
Every system of the body is involved in every movement we make. Without the active participation of the nervous, circulatory, endocrine, respiratory, digestive, immune, connective tissue, fluid, skeletal, ligamentous, and muscular systems (to mention just a few), we wouldn’t be able to create the movements of the breath or lift our arms overhead and fold forward into uttanasana, much less launch the body through space into a handstand.
DYNAMIC BALANCE OF BODY SYSTEMS
Any part of the body that we turn our attention to is part of more than one system: While bones are generally considered part of the skeletal system, they also play important roles in other systems, such as the circulatory, nervous, immune, and endocrine systems. The bones are part of the circulatory and immune systems because red and white blood cells are created in the bone marrow. They are part of the nervous system because of the role calcium has in the working of neurons, and they are part of the endocrine system because of the hormones secreted by bone cells that play a role in our metabolism. None of these systems can work alone. Without the circulatory system, other systems such as the respiratory, endocrine, and digestive systems would not be able to distribute oxygen, hormones, and nutrients to the cells of the body. Without the nervous system, it would be impossible to coordinate the muscles of the limbs or to modulate the dilation of the blood vessels to supply the bones, brain, heart, or muscles with enough blood. All of the systems of the body are overlapping and interdependent (figure 3.1, page 46).
If we focus on just one or two systems in studying anatomy and yoga, we run the risk of terribly oversimplifying the incredible effects that the practice of asana has on every system in the body. On the other hand, we can dive deeply into a single point of focus and find incredible complexity that enriches our experience of the whole. For the purposes of this book, the focus is on the role of the skeletal and muscular systems in generating the movements that create asana, knowing that starting at any beginning point can bring us into a relationship with all the other systems and tissues in the body.
MUSCULOSKELETAL SYSTEM
Bones, ligaments, muscles, and tendons all weave together into a dynamic whole. The skeletal portion of the musculoskeletal system is made up of the bones, ligaments, and other tissues that make up the joints: synovial fluid, hyaline cartilage, and fibrocartilaginous discs and wedges. The muscular portion is made up of the muscles and tendons that cross the joint space and attach to the bones, as well as the nerve endings that organize the exquisite sequencing and timing of our muscle actions. All of these tissues are either composed of or wrapped in layers of connective tissue.
The skeletal system and the muscular system are often treated as separate systems. When we consider how movement is generated, it makes more sense to think of them as one musculoskeletal (or skeletomuscular) system. The muscles and bones work intimately together to negotiate our relationships to gravity and space, to provide our upright posture, and to help us move through the world, feed ourselves, use tools, and create change.
Without the structure and support of the skeletal system, the muscles would be a puddle of contractile tissue with nothing to move. On the other hand, without the movement created by muscles, the bones would be unable to move through space and could only respond to forces outside the body travelling through them. Without connective tissue such as ligaments and tendons, bones and muscles would have no way to relate to each other.

One job of the bones is to receive weight and transmit force, while the ligaments direct that force along specific pathways. This weight and force might be generated by the pull of gravity or by other sources, such as the muscles that propel the leg through space to take a step. The job of the muscular system is to move the bones into positions where they can do their job as effectively as possible.
SKELETAL SYSTEM TISSUE: BONES AND LIGAMENTS
Our bones are incredible structures. They are strong enough to resist collapsing under the force we send through them, light enough that we can move them through space, and resilient enough to adapt to stresses that come from all directions in three-dimensional space.
Ligaments do an amazing job as well. They are flexible enough to allow three-dimensional movement at the joint and strong enough to align and guide a tremendous amount of force from bone to bone across the space of the joint.
Movement in the skeletal system happens on many levels. On a cellular level, individual cells are constantly breaking down and building up the matrix of the bone and the fibers of ligaments. On a tissue level, each bone and ligament has some degree of ability to change shape in response to the forces travelling through it. On a system level, movement happens where a relationship exists between two or more bones: the joints.
JOINTS
In the skeletal system the term joint describes the space where the surfaces of two or more bones come into relationship and articulate with each other. A joint is more of an event than a place in the sense that it depends on movement and change for its existence. If any movement is happening, however miniscule, then there is a joint.
Conventionally, joints are classified structurally by the tissue that connects the two bones. This could be cartilage, fibrous tissue, synovial fluid, or some combination of the three. Joints can also be classified functionally by the degree of movement possible and biomechanically by the number of bones involved and the complexity of the joint.
In the analysis of asana, we observe movement in synovial joints, the most mobile joints in the body. (Several of these synovial joints are also at least partly cartilaginous or fibrous.)
Synovial Joints
Starting from the center and moving outward, a synovial joint is composed of the bones that articulate with each other, the synovial fluid between them, the membrane that creates that synovial fluid, and the connective tissue that surrounds and protects the whole structure (figure 3.2).
To be more specific, the articulating surfaces at the ends of the bones are covered with a layer of hyaline cartilage that cushions and protects. These layers of hyaline cartilage are slippery and allow the ends of the bones to slide along each other with little friction.
Between these layers of hyaline cartilage, synovial fluid acts as a lubricant and facilitates the sliding of the articulating surfaces. Synovial fluid also distributes force in the joint to a slight degree, and it acts as a fluid seal between the two surfaces, as oil does between two panes of glass, holding them together. Synovial fluid is secreted by a synovial membrane (or synovium) that is connected to both bones. The presence of this synovial membrane defines the boundaries of the joint space: Everything outside the synovial membrane is outside the joint space.
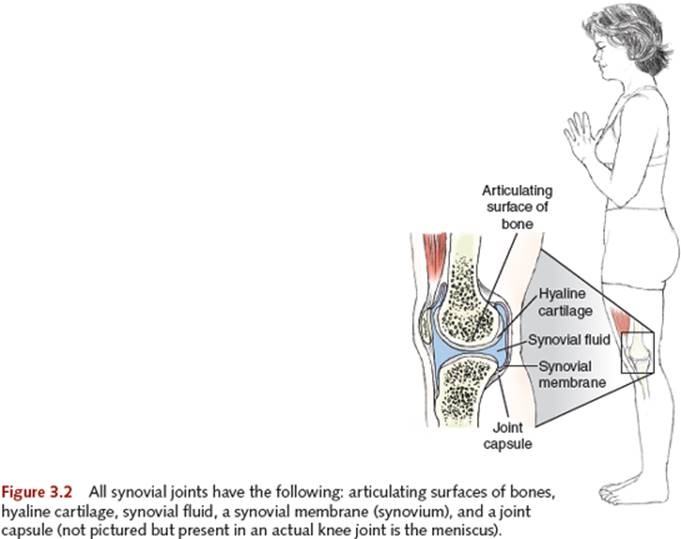
The synovial membrane is wrapped by layers of connective tissue that form the joint capsule, providing containment for the movement possibilities created by the mobility of the hyaline cartilage and synovial fluid. On the very outside of the joint capsule are fibers that thicken and organize themselves into straplike bands, the collateral ligaments. These ligaments direct the force that travels through a joint and keep the movement on track.
Superficial to all these elements are the muscles that travel across the joint.
Balanced Joint Space
In a healthy, functional joint, the space between the two bones is balanced, and maintains that balance throughout the full range of motion (ROM) in that joint. Balance is not the same as symmetry, and maintaining balanced joint space1 through the range of motion doesn’t mean that the joint space is evenly distributed at absolutely every moment.
Balanced joint space is instead the product of a complex set of factors, including but not limited to the contours of the articulating surfaces of the bones, the viscosity of the synovial fluid, the resilience of the joint capsule and ligaments around the joint, and the assorted contractions of the muscles around the joint. In a larger sense, the hydration of the tissues, the efficiency of the circulatory system, the ability of the nervous system to sense movement in the joint, and the quality of the mind’s attention contribute to this balance.
The layer of hyaline cartilage at the end of each bone is able to absorb a tremendous amount of force and distribute that force into the trabeculae, the weight-bearing scaffolding of the bone. This force then travels through bone and joint and bone and joint until it meets a surface that can absorb the force, such as the earth, or it is discharged in some movement through space, such as throwing a ball. That force could also be received and transmitted to another structure, or dispersed in unhelpful ways through soft tissues.
When the joint space is not balanced through the full range of movement and force is not distributed across the articulating surfaces, there is some wear and tear on the hyaline cartilage. Like other tissues in the body, the hyaline cartilage constantly remodels itself and can repair minor wear and tear without long-term consequences. (There are other tissues in the body, such as muscles, that remodel at a faster rate than the hyaline cartilage.) If the imbalance in the joint space is consistent and continuous over a long period of time, the hyaline cartilage cannot repair itself and can eventually become damaged or worn away. If the hyaline cartilage is worn away, the ends of the bones rub against each other. This friction eventually stimulates the bones to grow unevenly, which causes more friction and stress on the bones. This cycle of friction and growth can become quite painful and is one cause of osteoarthritis.
Lack of balance in the joint space can arise for a variety of reasons. Sometimes people are just born with joints that don’t line up efficiently. More often the challenge arises from inefficient movement patterns that eventually lead to imbalances in the joint capsule and ligaments, over- or underuse of the muscles surrounding the joint, or habitual patterns in the nervous system. These habits are often perpetuated through familiarity and lack of awareness. Even a perfectly appropriate idea, exercise, or image can be dangerous when done for too long or in a way that excludes any other ideas. Our ideas about movement are at fault as much as the bones and ligaments we are born with. For example, pulling the shoulders back to open up the front of the chest is a common instruction. This is a useful instruction for people whose shoulders have slid forward around their rib cage. If, however, there is an issue in the spine, pulling the shoulders back might increase neck and upper back effort without addressing the underlying spinal issue. Also, it might be an effective instruction once or twice, but if someone continues to pull the shoulders back for an extended period of time, that person will end up pulled so far back that he is out of balance in the other direction.
Joint Actions
It is a fundamental fallacy to think that our human bodies work like the structures that humans have built. Human joints are frequently compared to devices used in construction to create joints, such as a hinge or a ball and socket. The mechanics of a human joint, however, are not the same as those of a joint between pieces of wood or metal or ceramic or plastic, in part because of the nature of the materials.2
Useful as it might be on a superficial level to compare the workings of the elbow joint to a hinge, drawing this parallel limits our ideas about how movement happens at the joint. Nothing in the body is perfectly flat or straight or less than three-dimensional, including the articulating surfaces of the bones. Because these articular surfaces always have volume and contour, movement in the joints is always three-dimensional.
The conventional terms used to describe movement at the joints, joint actions, describe fairly simple movements that are flat and two-dimensional and happen in a single plane. No single joint action takes into account the volume of the movement possibilities at every joint.
The implication of using two-dimensional language to describe movement at our joints is that we simplify our concept of what movements are possible and then simplify the movements we do. The danger is that we deprive ourselves of movement choices and overuse the few options we think are available to us.
Because all the articulating surfaces in our joints are three-dimensional, every joint is capable of more than one joint action, if not three or four. Equal amounts of movement are not possible in each action, but even if it is a tiny movement, the joint has movement in every dimension. That tiny movement could have huge repercussions on two or three joints or in 5 to 10 years down the line.
Conventional Definitions of Joint Actions
The basic terms that describe joint actions apply to a majority of the joints in the body. Several terms have specific meanings in particular joints, and some terms are used in more than one joint but mean different things in different joints.
Anatomical definitions of joint actions often use planes to describe the movement. A plane is a two-dimensional surface, and the three basic planes intersect at right angles to each other. When the planes are oriented so that they intersect in the center of the body, they can be used to describe relationships within the body (anterior and posterior describe a sagittal relationship of body parts) or movements (flexion and extension describe sagittal movement of the spine). The vertical plane (also called the coronal or door plane) divides the body into front and back. The horizontal plane (also called the transverse or table plane) divides the body into top and bottom. The sagittal plane (also called the median or wheel plane) divides the body into right and left sides.
Spinal Joint Actions
The following terms describe movements when the joints of the spine are moving and the vertebrae articulate in relationship to each other. In these spinal actions the actual shape of the spine changes, which is a different action than moving the spine through space (by articulating at the hips, for example, which would be an action in the legs). Common yoga language such as forward bending is a nonanatomical description that can refer to either a movement of the spine through space or the spinal joint action of flexion (see chapter 2, page 33).
flexion—Movement in the sagittal plane that brings the anterior surfaces of the body toward each other.
extension—Movement in the sagittal plane that brings the anterior surfaces of the body away from each other.
lateral flexion—Movement in the vertical or coronal plane that bends the spine to one side or the other.
rotation—Movement in the horizontal or transverse plane, around the vertical axis of the spine:
• In rolling, all of the parts of the spine rotate in the same direction.
• In twisting, one part of the spine turns a different direction from another part of the spine.
axial extension—Movement along the vertical axis of the spine that lengthens the spine by taking out the sagittal curves.
circumduction—Movement that travels through space around the axis of the body, tracing a cone shape. This is not the same as rotation.
Limb Joint Actions
These terms describe the joint actions that can happen in the upper and lower limbs, which include the shoulder girdle and pelvis. As in the spine, there is a difference between moving a joint through space and actually articulating in the joint, which is the joint action. (For example, when you lift your whole arm to the ceiling, the elbow does move through space but it doesn’t necessarily articulate.)
Actions in All Limbs
For the joint actions below, the same terms can be used to describe movement at a variety of joints. Which bones are involved in the movement will depend on which joint is articulating.
flexion—Movement in which the anterior surfaces of the limb move toward each other; depending on the position of the spine, hips, and shoulders, this could happen in any plane. Because of a spiral in the limbs that occurs while we are embryos, flexion in the knee, ankle, and foot joints moves what we consider the back surfaces of the leg toward each other.
extension—Movement in which the anterior surfaces move away from each other; again, depending on the position of the spine, hips, and shoulders, this could happen in any plane. And, because of that embryological spiral, extension in the knee, ankle, and foot joints moves what we consider the back surfaces of the leg away from each other.
rotation—Movement around the axis of the limb; in the hips, shoulders, and forelegs, this is further described as internal (or medial) and external (or lateral) rotation. Rotation in the hand, foot, and forearm has special names (see the sections that follow).
abduction—Movement of the limb away from the torso or the midline of the body; in the hand, foot, and scapula, this term describes a more specific action (see the sections that follow).
adduction—Movement of the limb toward the torso or the midline of the body; in the hand, foot, and scapula this term describes a more specific action (see sections that follow).
circumduction—Movement that travels through space around the axis of the limb, tracing a cone shape. This is not the same as rotation.
Actions in Specific Limbs
Some parts of the limbs can perform movements that are not described by the general terms listed above. These joint actions have terms that are used for specific body parts (such as pronation and supination, which only occur in the feet and forearms, or radial deviation, which only occurs in the wrists). In some body parts a general joint action will refer to a different movement than in the rest of the limb. (In the hands, abduction refers to movement away from the middle finger rather than away from the midline of the body.)
Hand
rotation—Rotation around the long axis of the hand is called eversion when it lifts the outer edge of the hand and inversion when it lifts the inner edge of the hand.
abduction—Movement of the fingers away from the third finger.
adduction—Movement of the fingers toward the third finger.
radial deviation—Movement of the fingers toward the radial (thumb) side of the hand.
ulnar deviation—Movement of the fingers toward the ulnar (pinkie) side of the hand.
opposition—Movement of the thumb and the little finger toward each other.
Wrist
dorsiflexion—Movement when the angle between the back of the hand (the dorsal surface) and the forearm decreases. (From an embryological perspective, this is extension of the wrist.)
palmar flexion—Movement when the angle between the palm of the hand (the palmar surface) and the forearm decreases. (From an embryological perspective, this is flexion of the wrist.)
radial deviation or abduction—Movement of the hand toward the radial side of the forearm (thumb side).
ulnar deviation or adduction—Movement of the hand toward the ulnar side of the forearm (pinkie side).
Forearm
rotation—Rotation of the radius and ulna so that they cross each other is called pronation, and rotation of the radius and ulna so that they are uncrossed is called supination. (Sometimes pronation is described as “palm down” and supination as “palm up,” but the position of the palm doesn’t accurately describe these actions because of the movements available in the shoulder joint and scapula.)
Clavicle
elevation—Movement of the distal end of the clavicle upward in the vertical plane.
depression—Movement of the distal end of the clavicle downward in the vertical plane.
upward rotation—Rotation of the clavicle around its longitudinal axis to roll the top surface backward.
downward rotation—Rotation of the clavicle around its longitudinal axis to roll the top surface forward.
protraction—Movement of the distal end of the clavicle forward, usually accompanied by scapular protraction.
retraction—Movement of the distal end of the clavicle backward, usually accompanied by scapular retraction.
Shoulder (Glenohumeral Joint)
flexion—Movement of the arm sagittally forward in space.
extension—Movement of the arm sagittally backward in space.
abduction—Movement of the arm from alongside the torso to open to the side and away from the body.
adduction—Movement of the arm from an abducted position toward the side of the body.
horizontal abduction—Movement of the arm from a flexed position in front of the body to open to the side and away from the body.
horizontal adduction—Movement of the arm from an abducted position to the side of the body to a flexed position in front of the body.
protraction—Movement that slides the head of the humerus forward in the sagittal plane.
retraction—Movement that slides the head of the humerus backward in the sagittal plane.
Scapula
elevation—Sliding of the scapula upward in the vertical plane.
depression—Sliding of the scapula downward in the vertical plane.
upward or lateral rotation—Rotation of the scapula in the vertical plane in such a way that the glenoid fossa faces upward and the inferior angle moves laterally to the side.
downward or medial rotation—Rotation of the scapula in the vertical plane in such a way that the glenoid fossa faces downward and the inferior angle moves medially toward the spine.
abduction or protraction—Movement in the horizontal plane away from the spine, which ends up wrapping the scapula toward the front of the body.
adduction or retraction—Movement in the horizontal plane toward the spine, which ends up drawing the scapulae toward each other in the back.
Foot
rotation—Rotation around the long axis of the foot is called eversion when it lifts the outer edge of the foot and inversion when it lifts the inner edge of the foot.
abduction—Movement of the forefoot toward the lateral edge (little toe side) of the foot without moving the heel; the movement of the toes away from the second toe.
adduction—Movement of the forefoot toward the medial edge (big toe side) of the foot without moving the heel; the movement of the toes toward the second toe.
pronation and supination—In the feet, pronation is sometimes considered the same thing as eversion, and is sometimes a combination of eversion and abduction. And in the feet, supinationis sometimes used interchangeably with inversion, and is sometimes a combination of inversion and adduction.
Ankle
plantar flexion—Movement when the angle between the sole of the foot (the plantar surface) and the back of the foreleg decreases; pointing the foot. (From an embryological perspective, this is ankle flexion.)
dorsiflexion—Movement when the angle between the top of the foot (the dorsal surface) and the foreleg decreases. (From an embryological perspective, this is ankle extension.)
Pelvis
nutation—Movement of the sacrum separately from the pelvic bones in such a way that the top of the sacrum tips forward, or nods, and the bottom of the sacrum (near the coccyx) tips back. This is movement at the sacroiliac (SI) joint, between the sacrum and pelvic or innominate bone, not movement of the full pelvis (which would be an anterior or posterior tilt of the pelvis caused by joint action at the hip joints or lumbar spine).
counternutation—Movement of the sacrum in such a way that the top of the sacrum tips backward and the bottom of the sacrum (near the coccyx) tips forward. This is movement at the SI joint, between the sacrum and innominate bone, not movement of the full pelvis (which would be an anterior or posterior tilt of the pelvis caused by joint action at the hip joints or lumbar spine).
Range of Motion in Joints
The body never moves only one joint or does only one joint action. In any given movement, the body might be moving through the subtleties of 15 or even 500 different joint actions just to bend a leg or lift an arm.
Even if we set out to completely focus on one particular joint, as soon as we begin a movement, it travels to the joints at the other ends of the moving bones and into the next bones and joints and the next bones and joints and the next—all the way into the spine and all the way out to the periphery. If you are lying passively and someone else moves you, that movement will still travel through your tissues one way or another.
Because movement travels through the body in this way, it isn’t practical to focus exclusively on the range of motion in a single joint. While it is possible for a skilled hands-on practitioner to effectively isolate a joint and determine how much movement is possible in the bones and soft tissues, as soon as we begin to move volitionally, we must take into account the rest of the movement choices in the body.
In observing the wholeness of a person moving, you are able see that when movement seems to stop in one joint, it moves to the next. Sometimes it skips over joints that don’t move easily or becomes so small that it is difficult to perceive, but it always goes somewhere.
Instead of focusing on the range of motion in specific joints, look at the whole pattern of movement in the skeletal system: Observe where there is much movement and it seems easy, and observe where there is less movement and it seems more challenging. Then ask how to bring balance: If someone has made it to the limit of what can happen in one joint, is movement possible at the next joint? Do some joints do all the movement to the point of being overly mobile? Are some joints not moving at all, as if there aren’t joints there? It can also be a question of attention: Whether someone is very flexible or very stiff, his or her body will have places where there is a lot of awareness and places that are more in the shadows.
CONCLUSION
Success in an asana (or any movement) should be measured by the quality of balance or intrinsic equilibrium through the whole body, rather than in the range of motion in a single joint. This quality arises in the skeletal system from the presence of balanced joint space in each joint, the availability of clear pathways for movement through the bones and joints, and the awareness of our individual patterns in the wholeness of the systems of our body.
1 I first learned the concept of balanced joint space through Body–Mind Centering (BMC). It is fundamental to BMC’s approach to repatterning movement in the skeletal and ligamentous systems.
2 If you are interested in reading more about these differences, Steven Vogel has written a fascinating book called Cats’ Paws and Catapults: Mechanical Worlds of Nature and People (W. W. Norton & Company, 1998).