
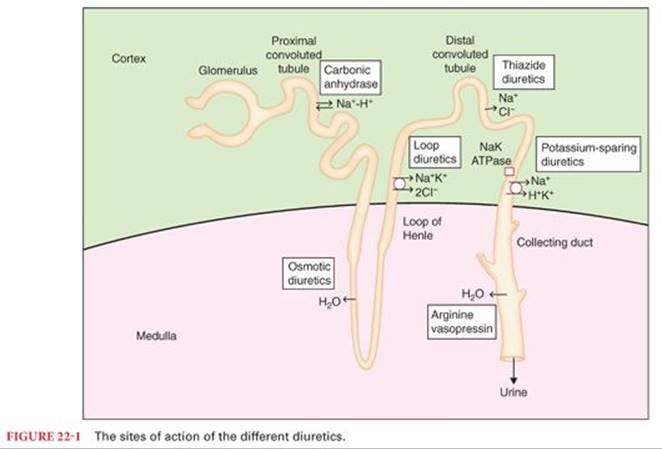
Diuretics, drugs commonly used in the treatment of hypertension and heart failure, consist of a group of drugs with differing pharmacokinetic and pharmacodynamic properties. Their primary effect is to increase urine flow and to promote diuresis. Most diuretics produce their clinical effect by blocking sodium (Na+) reabsorption in different locations of the nephron,1 resulting in increased sodium ion delivery to the distal tubules. The normal driving force for potassium (K+) excretion by distal renal tubules is the transtubular electrical potential difference created by sodium reabsorption. The presence of Na+ in the distal tubules promotes its reabsorption in exchange for secretion of K+ and results in hypokalemia. The sites of action of the different diuretics are illustrated in Figure 22-1. In general, diuretics with a site of action upstream of the collecting duct result in hyponatremia, hypokalemia, and metabolic alkalosis. In contrast, collecting duct diuretics result in hyperkalemia and metabolic acidosis.2
Carbonic Anhydrase Inhibitors
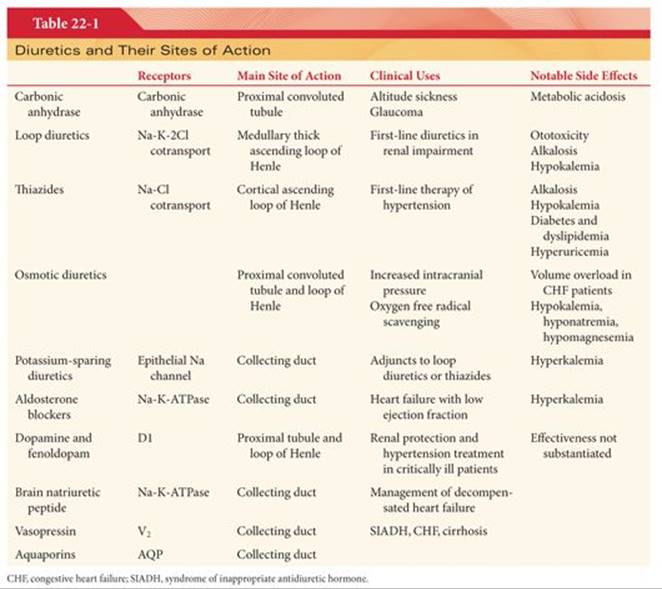
Acetazolamide is the prototype of a class of sulfonamide drugs that bind avidly to the enzyme carbonic anhydrase, producing noncompetitive inhibition of enzyme activity, principally in the proximal renal tubules as well as the collecting ducts (see Fig. 22-1; Table 22-1).3 A Na+-H+ exchanger allows absorption of Na+ in exchange for secretion of H+ into the renal tubule. HCO3− and H+ combine in the lumen of the proximal tubule to produce H2CO3. The enzyme carbonic anhydrase catalyzes the otherwise slow breakdown of H2CO3 into CO2 and H2O; CO2 diffuses readily into the tubular cells, where cytoplasmic carbonic anhydrase catalyses the reverse reaction leading to HCO3−, which then follows an electrochemical gradient across the basal membrane into the interstitium. The net result is absorption of HCO3−. Inhibition of carbonic anhydrase in the proximal renal tubule by this class of diuretics results in decreased reabsorption of Na+, HCO3−, and water.1,3
Pharmacokinetics and Pharmacodynamics
After oral administration, acetazolamide is excreted unchanged by the kidneys. The dose should be adjusted in patients with renal failure and the elderly.4 Acetazolamide completely blocks membrane-bound and cytoplasmic carbonic anhydrase in the proximal tubule and to a lesser extent in the collecting ducts, preventing Na+ and HCO3− absorption.3 This increased excretion of HCO3− results in an alkaline urine and metabolic acidosis. Natriuresis associated with carbonic anhydrase inhibitors is modest, with an increase in fractional Na+ excretion of up to 5%.3 The increased delivery of Na+ to the distal tubules leads to potassium loss. Most of the chloride is reabsorbed in the loop of Henle,3 leading to the excretion of an alkaline urine in the presence of hyperchloremic metabolic acidosis.
Clinical Uses
In addition to its diuretic properties, acetazolamide is administered to decrease intraocular pressure in the treatment of glaucoma. There is a high concentration of the carbonic anhydrase enzyme in the ciliary processes; inhibition of the enzyme activity by acetazolamide results in decreased formation of aqueous humor and consequently a decrease in intraocular pressure.2 Similarly, formation of cerebrospinal fluid is also inhibited by acetazolamide. Accordingly, acetazolamide has been used in the treatment of idiopathic intracranial hypertension.2 Idiopathic intracranial hypertension, previously referred to as benign intracranial hypertension or pseudotumor cerebri, is characterized by increased intracranial pressure (ICP) in the absence of tumors or other causes and manifests with headaches, pulsatile tinnitus, and papilledema and visual changes secondary to the elevated ICP, which can progress to vision loss. Women are more likely to be affected, especially obese women in their third decade of life. When treatment with acetazolamide fails, surgical placement of a ventriculoperitoneal shunt to reduce the elevated ICP is an option. Lumbar punctures, in addition to being diagnostic by providing direct measurement of the elevated ICP, can provide symptomatic relief via removal of cerebrospinal fluid.
Acetazolamide may also be beneficial in the management of familial periodic paralysis because the drug-induced metabolic acidosis increases the local concentration of potassium in skeletal muscles.2Similarly, acetazolamide, by producing metabolic acidosis, may stimulate the respiratory drive in patients who are hypoventilating in a compensatory response to respiratory alkalosis, as occurs with altitude sickness. Altitude sickness, which can be prevented by a slow acclimatization process, develops following rapid ascent to high altitudes.2 The hypoxia at high altitudes is counteracted by hyperventilation, which leads to respiratory alkalosis, which depresses ventilation. Acetazolamide-induced metabolic acidosis can reverse this hypoventilation.2 Conversely, the loss of bicarbonate ions necessary to buffer carbon dioxide may result in the exacerbation of respiratory acidosis in patients with chronic obstructive airway disease, leading to central nervous system (CNS) depression.
Side Effects
There is a high incidence of systemic side effects associated with the use of acetazolamide such as fatigue, decreased appetite, depression, and paresthesias,4 which could be secondary to the development of acidosis.4 Acetazolamide dose should be reduced in patients with chronic renal insufficiency and avoided in patients with severe chronic renal insufficiency because of the increased risk of metabolic acidosis.2
Loop Diuretics
Furosemide, torasemide, azosemide, bumetanide, and ethacrynic acid are diuretics that inhibit reabsorption of sodium, potassium, and chloride by impairing activity of the Na+-K+-2Cl− transport protein in the medullary portions of the thick ascending limb of the loop of Henle. This area of the nephron is impermeable to water and accounts for the reabsorption of 20% to 30% of filtered Na+.1,2 Because of their site of action, loop diuretics are the most potent diuretics and have a dose-dependent response.2 Diuretics in general and loop diuretics in particular are first-line therapy in patients with fluid retention resulting from heart failure.2
Pharmacokinetics and Pharmacodynamics
Ethacrynic Acid
Ethacrynic acid is no longer in clinical use because of its side effect profile. Ototoxicity, a common dose-dependent side effect of loop diuretics, is more common with ethacrynic acid.2 Nausea is another common side effect.
Furosemide
Furosemide is effective when administered orally or intravenously (IV). However, absorption of orally administered furosemide varies between patients from 10% to 100%, with an average bioavailability of 50%.2,5 Protein binding is extensive, with approximately 90% of the drug bound to albumin. Glomerular filtration and renal tubular secretion account for approximately 50% to 60% of furosemide excretion. The remaining 40% to 50% is conjugated to glucuronide in the kidneys.2,5,6 The elimination half-life is 1 to 2 hours, resulting in the short duration of action. Furosemide has a rapid onset, producing diuresis within 5 to 10 minutes of administration, with a peak effect at 30 minutes and duration of action of 2 to 6 hours. In order to achieve natriuresis, furosemide needs to reach the site of action within the kidneys. In patients with normal renal function, 40 mg of IV furosemide will produce maximal natriuresis.5 Because of decreased drug delivery to the tubule in chronic renal insufficiency, the dosing of loop diuretics should be increased in these patients.2,5 Maximal diuresis can be achieved with an IV bolus of 160 to 200 mg, administered slowly to avoid the occurrence of tinnitus.5 Doses larger than 200 mg will not result in increased natriuresis.5 In addition, in patients with chronic renal insufficiency, a loading dose of furosemide followed by a continuous infusion may be used to achieve a sustained diuresis rather than repeated boluses.1,5 More recently, the Diuretic Optimization Strategies Evaluation (DOSE) trial, a prospective randomized study of the use of loop diuretics in patients admitted with acute heart failure, did not find a significant difference in symptomatic relief or improvement of renal function with the use of high-dose diuretics or with continuous diuretic infusion, compared to low-dose or repeated diuretic boluses respectively.7 The combination of furosemide with a different class of diuretic, such as a thiazide diuretic, may increase the response.5
Bumetanide and Torasemide
Bumetanide has a bioavailability of 80% to 100% after oral administration and can be administered orally, IV, or intramuscularly. It is 40 times more potent than furosemide except in its effect on potassium excretion.2 Similar to bumetanide, torasemide’s metabolism is mostly by the liver,2 and in patients with liver failure, there is increased drug delivery to the kidneys.5 Torasemide is twice as potent as furosemide and has a longer duration of action, with a plasma half-life of 3 to 4 hours5 allowing for a once a day dosing regimen.8
Clinical Uses
Loop diuretics are not the first-line treatment for hypertension in patients with normal kidney function. However, they are first-line diuretics in patients with renal insufficiency.1,5,8 The antihypertensive effect of loop diuretics is due to their ability to decrease intravascular fluid volume and eliminate salt. Compared to furosemide, the long-acting drug azosemide produces better blood pressure control, preserving the normal 10% decline in blood pressure in many individuals that occurs at night (nocturnal dipping) and is associated with better long-term outcomes.
Loop diuretics are commonly used in patients admitted with acute exacerbation of heart failure.7,8 Diuresis leads to loss of water and salt with resulting decrease in intravascular volume thus lowering ventricular filling pressure and reducing pulmonary edema.6 In addition, loop diuretics induce renal synthesis of vasodilatory prostaglandins, further enhancing their diuretic effects by increasing renal blood flow and leading to a redistribution of cortical blood flow.6 Treatment with torasemide was found to decrease readmissions related to heart failure when compared to furosemide.1
Furosemide decreases ICP by inducing systemic diuresis and decreasing cerebrospinal fluid production. This diuretic-induced decrease in ICP is not accompanied by changes in cerebral blood flow or plasma osmolarity. Furosemide can be administered as single-drug therapy (0.5 to 1.0 mg/kg IV) or as a lower dose (0.1 to 0.3 mg/kg IV) in combination with mannitol. Alterations in the blood–brain barrier do not influence the immediate or subsequent effects of furosemide on ICP. This characteristic contrasts with that of mannitol, which may produce rebound intracranial hypertension if a disrupted blood–brain barrier allows mannitol to enter the CNS. A combination of furosemide and mannitol is more effective in decreasing ICP than either drug alone, but severe dehydration and electrolyte imbalance are also more likely.
In the presence of symptomatic hypercalcemia, furosemide may be used to lower the plasma concentration of calcium by stimulating urine output.
Side Effects
Side effects of loop diuretics most often manifest as abnormalities of fluid and electrolyte balance. They can lead to hypokalemia and increase the likelihood of digitalis toxicity. As with thiazide diuretics, loop diuretics may cause hyperuricemia, but this is rarely clinically significant. Likewise, hyperglycemia, although possible, is less likely to occur than with thiazide diuretics. Acute or chronic treatment of patients with diuretics, including loop diuretics, may result in tolerance to the diuretic effect (“braking phenomenon”). Acute tolerance is presumed to reflect activation of the renin-angiotensin system to retain sodium and water in the presence of a contracted extracellular fluid volume.5With chronic use of diuretics, there is evidence of a compensatory hypertrophy of those portions of the renal tubule (especially distal convoluted tubules) responsible for sodium retention, leading to decreased diuretic effectiveness.5When tolerance develops in a patient treated chronically with furosemide, it may be possible to reestablish a diuretic effect with the administration of a thiazide diuretic, which blocks the hypertrophied Na+ reabsorption sites.5
Loop diuretics should only be administered to patients with a normal or increased intravascular fluid volume. Hypotension may result from administration of loop diuretics to hypovolemic patients exacerbating renal ischemic injury and concentrating nephrotoxins in the renal tubules. Accordingly, loop diuretics should be avoided in patients with acute renal insufficiency.2,9
Furosemide increases renal tissue concentrations of aminoglycosides and enhances the possible nephrotoxic effects of these antibiotics. Cephalosporin nephrotoxicity may also be increased by furosemide. In addition, loop diuretics potentiate nondepolarizing neuromuscular blockade.2 Furosemide has been associated with an allergic interstitial nephritis similar to that occasionally produced by penicillin. Cross-sensitivity may exist when a patient allergic to other sulfonamides is given furosemide. The renal clearance of lithium is decreased in the presence of diuretic-induced decreases in sodium reabsorption, and plasma concentrations of lithium may be acutely increased by the IV administration of furosemide in the perioperative period.10
Ototoxicity, either transient or permanent, is a rare, dose-dependent complication associated with the use of loop diuretics. This side effect is most likely to occur with prolonged increases in the plasma concentration of these drugs in the presence of other ototoxic drugs such as aminoglycosides or in the presence of chronic renal insufficiency.2
Thiazide Diuretics
Thiazide diuretics are most often administered for long-term treatment of essential hypertension in which the combination of diuresis, natriuresis, and vasodilation are synergistic. Included in this class of drugs are hydrochlorothiazide and thiazide-like drugs, such as chlorthalidone and indapamide. Hydrochlorothiazide is the second most frequently prescribed antihypertensive medication, and thiazides are usually administered in combination with other antihypertensives.11 Thiazide diuretics may also be used to mobilize edema fluid associated with renal, hepatic, or cardiac dysfunction. Less common uses of thiazide diuretics include management of diabetes insipidus and treatment of hypercalcemia.
Pharmacokinetics and Pharmacodynamics
Thiazide diuretics inhibit the Na+-Cl− cotransporter in the cortical portion of the ascending loop of Henle and the distal convoluted tubule, inhibiting reabsorption of 5% to 10% of the filtered sodium2 (see Fig. 22-1). Enhanced distal delivery of Na+ results in increased excretion of potassium into the renal tubules, resulting in an increase in the urinary excretion of sodium, chloride, and potassium ions. In addition, thiazide diuretics stimulate the reabsorption of calcium in the distal convoluted tube.1
Thiazide diuretics are readily absorbed when administered orally; hydrochlorothiazide has a 60% to 70% bioavailability, and they are extensively protein-bound.8 Most thiazides are eliminated unchanged in the kidney; indapamide, however, is metabolized by the liver.5 Thiazides’ effectiveness markedly decreases in patients with renal insufficiency.5 Thiazide diuretics have a long half-life of 8 to 12 hours, allowing for a convenient once-a-day dosing.8 Chlorthalidone has the longest elimination half-life of 50 to 60 hours.8 Indapamide, xipamide, and metolazone are structurally related to furosemide but share a thiazide-like mechanism of action with differences in their clinical effects.2 When compared to hydrochlorothiazide, metolazone has a slow and unpredictable absorption and tends to accumulate because of its prolonged elimination half-life.5 Thiazide diuretics, with the exception of metolazone, are ineffective in patients with severe renal insufficiency and the use of loop diuretics in these patients is recommended if diuresis is needed.8
Clinical Uses
Thiazide diuretics are recommended as first-line therapy for essential hypertension and the use of chlorthalidone specifically has been shown to decrease the risk of major cardiovascular events when compared to calcium channel blockers or angiotensin-converting enzyme inhibitors in a large randomized control trial, the Antihypertensive and Lipid-Lowering Treatment to Prevent Heart Attack Trial (ALLHAT).12
The antihypertensive effect of thiazide diuretics is due initially to a decrease in extracellular fluid volume, often with a decrease in cardiac output, which normalizes after several weeks.1 The sustained antihypertensive effect of thiazide diuretics, however, is due to peripheral vasodilation, which requires several weeks to develop. It is unclear whether the resulting decrease in systemic vascular resistance after chronic thiazide therapy results from direct or indirect vasodilatory effect.11
Because they stimulate calcium reabsorption, thiazide diuretics are used in the treatment of calcium-containing renal calculi.1 Although unlikely to cause hypercalcemia, thiazide diuretics should be used cautiously in patients with conditions that predispose to hypercalcemia, such as hyperparathyroidism and sarcoidosis.2
Chlorthalidone, a longer acting thiazide-like diuretic, is recommended for use in resistant hypertension, achieving better nighttime control of the blood pressure.1 In addition, treatment with chlorthalidone resulted in decreased cardiovascular events when compared to treatment with lisinopril or amlodipine.12
Indapamide, a weak diuretic, decreases blood pressure by causing vasodilation.2 In contrast, xipamide is a potent diuretic and kaliuretic, and frequent measurement of potassium levels is recommended when it is prescribed.2Metolazone can promote diuresis in patients with renal insufficiency, in whom the other thiazides effective, and is usually administered with a loop diuretic. Their concomitant use should be monitored closely because of their synergism and because of metolazone’s propensity to accumulate due to its long elimination half-life.2,5,8
Side Effects
Thiazide diuretic–induced hypokalemic, hypochloremic, metabolic alkalosis is a common side effect when these drugs are administered chronically for maintenance treatment of essential hypertension. However, these side effects are usually well tolerated at low doses.8 Hypokalemia may manifest as skeletal muscle weakness and gastrointestinal ileus and may increase the risk of developing digitalis toxicity. Depletion of sodium and magnesium ions may accompany kaliuresis. Cardiac dysrhythmias may occur as the result of diuretic-induced hypokalemia or hypomagnesemia. In addition, hypercalcemia may result, especially in patients receiving calcium supplements or vitamin D therapy.2 The use of thiazide diuretics can potentiate nondepolarizing neuromuscular blockade by producing hypokalemia.2 The effectiveness of thiazides is decreased in patients receiving nonsteroidal antiinflammatory drugs.8 In addition, thiazide diuretics may promote lithium reabsorption in the proximal tubule by a compensatory mechanism, thereby potentiating toxicity in patients on lithium therapy.2 Inhibition of renal tubular secretion of urate by thiazide diuretics can result in hyperuricemia in 50% of treated patients, and a small percentage of patients might develop clinical gout.2,11
Thiazide diuretics may cause glucose intolerance and aggravate glucose control in diabetic patients,2 especially when used in combination with β blockers. The mechanism of hyperglycemia is unknown but may result from a drug-induced decrease of insulin release from the pancreas and peripheral resistance to the effects of insulin.11 In addition, thiazide-induced hypokalemia may be associated with glucose intolerance and treating the hypokalemia may protect from developing diabetes.8 Thiazide treatment may affect cholesterol and triglyceride levels, aggravating hyperlipidemia.11 Intravascular fluid volume status should be considered in all patients treated with thiazide diuretics who are scheduled for surgery. The presence of orthostatic hypotension should arouse suspicion that intravascular fluid volume is decreased. Because of the structural similarities between sulfonamide antibiotics and thiazide and loop diuretics, it has been suggested that patients with sulfa allergy may demonstrate cross-reactivity to these classes of diuretics.2
Osmotic Diuretics
Osmotic diuretics such as mannitol, urea, isosorbide, and glycerin are inert substances that do not undergo metabolism and are filtered freely at the glomerulus. Their administration causes increased plasma and renal tubular fluid osmolality, with resulting osmotic diuresis.3 Portions of the renal tubules that are highly permeable to water, namely, the proximal renal tubules and more importantly, the loop of Henle, represent the principal site of action of osmotic diuretics.3
Mannitol
Mannitol is the only osmotic diuretic in current use. Structurally, mannitol is a six-carbon sugar alcohol that does not undergo metabolism. It is not absorbed from the gastrointestinal tract, which necessitates its exclusive use by IV injection to achieve a diuretic effect. Mannitol does not enter cells, and its only means of clearance from the plasma is by glomerular filtration.
Pharmacokinetics and Pharmacodynamics
After administration, mannitol is completely filtered at the glomeruli, and none of the filtered drug is subsequently reabsorbed from the renal tubules.3 By increasing tubular fluid osmolality, it decreases water reabsorption and promotes water diuresis.2 Sodium is diluted in the retained water in the renal tubules, leading to less reabsorption of this ion. However, hypernatremia may result from the water diuresis.2
In addition to causing renal tubular effects, IV administration of mannitol also increases plasma osmolarity, thus drawing fluid from intracellular to extracellular spaces. This increased plasma osmolarity may result in an acute expansion of the intravascular fluid volume which could be poorly tolerated in patients with borderline cardiac function. Increased plasma osmolarity allows water to move along an osmotic gradient from tissues, including the brain, into the intravascular space, leading to decreased ICP. Mannitol is a scavenger of oxygen-free radicals, which may prevent cellular injury.
Clinical Uses
Mannitol is used primarily in the acute management of elevated ICP and in the treatment of glaucoma. Mannitol decreases ICP by increasing plasma osmolarity, which draws water from tissues, including the brain, along an osmotic gradient. Mannitol begins to exert an effect within 10 to 15 minutes, with a peak effect at 30 to 45 minutes and a duration of 6 hours.13 The effect on ICP is dose-dependent within this dosing range and the larger dose may last longer. However, larger doses, up to 2 g/kg, and repeated administration can result in metabolic derangements. An intact blood–brain barrier is necessary for the cerebral effects of mannitol. If the blood–brain barrier is not intact, mannitol may enter the brain, drawing fluid with it and causing worsening of the cerebral edema. In addition, a rebound increase in ICP may occur following mannitol use.13
Mannitol has been used to prevent perioperative kidney failure in the setting of acute tubular necrosis. It is thought to provide renal protection via several mechanisms. As an osmotic diuretic, it is not reabsorbed by the tubules and results in osmotic diuresis that forces casts and necrotic debris out of the renal tubules. In addition, mannitol has been shown to cause vasodilation of vascular smooth muscle mediated by the release of prostaglandins,13 which is dependent on the dose and rate of administration.14 This vasodilation leads to improved renal blood flow, thereby protecting the kidneys from acute failure following renal tubular necrosis.2,13 Mannitol also has free radical scavenging properties, which may protect transplanted kidneys following reperfusion.2,13 Despite its common use during cardiac and major vascular surgery for renal protection, it has not been shown to prevent perioperative acute renal failure.13
Side Effects
The initial increase in intravascular volume associated with the administration of mannitol may be poorly tolerated in patients with left ventricular dysfunction, leading to pulmonary edema. For this reason, furosemide may be a preferred drug for treatment of increased ICP in patients with left ventricular dysfunction. In addition, in patients with renal insufficiency, mannitol is not filtered and will cause increase in the intravascular volume.5 Prolonged use of mannitol may cause hypovolemia, electrolyte disturbances with hypokalemic hypochloremic alkalosis, and plasma hyperosmolarity due to excessive excretion of water and sodium.
Potassium-Sparing Diuretics
Potassium-sparing diuretics act on the collecting ducts and are grouped in two categories: pteridine analogs and aldosterone receptor blockers.1 Pteridine analogs, such as triamterene and amiloride, prevent Na+ reabsorption in the cortical collecting duct by blocking the epithelial Na+ channels (ENa+C), independent of aldosterone. Aldosterone receptor blockers on the other hand, such as spironolactone and eplerenone, prevent the synthesis and the activation of the aldosterone-dependent basal cell Na+-K+-ATPase pump. Both mechanisms result in decreased Na+ reabsorption without the increased K+ secretion that would otherwise occur.1 The collecting duct accounts for less than 3% of sodium reabsorption. Accordingly, potassium-sparing diuretics do not cause substantial diuresis and are not used as single antihypertensive therapy.1,15 They are used in conjunction with thiazide diuretics to prevent the associated loss of potassium and magnesium.8
Pharmacokinetics and Pharmacodynamics
Oral absorption of amiloride and triamterene is limited (25% and 50%, respectively).3 Amiloride is more potent than triamterene and is not metabolized but excreted unchanged in the kidneys.5 Triamterene is a pteridine with a structural resemblance to folic acid. The metabolism of triamterene by the liver is extensive, and its metabolite, secreted into the renal tubule, has diuretic activity. Accordingly, both kidney and liver disease will affect the pharmacokinetics of triamterene.5 The elimination half-time for triamterene is 4 hours and for amiloride is about 20 hours.3
Clinical Uses
Potassium-sparing diuretics are most often used in combination with loop diuretics or thiazide diuretics to augment diuresis and limit renal loss of potassium; they are rarely used as monotherapy.15 Because cystic fibrosis is associated with increased sodium absorption across airway epithelium, aerosolized amiloride has been investigated in patients with cystic fibrosis. However, there is no evidence that topically administered amiloride causes any improvement in respiratory function or in mucus secretion in patients with cystic fibrosis.16
Side Effects
Hyperkalemia is the principal side effect of therapy with potassium-sparing diuretics, especially when combined with angiotensin-converting enzyme inhibitors or angiotensin II receptor blockers or in presence of nonsteroidal antiinflammatory drugs.2,15 Although triamterene is a weak folic acid antagonist, it rarely causes megaloblastic anemia except in patients already at risk for folic acid deficiency.15
Aldosterone Antagonists
Spironolactone is a synthetic steroid analog and a nonspecific mineralocorticoid receptor antagonist.8 This drug bears a close structural resemblance to aldosterone and results in potassium-sparing diuresis. Spironolactone binds to the cytoplasmic mineralocorticoid receptors in the collecting ducts, preventing Na+ reabsorption via the Na+-K+ pump. Eplerenone is a selective aldosterone receptor blocker, has less affinity for other mineralocorticoid receptors, and is less potent than spironolactone.15 It was previously believed that spironolactone effects were solely the result of competitive antagonism of aldosterone binding to the mineralocorticoid receptors. However, it has been shown that blocking the effects of other ligands, such as cortisol, on the mineralocorticoid receptors contributes to spironolactone and eplerenone clinical effects.15 Conversely, blockade of aldosterone produces beneficial end-organ effects, independently of blood pressure control.15 Spironolactone, when added to conventional therapy, was shown to effectively reduce morbidity and mortality in patients with heart failure with poor ejection fraction in the Randomized Aldactone Evaluation Study (RALES).17 This is thought to be the result of prevention of aldosterone-induced cardiac remodeling and fibrosis.15 However, spironolactone therapy was not found to significantly improve outcomes in patients with heart failure and preserved ejection fraction (diastolic heart failure).18 Similarly, eplerenone, a selective mineralocorticoid receptor blocker, has been shown to improve morbidity and mortality compared to optimal medical treatment in patients with acute myocardial infarction and left heart failure in the Eplerenone in Acute Myocardial Infarction Heart Failure Efficacy and Survival Study (EPHESUS).15,19
Pharmacokinetics and Pharmacodynamics
Spironolactone and eplerenone exert their effect on the aldosterone receptor of the tubular cell and reach the tubular cells from the plasma, not from the tubular fluid.2 They are the only diuretics that do not need to reach the renal tubule to exert their effect.3 They provide competitive blockade of epithelial aldosterone receptors in the distal tubule and the collecting duct, preventing Na+-K+-ATPase activation and resulting in decreased sodium reabsorption and in decreased potassium excretion.15 Oral absorption of spironolactone approaches 70% of the administered dose. Spironolactone undergoes extensive hepatic first-pass metabolism with multiple active metabolites,5 which account for spironolactone’s long half-life of 20 hours.15 Spironolactone and its metabolites are extensively bound to plasma proteins and excreted by the kidneys. Similarly, eplerenone undergoes hepatic metabolism and its half-life is prolonged in the presence of CYTP3A4 inhibitors, such as ketoconazole and verapamil.15
Clinical Uses
Spironolactone and eplerenone are often prescribed for the treatment of essential hypertension, in combination with thiazides, particularly in patients with a low renin state (Black, the elderly, and diabetics) or patients with metabolic syndrome (the name for a group of risk factors that raises risk for heart disease and other health problems, such as diabetes and stroke).15 Aldosterone antagonist diuretics are also used in patients with refractory hypertension, whose blood pressure remains difficult to control despite therapy with several medications, including a diuretic.15 Furthermore, thiazide therapy might promote increased aldosterone levels because of decreased intravascular volume.15 The combination of spironolactone with a thiazide diuretic results in improved diuresis and blood pressure control, in addition to prevention of the thiazide-induced hypokalemia and hypomagnesemia.8
In addition, spironolactone and eplerenone are used in the treatment of patients demonstrating “aldosterone escape,” which results from incomplete aldosterone blockade during antihypertensive therapy with blockers of the renin-angiotensin-aldosterone system.8,15 Aldosterone antagonists are used to promote diuresis in patients with edema and fluid overload associated with hyperaldosteronism, such as liver cirrhosis, nephrotic syndrome, and heart failure. Also, as discussed earlier, the administration of spironolactone along with an angiotensin-converting enzyme inhibitor in the treatment of patients with heart failure with poor ejection fraction results in a decrease in cardiovascular morbidity and mortality.17
Side Effects
Hyperkalemia, especially in the presence of impaired renal function, is the most serious side effect of treatment with spironolactone. In addition, the combination of spironolactone with angiotensin-converting enzyme inhibitors can exacerbate hyperkalemia in these patients.2 Because it is a nonspecific mineralocorticoid receptor antagonist, spironolactone can block androgen and progesterone receptors, leading to gynecomastia and breast tenderness8 that could prompt patients to seek cessation of therapy.17
Dopamine Receptor Agonists
Dopamine receptor agonists, such as dopamine and fenoldopam, result in natriuresis and increased renal blood flow via their actions on renal tubular dopamine-1 (D1) receptors.
Pharmacokinetics and Pharmacodynamics
Endogenous dopamine is synthesized locally in the epithelial cells of the renal tubules and exerts its effect directly.3 At low concentrations, dopamine produces its clinical effect via activation of dopamine receptors. Activation of D1receptors in the proximal renal tubule and in the loop of Henle increases cyclic adenosine monophosphate formation, resulting in inhibition of the Na+-H+ exchange and Na+-K+-ATPase pump.3 In addition, D1 receptors mediate an increase in renal blood flow leading to a small increase in glomerular filtration rate.3 With increasing doses of dopamine, sympathetic activation begins to predominate. β activation results in increased inotropy, increased cardiac output, and elevation in systemic blood pressure. At even higher doses, α activation prevails, leading to vasoconstriction.
Fenoldopam is a fast-acting IV antihypertensive with a short half-life of 10 minutes,3 used in the short-term treatment of patients with severe hypertension. Fenoldopam is a relatively selective D1 receptor agonist with moderate affinity to α2 receptors. It has no effect on D2, β, or α1 receptors.3 Accordingly, it results in increased renal blood flow and decreased systemic vascular resistance.20 Both dopamine and fenoldopam have poor availability after oral intake and are thus administered IV.
Clinical Uses
Dopamine is used to maintain renal blood flow in patients in cardiogenic shock with low or normal systemic vascular resistance.3 Similarly, fenoldopam is used for its renal vasodilation properties and, even at higher doses it lacks sympathetic activity, thus it is used to treat resistant hypertension.3 Both drugs have been used at very low doses to provide renal protection in high-risk patients, such as after cardiac or major vascular surgery, or following radioiodine contrast injection.20 However, large randomized trials have not found a reduction in the incidence of perioperative acute renal failure with these drugs.20,21,22
Natriuretic Peptides
Atrial natriuretic peptide and brain natriuretic peptide are normally produced in the atria and ventricles of the heart, respectively, in response to myocardial wall stretch.3 They exert their diuretic effect on the collecting duct of the kidneys by blocking the basal Na-K-ATPase channel. In the United States, nesiritide, a recombinant brain natriuretic peptide, is the only natriuretic peptide currently available. It is suggested in the management of patients with decompensated congestive heart failure,23 although data on its effect on long-term morbidity and mortality are lacking.24 It is administered IV as a continuous infusion and has a short half-life of 18 minutes.3
Vasopressin Receptor Antagonists
Vasopressin receptor antagonists, or vaptans, competitively inhibit V2 receptor in the renal collecting duct, thereby leading to decreased water reabsorption. Currently, tolvaptan is the only U.S. Food and Drug Administration–approved selective V2 receptor antagonist for the treatment of euvolemic and hypervolemic hyponatremia associated with syndrome of inappropriate antidiuretic hormone, congestive heart failure, or liver cirrhosis.25
Neprilysin Antagonists
Neprilysin (NEP) is a ubiquitous, membrane-bound metalloproteinase with greatest concentration in cardiovascular tissues and the kidneys.26 The most important function of NEP appears to be the natriuretic peptides, including atrial natriuretic peptide, brain natriuretic peptide, and C-type natriuretic peptide. The natriuretic peptides are released by cardiac and renal tissues in response to increased cardiac wall stress and volume overload, as occurs in heart failure and hypertension. The natriuretic peptides stimulate renal secretion of water and are broken down by NEP. NEP activity is increased in heart failure, leading to accelerated breakdown of natriuretic peptides. Specific NEP inhibition has been shown to increase circulating levels of natriuretic peptides, promoting natriuresis; they have also been shown to reduce the cardiovascular remodeling that is inherent to end-stage heart failure. The NEP inhibitors, used alone or in combination with other agents, may well emerge as a novel group of agents for reducing morbidity and mortality associated with advanced heart failure.
Aquaporin Modulators
Aquaporins (AQP) are recently described membrane channels facilitating water movement across cells in response to osmotic gradient.27 Subtypes of AQP respond to antidiuretic hormone (ADH) in the collecting duct of the kidney and mutations in those channels can result in hereditary nephrogenic diabetes insipidus.2,27 Other subunits located in the cerebral perivascular astrocyte end foot may be involved in cerebral edema and in the pathogenesis of neuromyelitis optica.2,27 Nephrogenic diabetes insipidus (NDI), which is characterized by polyuria and polydipsia, results from an inappropriate response to ADH. The most common form of NDI is acquired, usually secondary to lithium toxicity, hypercalcemia, or polycystic kidney disease. Hereditary NDI on the other hand is rare and can result either from an X-linked defect in V2 receptors or from an autosomal recessive AQP2 mutation.27 Treatment with thiazide diuretics in these patients helps decrease the kidney’s diluting ability.27
References
1. Roush GC, Kaur R, Ernst ME. Diuretics: a review and update. J Cardiovasc Pharmacol Ther. 2014;19(1):5–13.
2. Wile D. Diuretics: a review. Ann Clin Biochem. 2012;49(pt 5):419–431.
3. Goodman LS, Brunton LL, Chabner B, et al. Goodman & Gilman’s Pharmacological Basis of Therapeutics. 12th ed. New York, NY: McGraw-Hill; 2011.
4. Yano I, Takayama A, Takano M, et al. Pharmacokinetics and pharmacodynamics of acetazolamide in patients with transient intraocular pressure elevation. Eur J Clin Pharmacol. 1998;54(1):63–68.
5. Brater DC. Diuretic therapy. N Engl J Med. 1998;339(6):387–395.
6. Leto L, Aspromonte N, Feola M. Efficacy and safety of loop diuretic therapy in acute decompensated heart failure: a clinical review. Heart Fail Rev. 2014;19(2):237–246.
7. Felker GM, Lee KL, Bull DA, et al; NHLBI Heart Failure Clinical Research Network. Diuretic strategies in patients with acute decompensated heart failure. N Engl J Med. 2011;364(9):797–805.
8. Ernst ME, Moser M. Use of diuretics in patients with hypertension. N Engl J Med. 2009;361(22):2153–2164.
9. Mehta RL, Pascual MT, Soroko S, et al; PICARD Study Group. Diuretics, mortality, and nonrecovery of renal function in acute renal failure. JAMA. 2002;288(20):2547–2553.
10. Havdal HS, Borison RL, Diamond BI. Potential hazards and applications of lithium in anesthesiology. Anesthesiology. 1979;50: 534–537.
11. Duarte JD, Cooper-DeHoff RM. Mechanisms for blood pressure lowering and metabolic effects of thiazide and thiazide-like diuretics. Expert Rev Cardiovasc Ther. 2010;8(6):793–802.
12. ALLHAT Officers and Coordinators for the ALLHAT Collaborative Research Group. Major outcomes in high-risk hypertensive patients randomized to angiotensin-converting enzyme inhibitor or calcium channel blocker vs diuretic: the Antihypertensive and Lipid-Lowering Treatment to Prevent Heart Attack Trial (ALLHAT). JAMA. 2002;288(23):2981–2997.
13. Shawkat H, Westwood M-M, Mortimer A. Mannitol: a review of its clinical uses. Contin Educ Anaesth Crit Care Pain. 2012;12(2):82–85.
14. Ravissin P, Abou-Madi M, Archer D, et al. Changes in CSF pressure after mannitol in patients with and without elevated CSF pressure. J Neurosurg. 1988;69:869–876.
15. Epstein M, Calhoun DA. Aldosterone blockers (mineralocorticoid receptor antagonism) and potassium-sparing diuretics. J Clin Hypertens. 2011;13(9):644–648.
16. Burrows EF, Southern KW, Noone PG. Sodium channel blockers for cystic fibrosis. Cochrane Database Syst Rev. 2014;4:CD005087.
17. Pitt B, Zannad F, Remme WJ, et al. The effect of spironolactone on morbidity and mortality in patients with severe heart failure. N Engl J Med. 1999;341(10):709–717.
18. Pitt B, Pfeffer MA, Assmann SF, et al; TOPCAT Investigators. Spironolactone for heart failure with preserved ejection fraction. N Engl J Med. 2014;370(15):1383–1392.
19. Pitt B, Remme W, Zannad F, et al; Eplerenone Post-Acute Myocardial Infarction Heart Failure Efficacy and Survival Study Investigators. Eplerenone, a selective aldosterone blocker, in patients with left ventricular dysfunction after myocardial infarction. N Engl J Med. 2003;348(14):1309–1321.
20. Bove T, Landoni G, Calabro MG, et al. Renoprotective action of fenoldopam in high-risk patients undergoing cardiac surgery: a prospective, double-blind, randomized clinical trial. Circulation. 2005;111(24):3230–3235.
21. O’Hara JF Jr, Mahboobi R, Novak SM, et al. Fenoldopam and renal function after partial nephrectomy in a solitary kidney: a randomized, blinded trial. Urology. 2013;81(2):340–345.
22. Zangrillo A, Biondi-Zoccai GG, Frati E, et al. Fenoldopam and acute renal failure in cardiac surgery: a meta-analysis of randomized placebo-controlled trials. J Cardiothorac Vasc Anesth. 2012;26(3), 407–413.
23. Publication Committee for the VMAC Investigators. Intravenous nesiritide vs nitroglycerin for treatment of decompensated congestive heart failure: a randomized controlled trial. JAMA. 2002; 287(12):1531–1540.
24. Chen HH, Sundt TM, Cook DJ, et al. Low dose nesiritide and the preservation of renal function in patients with renal dysfunction undergoing cardiopulmonary-bypass surgery: a double-blind placebo-controlled pilot study. Circulation. 2007;116(11)(suppl):I-134–I-138.
25. Lehrich RW, Greenberg A. Hyponatremia and the use of vasopressin receptor antagonists in critically ill patients. J Intensive Care Med. 2012;27(4):207–218.
26. von Lueder TG, Atar D, Krum H. Current role of neprilysin inhibitors in hypertension and heart failure. Pharmacol Ther. 2014; 144(1):41–49.
27. Verkman AS, Anderson MO, Papadopoulos MC. Aquaporins: important but elusive drug targets. Nat Rev Drug Discov. 2014;13(4): 259–277.