
Beth H. Shaz1,2, Richard O. Francis1,3 & Christopher D. Hillyer1,4
1New York Blood Center, New York, NY, USA
2Emory University School of Medicine, Atlanta, GA, USA
3Columbia University Medical Center, New York, NY, USA
4Weill Cornell Medical College, New York, NY, USA
Transfusion-associated graft-versus-host disease
Transfusion-associated graft-versus-host disease (TA-GVHD) is an uncommon yet highly fatal complication of cellular blood component transfusion; cellular components are defined as red blood cell (RBC), platelet and granulocyte components (not fresh frozen plasma). TA-GVHD is defined by the UK haemovigilance system Serious Hazards of Transfusion (SHOT) as fever, rash, liver dysfunction, diarrhoea and pancytopenia occurring 1–6 weeks after transfusion, without other apparent cause (similarly the US National Healthcare Safety Network Biovigilance system definition for definitive diagnosis is fever, rash, hepatomegaly, diarrhoea between 2 days and 6 weeks after transfusion with laboratory evidence of liver dysfunction, pancytopenia, leucocyte chimerism and findings of TA-GVHD on skin or liver biopsy). Development of TA-GVHD requires the product to contain immunologically competent lymphocytes and the recipient must express tissue antigens absent in the donor and must be incapable of mounting an effective immune response to destroy the foreign lymphocytes. Cellular blood products contain viable lymphocytes that can proliferate and result in TA-GVHD. Inactivation of these lymphocytes, usually through irradiation, prevents TA-GVHD. The identification of individuals at high risk for TA-GVHD, such as immune-impaired patients or those receiving products from relatives, and the subsequent requirement that these individuals receive irradiated products, reduces the incidence of TA-GVHD, but its elimination requires universal irradiation or lymphocyte inactivation of all cellular blood components.
Pathogenesis
TA-GVHD results from the engraftment of transfused donor T-lymphocytes in a recipient whose immune system is unable to reject them. The mechanism of TA-GVHD is similar to that of acute GVHD after haemopoietic stem cell (HSC) transplantation. Donor T-lymphocytes recognize recipient HLA antigens as foreign, resulting in activation and proliferation of the lymphocytes, which leads to host cell death and tissue destruction.
Clinical features
TA-GVHD is an acute illness characterized by fever, rash, pancytopenia, diarrhoea and liver dysfunction which begins 4–30 days (median 8–10 days) after transfusion and results in death within 3 weeks from symptom onset in over 90% of the cases [1]. In neonates the clinical manifestations are similar, yet the interval between transfusion and onset is longer; the median time of onset of fever is 28 days, rash 30 days and death 51 days [2]. In the typical scenario, fever is the presenting symptom followed by an erythematous maculopapular rash, which begins on the face and trunk and spreads to the extremities. Liver dysfunction manifests as an obstructive jaundice or an acute hepatitis. Gastrointestinal complications include nausea, anorexia or diarrhoea. Leucopenia and pancytopenia, the primary reason for death resulting from sepsis, candidiasis and multiorgan failure, develop later and progressively become more severe.
Diagnosis
The diagnosis of TA-GVHD is based on the characteristic clinical manifestations, pathologic findings on tissue biopsy, and, if possible, evidence of donor-derived lymphocytes in the recipient's blood or affected tissues. Laboratory data demonstrate pancytopenia and abnormal liver function tests. Skin biopsy changes include epidermal basal cell vacuolization and mononuclear cell infiltration. Liver biopsy findings include degeneration of the small bile ducts, periportal mononuclear infiltrates and cholestasis. The bone marrow is usually hypocellular or aplastic, which is the primary differentiating feature between TA-GVHD and GVHD occurring after HSC transplantation. The discovery of donor lymphocytes or DNA in the patient's peripheral blood or tissue biopsy with the appropriate clinical scenario confirms the diagnosis. Donor-derived DNA is usually detected using polymerase chain reaction (PCR)-based HLA typing; other methods include the use of amplified fragment length polymorphisms, variable-number tandem repeat analysis, short tandem repeat analysis, microsatellite markers and cytogenetics.
Treatment
Most treatments of TA-GVHD are largely ineffective including aggressive use of corticosteroids, antithymocyte globulin, ciclosporin and growth factors. However, spontaneous resolution and successful treatment with a combination of ciclosporin, steroids and OKT3 (anti-CD3 monoclonal antibody) or antithymocyte globulin have been reported. Transient improvement has been seen with nafamostat mesilate, a serine protease inhibitor that inhibits cytotoxic T-lymphocytes. There are case reports of successful treatment with autologous or allogeneic HSC transplantation.
Prevention
Since treatment options for TA-GVHD are mostly unsuccessful, patients at increased risk must be identified and transfused with lymphocyte inactivated products, usually by gamma-irradiation or pathogen inactivation technologies. Gamma-radiation is derived from decay of radioactive isotopes, such as caesium-137 or cobalt-60. Properly installed and maintained radioisotope instruments are safe, but their use requires appropriate security, radiation safety protocols and training (in the USA, blood irradiators are regulated by the Nuclear Regulatory Commission). Some pathogen reduction technologies have been shown in human clinical trials, mouse models and other lymphocyte proliferation assays to inactivate T-lymphocytes (Table 11.1). Gamma-irradiation is the most common method used for irradiation to prevent TA-GVHD; in Europe the use of pathogen inactivation for platelets is growing, and irradiation by X-ray generated by linear acceleration is increasing in the USA as a non radionuclide source.
Table 11.1 Potential methods for leucocyte inactivation.
|
Method |
Leucocyte inactivation |
|
Ultraviolet B |
Inhibits TA-GVHD in dog transfusion model |
|
8-Methoxypsoralen with UV |
Inhibits activation and proliferation |
|
Aminomethyl trimethylpsoralen with UVA |
Inhibits activation and proliferation |
|
Amotosalen (S-59) with UVA |
Inhibits activation and proliferation |
|
Inhibits TA-GVHD in murine transfusion model |
|
|
Methylene blue with light |
Does not inactivate leucocytes |
|
Dimethylmethylene blue with light |
No data on leucocyte inactivation |
|
Riboflavin with UV |
Inhibits proliferation |
|
Inactine (PEN 110) |
Inhibits TA-GVHD in murine transfusion model |
|
Inhibits activation and proliferation |
|
|
Thionine with UVB |
Inhibits proliferation |
|
Adapted by permission from Macmillan Publishers Ltd, Bone Marrow Transplant 2004, 33(1): 1–7, copyright 2004. |
|
Source and dose of ionizing radiation
Both gamma-rays and X-rays inactivate T-lymphocytes and can be used to irradiate blood components. Usually gamma-rays originate from caesium-137 or cobalt-60 while X-rays are generated from linear accelerators. Quality assurance measures should be performed, including dose mapping, adjustment of irradiation time to correct for isotopic decay, assurance of no radiation leakage, timer accuracy, turntable operation, preventive maintenance and a qualitative indicator label to confirm that blood products have been properly irradiated.
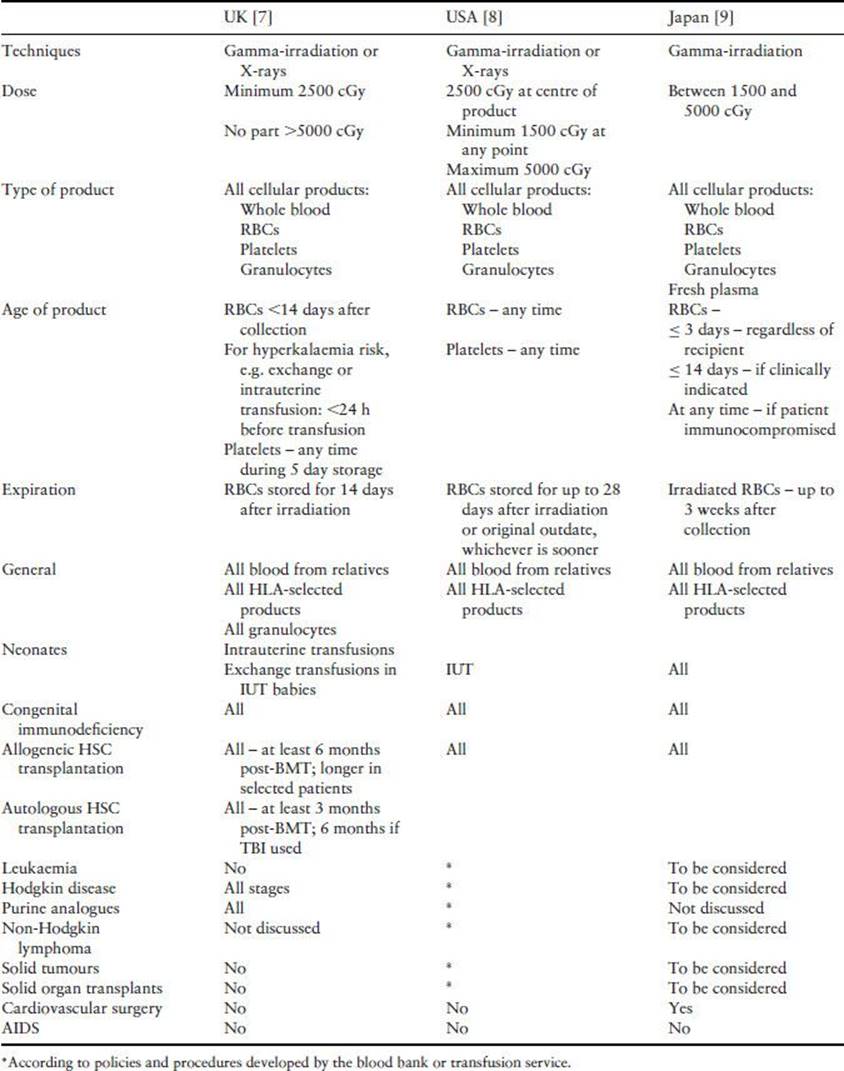
The dose of irradiation must be sufficient to inhibit lymphocyte proliferation but not significantly damage RBCs, platelets and granulocytes or their functions. Assays to assess the effect of irradiation on T-lymphocyte proliferation include mixed lymphocyte culture (MLC) assay and limiting dilution analysis (LDA). The recommended dose varies between 15 and 50 Gy (Table 11.2). Of note, there have been three patients transfused with irradiated blood products, two at doses of 20 Gy [3,4] and one at 15 Gy [5], who developed TA-GVHD, but it is unknown if there was a process or dose failure.
Table 11.2 Comparison of irradiation guidelines, including dose and indications.
Adverse effects of irradiation
At recommended doses, radiation causes some oxidation and damage to lipid components of membranes, which continues during storage. Products irradiated immediately prior to transfusion appear to be unaffected and have virtually normal function. In stored products, radiation modestly harms RBCs, but does not appear to affect platelet and granulocyte function significantly in the clinically utilized doses. The effects on RBCs include an increase in extracellular potassium and a decrease in posttransfusion RBC survival. The increase in extracellular potassium is usually not of clinical significance because of posttransfusion dilution of the potassium. However, there may be certain patients who are sensitive to the increased potassium resulting in transfusion-associated hyperkalemia, such as premature infants, infants receiving large RBC volumes and fetuses receiving intrauterine transfusions (IUT), neonatal exchange transfusions or intracardiac transfusions via central line catheters. The potassium increase can be prevented by either irradiating the RBC product within 24 hours of infusion or washing the RBC product prior to transfusion. Also RBC products stored in additive solutions have lower extracellular potassium than CPDA-1 units of a similar age. The in vivo viability of irradiated RBCs evaluated at 24-hour recovery is reduced by 3–10% compared to nonirradiated RBCs [6]. As a consequence, RBC product outdate is variably shortened to 14–28 days after irradiation (Table 11.2).
Blood component factors
Age of blood
Use of fresh blood increases the risk of TA-GVHD. A Japanese series of cases of TA-GVHD in immunocompetent patients found that 62% of patients had received blood less than 72 hours old [1] and a US series found about 90% of cases received blood less than 4 days old [10]. The increased risk with fresh blood is possibly due to the function and viability of lymphocytes as during storage these cells undergo apoptosis and fail to stimulate an MLC response. Therefore, older blood may be less likely to cause TA-GVHD.
Leucocyte dose
Leucocyte reduction of blood components may decrease the risk of TA-GVHD, but it does not eliminate it. SHOT data reported a decrease in the number of TA-GVHD cases following universal leucocyte reduction of blood components in the UK in 1999 [11].
Blood components
All cellular blood components, including RBCs, platelets, granulocytes, whole blood and fresh plasma (not frozen plasma) contain viable T-lymphocytes that are capable of causing TA-GVHD (Table 11.2). Granulocyte transfusions are the highest risk product because they have a high lymphocyte count and are administered fresh to neutropenic and immunosuppressed patients. Therefore, it is recommended that all granulocyte products undergo irradiation prior to transfusion and the remaining cellular blood components be irradiated for patients at increased risk.
Patients at increased risk
Patient populations have varying risk factors for developing TA-GVHD (Table 11.3). It is difficult to quantify any of these risks because the number of these patients, the number who are transfused or the number of transfusions or type of products received are unknown. The risk is therefore derived from case reports or haemovigilance data, which is biased by underrecognition, misdiagnosis and under- and passive reporting.
Table 11.3 Indications for irradiated cellular blood components to prevent TA-GVHD.
|
Clear indications |
|
Congenital immunodeficiency syndromes (suspected or known) |
|
Allogeneic and autologous haemopoietic progenitor cell transplantation |
|
Transfusions from blood relatives |
|
HLA-matched or partially HLA-matched products (platelet transfusions) |
|
Granulocyte transfusions |
|
Hodgkin disease |
|
Treatment with purine analogue drugs (fludarabine, cladribine and deoxycoformycin) |
|
Treatment with Campath (anti-CD52) and other drugs/antibodies that affect T-lymphocyte number or function |
|
Intrauterine transfusions |
|
Indications deemed appropriate by most authorities |
|
Neonatal exchange transfusions |
|
Pre-term infants/low birthweight infants |
|
Infant/child with congenital heart disease (secondary to possible DiGeorge syndrome) |
|
Acute leukaemia |
|
Non-Hodgkin lymphoma and other haematologic malignancies |
|
Aplastic anaemia |
|
Solid tumours receiving intensive chemotherapy and/or radiotherapy |
|
Recipient and donor pair from a genetically homogeneous population |
|
Indications unwarranted by most authorities |
|
Solid organ transplantation |
|
Healthy newborns/term infants |
|
HIV/AIDS |
Congenital immunodeficiency patients
The first reported cases of TA-GVHD occurred in the 1960s in children with T-lymphocyte congenital immunodeficiency syndromes. Children with severe congenital immunodeficiency syndromes (SCID) and with variable immunodeficiency syndromes, such as Wiskott–Aldrich and DiGeorge syndromes, have developed TA-GVHD. These children may be transfused prior to the recognition of these immunodeficiency syndromes, which has been reported in two infants in Canada. Because of the possibility of the patient not being known to be immunodeficient, it may be prudent to irradiate all blood components for children under a certain age. This is particularly true with infants undergoing cardiac surgery who may have unrecognized DiGeorge syndrome. In three reported cases of TA-GVHD in SCID patients, allogeneic HSC transplantation was successful in treating the disease. It is recommended that all patients with suspected or confirmed congenital immunodeficiency receive irradiated products.
Allogeneic and autologous HSC recipients
Both allogeneic and autologous HSC transplant recipients are at increased risk of TA-GVHD. Patients who undergo allogeneic HSC transplantation have received irradiated blood products routinely for over 40 years. Multiple organizations, including The European School of Haematology (ESH), European Group for Blood and Marrow Transplantation (EMBT) and Foundation for the Accreditation of Cellular Therapy (FACT), recommend irradiated blood products for allogeneic and autologous HSC recipients, but it is unclear for how long before and after transplantation these patients require irradiated blood products.
Leukaemia and lymphoma patients
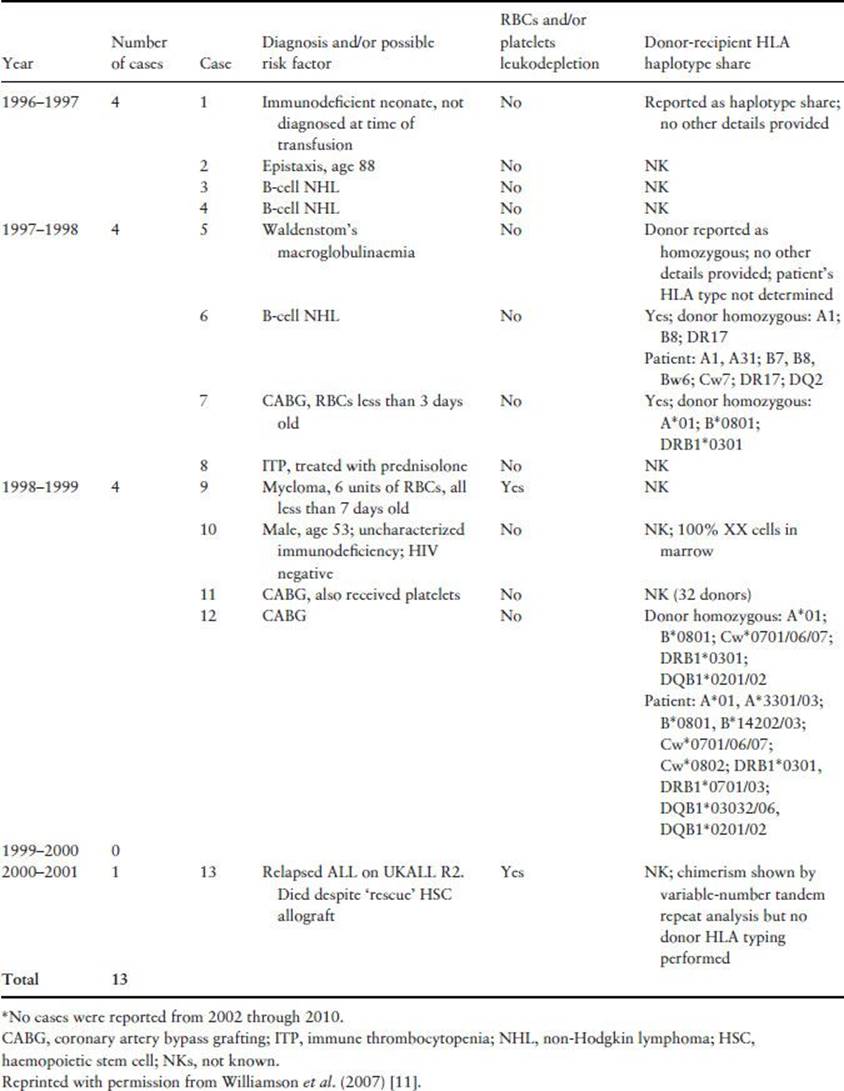
Patients with haematologic malignancies are at increased risk for TA-GVHD, especially patients with Hodgkin disease (HD). Twenty cases were reported in patients with malignant lymphoma, 13 in association with HD and 7 with non-Hodgkin lymphoma (NHL), and all undergoing therapy for active disease at the time. Five of thirteen cases reported to SHOT were associated with haematologic malignancies (Table 11.4). In the 1970s and 1980s, cases of TA-GVHD occurred in patients with acute leukaemia undergoing chemotherapy; the majority of these patients had received granulocyte transfusions. It is recommended that patients with haematological malignancies receive irradiated products; however, it is less clear if this requirement should be only during active treatment.
Table 11.4 Cases of TA-GVHD reported to SHOT 1996 through 2001.*
Recipients of fludarabine and other purine analogues as well as other drugs/antibodies that affect T-lymphocyte number or function
TA-GVHD was initially reported in patients with CLL receiving fludarabine, a purine analogue that results in profound lymphopenia. There are nine cases of TA-GVHD in CLL, AML and NHL patients who received fludarabine up to 11 months prior to transfusion. In addition, TA-GVHD occurred in one patient who received fludarabine for autoimmune disease. Other purine analogues, including deoxycoformycin (pentostatin) and chlorodeoxyadenosine (cladribine), have been associated with the development of TA-GVHD. Thus, it is recommended that all patients who have received fludarabine or other purine analogues as well as Campath (anti-CD52) or other drugs/antibodies that affect T-lymphocyte function or number be transfused with irradiated products; however, it is unclear if this requirement should only be for at least one year and until recovery from the resulting lymphopenia following the administration of these drugs.
Fetus and neonate
Fetuses and neonates have immature immune systems and may be at increased risk of TA-GVHD. In neonates, most cases of TA-GVHD reported are in those with congenital immunodeficiency or that received products from related donors. At least ten cases have been reported after neonatal exchange transfusions; four occurred in infants who had previously received IUT. Seven cases were in preterm infants (excluding those who received a product from a relative). A single case report involved a full-term infant receiving extracorporeal membrane oxygenation (ECMO). The use of irradiated products for fetal and neonatal transfusions is recommended for exchange transfusions and IUT, preterm infants, infants with congenital immunodeficiency and those receiving products from relatives; its need is less clear for other neonatal transfusions.
Patients with aplastic anaemia
Since patients with aplastic anaemia are usually treated with intensive chemotherapy regimens and possible HSC transplantation, some authorities recommend they receive irradiated products, especially during myelosuppressive therapy or treatment with antithymocyte globulin.
Patients receiving chemotherapy and immunotherapy
TA-GVHD has occurred in patients with solid tumours, including neuroblastoma, rhabdomyosarcoma and bladder and small cell lung cancer, during intensive myeloablative therapy. Therefore, it is recommended that patients with solid tumours receive irradiated products, especially during myelosuppressive therapy.
Solid organ transplantation recipients
GVHD is a rare complication of solid organ transplantation, which usually results from the passenger lymphocytes contained within the solid organ and not from transfusion, even though these individuals are highly immunosuppressed and transfused. There have been four cases of TA-GVHD in solid organ transplant recipients; one was a liver transplant recipient with pre-existing pancytopenia, one a heart transplant recipient and two were inconclusive cases in kidney transplant recipients. The risk of TA-GVHD in solid organ transplant recipients appears low and the use of irradiated products is generally considered to be unwarranted.
Human immunodeficiency virus (HIV) and acquired immunodeficiency syndrome (AIDS) patients
HIV/AIDS is not considered a risk factor for TA-GVHD as there is only a single case report of a child with AIDS developing transient TA-GVHD. It is postulated that HIV infects the transfused T-lymphocytes and thus prohibits the donor lymphocytes from engrafting. The use of irradiated blood products in HIV/AIDS patients is not warranted, but approximately a quarter of institutions in the USA choose to take this precaution, probably because of the immunosuppresive nature of HIV/AIDS and the high degree of fatality of TA-GVHD.
Cardiovascular surgery patients
Prior to the Japanese changing their irradiation policies, their reported incidence of TA-GVHD following cardiovascular surgery was 0.15–0.47%. Fifty-six of the 122 cases of TA-GVHD reported in Japan from 1985 to 1993 were patients after cardiovascular surgery; 28% used blood from a relative and 72% used blood less than 72 hours old [1]. They also reported a lower risk for women than men, possibly secondary to women having previous exposure to leucocytes during pregnancy and childbirth. There are five cases reported in the UK (Table 11.4) and one in the USA [12]. Possible reasons for the increased risk are that the RBC products are usually less than 72 hours old and cardiac surgery may result in reduced cell-mediated immunity. The recommendation for irradiated products is warranted in Japan but not in the USA or UK at this time.
Immunocompetent patients
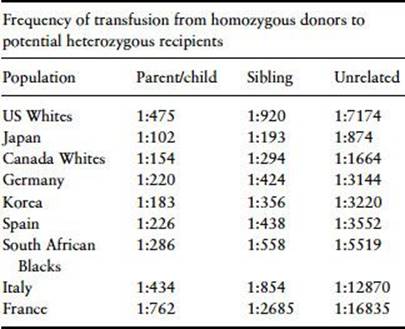
TA-GVHD has been reported in immunocompetent patients, especially those who received transfusions of blood products donated by close relatives. The majority of cases reported in immunocompetent patients occurred with the use of fresh whole blood from a close relative [13]. In a review of 122 cases of TA-GVHD in immunocompetent Japanese patients, 67% had not received products from a related donor and of the 66 noncardiovascular surgery patients, 39 had solid tumours and 27 had other conditions [1]. The risk of receiving a blood product from a homozygous donor is greatest in populations with limited HLA haplotype polymorphisms, such as Japan [14] (Table 11.5). The frequency of reported cases is substantially lower than these estimates, which may be a result of unrecognized and/or unreported cases, lymphocytes in blood products that are either nonviable or insufficient to cause disease and/or recipients who may be able to destroy the donor lymphocytes based on minor HLA differences between the donor and recipient. Irradiation of products from close relatives and HLA matched products is recommended, but the risk is minimal for other immunocompetent patients.
Table 11.5 Frequency of homozygous HLA donors in various populations.
Guidelines and requirements for irradiated products
In 1989, AABB institutional members were surveyed about their blood product irradiation practices [15]. Approximately 10.1% of the products transfused were irradiated, which has remained fairly constant. The indications included patients with allogeneic HSC transplantation (88%), autologous HSC transplantation (81.4%), congenital immunodeficiency syndrome (68.4%), premature newborn (53.9%), leukaemia (51.4%), organ transplantation (40.4%), HD (34.0%), NHL (32.0%), HLA matched product (31.0%), AIDS (24.5%), term newborn (24.0%) and solid tumour (20.0%). This survey highlighted the need for guidelines. In 1996, the American Society for Clinical Pathology and the UK published guidelines for the use of irradiation to prevent TA-GVHD; the UK guidelines were updated in 2010 [7] (Table 11.2). Japan has elected to irradiate all blood products.
Only two of the 13 TA-GVHD cases reported to SHOT fulfilled the current UK guideline criteria for irradiated blood products, which highlights the need to continually monitor and revise the definition of high-risk individuals. The remaining 11 patients may have had some degree of unrecognized immunosuppression or shared HLA haplotypes with the donors, potentially demonstrating the need for universal irradiation.
Universal irradiation
As case reports cited above indicate, TA-GVHD can occur in immunocompetent patients and individuals where the degree of immunocompromise was not known or properly identified prior to transfusion. Given that TA-GVHD is fatal in almost all cases and the risk of radiation of a product includes only minimal cost and effect on product potency, many authorities consider that the cost : benefit ratio is weighted in favour of universal irradiation. Consideration of universal irradiation should be undertaken on a local, regional or national basis, as appropriate.
Haemovigilance
Some countries have begun comprehensive tracking systems for adverse events of blood transfusion (Chapter 18). SHOT data from 1996 to 2005 revealed that 11 cases of TA-GVHD occurred with the use of non-leucocyte-reduced and two cases with leucocyte-reduced products (Table 11.4). No additional cases have been reported through 2010. In addition there were 405 reports where irradiated products were indicated and were not used due to error. From 1992 to 2000, two cases of TA-GVHD have been reported to Health Canada with the addition of 1–2 cases that were presented but not reported. Irradiated blood products were used in Canada for highly immunocompromised patients and patients receiving directed donation from close relatives. With this information, the risk of TA-GVHD in Canada is estimated to be less than 1 per million products transfused. The continued occurrence of TA-GVHD is likely to be from lack of agreement on the level of immunodeficiency that results in increased risk and patients with immunocompromised conditions who receive nonirradiated products either secondary to not being identified prior to transfusion or the product not being irradiated by error. On the other hand, the low incidence reported may be secondary to underreporting and/or underrecognition, the fact that lymphocytes are no longer capable of proliferating because the blood is older by the time of transfusion, the risk decreasing by leucocyte reduction of blood products and the genetic heterogeneity of Canadians.
Transfusion-associated microchimerism
Chimerism is defined as the presence of two genetically distinct cell lines in a single organism. Haemopoietic chimerism refers to the persistence of allogeneic donor lymphocytes in a recipient. Microchimerism (MC) occurs when these donor cells represent a small population (less than 5%) and can be a consequence of pregnancy, organ transplantation or transfusion. With increased sensitivity of methods, MC can be detected not infrequently after transfusion, but the conditions that facilitate and consequences of this phenomenon are unknown.
Normal clearance of transfused lymphocytes
In a study investigating the clearance of lymphocytes in immunocompetent recipients, three phases were found: first, 99.9% of the lymphocytes were cleared over the first 2 days, second, there was a 1-log increase in the number of circulating donor lymphocytes on days 3–5 and, lastly, there was a secondary clearance [16]. It was postulated that this transient increase in donor lymphocytes represents one arm of an in vivo mixed lymphocyte reaction with activated donor T-lymphocytes proliferating in reaction to HLA-incompatible recipient cells.
Clinical data
TA-MC has been reported mostly in trauma patients [17], but has also been reported in sickle cell disease and thalassemia patients. HIV-positive individuals do not have sustained TA-MC. Irradiation of products prevents TA-MC. Leucocyte reduction of blood products is reported not to decrease the incidence of TA-MC among trauma patients [18]. In addition, TA-MC can be sustained for decades after transfusion [19]. Age, gender, injury severity score, splenectomy and number of units transfused did not correlate with the establishment of TA-MC in trauma patients. When patients were evaluated for symptoms suggestive of chronic GVHD several months after transfusion, TA-MC did not correlate with these symptoms. One study reported a decrease in donor-specific lymphocyte response in TA-MC trauma patients versus non-TA-MC patients [20]. TA-MC may occur, especially in trauma patients, but its conditions and consequences are unknown.
Testing for TA-MC
Detection of TA-MC requires the ability to detect small amounts of minor population DNA among large amounts of host DNA and selection of optimal genetic differences. One technique is to use real-time PCR. Initially this technique was used to detect the Y chromosome in women who received blood transfusions from at least one male donor. This has been expanded to a panel of 12 HLA-DR polymorphisms. A third improvement was the addition of a panel of 12 insertion/deletion (InDel) polymorphisms.
Testing limitations
The ability to detect TA-MC is limited by sample volume and sampling error. Large sample volume creates too much DNA and results in difficulties in testing. Sampling error is likely when an extremely low level of TA-MC exists. Techniques that look for the Y chromosome in women transfused with male blood components are of limited value, because this can result from the previous carrying of a male fetus. Because the clinical significance, if any, of TA-MC remains unknown, molecular testing is for research purposes.
Clinical consequences
To date, no clear relationship of TA-MC to clinical outcomes has been elucidated. To determine the association between TA-MC and autoimmune or other diseases, important confounding factors need to be considered, and long follow-up times are needed as these diseases can take years to develop and may result in vague symptoms. Currently, the conditions that facilitate TA-MC and its consequences remain to be established.
Key points
1. TA-GVHD is a rare yet highly fatal complication of cellular blood component transfusion.
2. TA-GVHD can be prevented by using irradiated or leucocyte-inactivated blood components.
3. Patients at increased risk for TA-GVHD include those who are immune impaired and those receiving blood components donated from relatives.
4. Leucocyte dose and age of the blood component, HLA matching between the donor and the recipient and immune state of the recipient contribute to the likelihood of developing TA-GVHD.
5. While there is strong data for providing irradiated blood components to prevent TA-GVHD in some patient populations, the need for irradiation in other disease states is less clear (refer to Table 11.3).
6. With increased sensitivity of methods to detect chimerism, microchimerism can be detected not infrequently after transfusion, but the conditions that facilitate it and its clinical consequences are unknown.
References
1. Ohto H & Anderson KC. Survey of transfusion-associated graft-versus-host disease in immunocompetent recipients. Transfus Med Rev 1996; 10: 31–43.
2. Ohto H & Anderson KC. Posttransfusion graft-versus-host disease in Japanese newborns. Transfusion 1996; 36: 117–123.
3. Drobyski S, Thibodeau S, Truitt RL et al. Third-party-mediated graft rejection and graft-versus-host disease after T-cell-depleted bone marrow transplantation, as demonstrated by hypervariable DNA probes and HLA-DR polymorphism. Blood 1989; 74: 2285–2294.
4. Sproul AM, Chalmers EA, Mills KI et al. Third party mediated graft rejection despite irradiation of blood products. Br J Haematol 1992; 80: 251–252.
5. Lowenthal RM, Challis DR, Griffiths AE et al. Transfusion-associated graft-versus-host disease: report of an occurrence following the administration of irradiated blood. Transfusion 1993; 33: 524–529.
6. Davey RJ, McCoy NC, Yu M et al. The effect of prestorage irradiation on posttransfusion red cell survival. Transfusion 1992; 32: 525–528.
7. Treleaven J, Gennery A, Marsh J et al. Guidelines on the use of irradiated blood components prepared by the British committee for standards in haematology blood transfusion task force. Br J Haematol 2011; 152: 35–51.
8. Roback JD (ed.). Technical Manual: AABB, 17th edn. Bethesda, MD: AABB; 2011, pp. 753–755.
9. Asai T, Inaba S, Ohto H et al. Guidelines for irradiation of blood and blood components to prevent post-transfusion graft-vs.-host disease in Japan. Transfus Med 2000; 10: 315–320.
10. Petz LD, Calhoun L, Yam P et al. Transfusion-associated graft-versus-host disease in immunocompetent patients: report of a fatal case associated with transfusion of blood from a second-degree relative, and a survey of predisposing factors. Transfusion 1993; 33: 742–750.
11. Williamson LM, Stainsby D, Jones H et al. The impact of universal leukodepletion of the blood supply on hemovigilance reports of posttransfusion purpura and transfusion-associated graft-versus-host disease. Transfusion 2007; 47: 1455–1467.
12. Triulzi D, Duquesnoy R, Nichols L et al. Fatal transfusion-associated graft-versus-host disease in an immunocompetent recipient of a volunteer unit of red cells. Transfusion 2006; 46: 885–888.
13. Agbaht K, Altintas ND, Topeli A et al. Transfusion-associated graft-versus-host disease in immunocompetent patients: case series and review of the literature. Transfusion 2007; 47: 1405–1411.
14. Ohto H, Yasuda H, Noguchi M et al. Risk of transfusion-associated graft-versus-host disease as a result of directed donations from relatives. Transfusion 1992; 32: 691–693.
15. Anderson KC, Goodnough LT, Sayers M et al. Variation in blood component irradiation practice: implications for prevention of transfusion-associated graft-versus-host disease. Blood 1991; 77: 2096–2102.
16. Lee TH, Donegan E, Slichter S et al. Transient increase in circulating donor leukocytes after allogeneic transfusions in immunocompetent recipients compatible with donor cell proliferation. Blood 1995; 85: 1207–1214.
17. Utter GH, Owings JT, Lee TH et al. Blood transfusion is associated with donor leukocyte microchimerism in trauma patients. J Trauma 2004; 57: 702–708.
18. Utter GH, Nathens AB, Lee TH et al. Leukoreduction of blood transfusions does not diminish transfusion-associated microchimerism in trauma patients. Transfusion 2006; 46: 1863–1869.
19. Utter GH, Lee TZ, Rivers RM et al. Microchimerism decades after transfusion among combat-injured US veterans from the Vietnam, Korean, World War II conflicts. Transfusion 2008; 48: 1609–1615.
20. Utter GH, Owings JT, Lee TZ et al. Microchimerism in transfused trauma patients is associated with diminished donor-specific lymphocyte response. J Trauma 2005; 58: 925–932.
Further reading
Corash L & Lin L. Novel processes for inactivation of leukocytes to prevent transfusion-associated graft-versus-host disease. Bone Marrow Transplant 2004; 33: 1–7.
Hume HA & Preiksaitis JB. Transfusion associated graft-versus-host disease, cytomegalovirus infection and HLA alloimmunization in neonatal and pediatric patients. Transfus Sci 1999; 21: 73–95.
Marschner S, Fast LD, Baldwin WM et al. White blood cell inactivation after treatment with riboflavin and ultraviolet light. Transfusion 2010; 50: 2489–2498.
Mintz PD & Wehrli G. Irradiation eradication and pathogen reduction. Ceasing cesium irradiation of blood products. Bone Marrow Transplant 2009; 44: 205–211.
Moroff G & Luban NLC. The irradiation of blood and blood components to prevent graft-versus-host disease: technical issues and guidelines. Transfus Med Rev 1997; 11: 15–26.
Ruhl H, Bein G & Sachs UJH. Transfusion-associated graft-versus-host disease. Transfus Med Rev 2009; 23: 62–71.
Triulzi DJ & Nalesnik MA. Microchimerism, GVHD, and tolerance in solid organ transplantation. Transfusion 2001; 41: 419–426.
Utter GH, Reed WF, Lee TH & Busch MP. Transfusion-associated microchimerism. Vox Sanguinis 2007; 93: 188–195.