
Lise J. Estcourt1, Simon J. Stanworth1 & Michael F. Murphy2
1NHS Blood and Transplant, John Radcliffe Hospital, Oxford, UK
2University of Oxford and NHS Blood and Transplant and Department of Haematology, John Radcliffe Hospital, Oxford, UK
Background
Patients with haematological diseases are major users of blood components. Haematological diseases requiring transfusion support cover a whole spectrum of clinical disorders: fetal, neonatal and paediatric practice (Chapter 32), haemoglobinopathies (Chapter 29), haemophilia (Chapter 25), immune disorders (Chapter 31) and bone marrow failure syndromes, in addition to haematological malignancies.
The haemopoietic system has a dramatic capacity for increasing the production of blood cells, but this capability varies between different diseases. The scenario of anaemia related to marrow ablation following chemotherapy is very different to anaemia in an individual with a well-compensated chronic haemolytic process. Although over 15% of all red cell units are transfused to patients with haematological disease, most are to patients with malignant disorders [1]. The requirement for blood transfusions in this group is related to both the underlying condition itself and the myelosuppressive/myeloablative effects of the specific treatments used.
This chapter considers the following topics:
· the indications for red cell, platelet and granulocyte transfusions in haematology patients and
· the approaches to the management and prevention of complications associated with transfusions in haematology patients, including the use of special types of blood components.
Red cell transfusions
The ready availability of red cell components means that anaemia can be easily treated. There are some special considerations in the management of anaemia that are applicable to haematology patients, as well as other clinical groups.
· The cause should be established and treatment other than blood transfusion should be used where appropriate, e.g. in patients with iron deficiency or megaloblastic or autoimmune haemolytic anaemia (AIHA). Anaemia of malignancy may be due to the effects of marrow infiltration or therapy, ‘inhibitory’ cytokine-mediated influences leading to the secondary anaemias (of chronic disorders) or low levels of erythropoietin.
· There is no universal ‘trigger’ for red cell transfusions, i.e. a given level of haemoglobin concentration (Hb) at which red cell transfusion is appropriate for all patients. Clinical judgement balancing factors such as quality-of-life indices play an important role in the decision to transfuse red cells or not [2].
Patients receiving intensive myelosuppressive/myeloablative treatment
There are specific considerations relating to the use of red cell transfusions in patients receiving intensive myelosuppressive/myeloablative treatment, including the need to provide a ‘reserve’ in case of severe infection or haemorrhage, and the convenience of having a standard policy for red cell transfusion in the setting of an acute haematology service, even if this may result in some patients being overtransfused.
The level of Hb used as the ‘trigger’ for transfusion varies from centre to centre but is usually in the range 8–10 g/dL. A restrictive policy is generally advocated because of the data from trials in other patient groups indicating the safety of this approach and the well-recognized risks of transfusion. There are no definite data to support the use of a higher level, although studies in animal models of thrombocytopenia and in uraemic patients suggest that correction of anaemia also results in correction of prolonged bleeding times [3].
Red cell transfusions and chronic anaemias
In patients with chronic anaemia requiring regular transfusions, red cell transfusions should be used to maintain the Hb just above the lowest level not associated with symptoms of anaemia [2]. There is considerable variation in this level depending on the patient's age, level of activity and coexisting medical problems, such as cardiovascular and respiratory disease; for example, some young patients are asymptomatic with an Hb below 7 g/dL, while some elderly patients are symptomatic even at an Hb above 10 g/dL. Special considerations apply to patients with haemoglobinopathies, and these are considered in Chapter 29.
The use of recombinant erythropoietin (RhEpo) in haematological disease
The clinical use of recombinant RhEpo might be considered in several situations in haematology patients, e.g. delayed erythroid engraftment after allogeneic bone marrow/peripheral blood progenitor cell transplantation, the treatment of anaemia in patients with myeloma or myelodysplasia, and in the management of Jehovah's Witnesses with haematological disorders. Evidence supports an association between increases in Hb, reduced red cell transfusion requirements and possibly improvement in quality-of-life indices with RhEpo therapy, although the findings concerning quality-of-life measures are more difficult to compare between studies. Uncertainties also remain about the factors predicting responsiveness, since a number of individuals fail to show adequate responses to RhEpo. However, as discussed in Chapter 46, recent systematic reviews have raised concerns about adverse events (increased morbidity and mortality) in patients treated with RhEpo [4,5]. The most recent American guidelines [4] now only recommend using RhEpo in patients with haematological malignancies who are being treated with palliative intent.
Red cell transfusions and immune blood disorders
In immune haemolytic anaemia, antibodies bind to red blood cell surface antigens and initiate destruction via the complement system and/or the macrophage system. Immune haemolytic anaemia may be alloimmune, autoimmune or drug induced (Table 28.1).
Table 28.1 Causes of immune haemolytic anaemia.
|
Alloimmune |
|
Haemolytic disease of the newborn (Chapter 32) |
|
Haemolytic transfusion reactions |
|
After allogeneic stem cell, renal, liver or cardiac transplantation when donor lymphocytes transferred in the allograft (‘passenger lymphocytes’) may produce red cell antibodies against the recipient and cause haemolytic anaemia (Chapter 7) |
|
Autoimmune |
|
Warm-autoantibody (antibody maximally active at 37°C; usually IgG with anti-Rh specificity) Idiopathic (> 30% of cases) Secondary to lymphoproliferative disease (e.g. chronic |
|
Cold-autoantibody (antibody maximally active at less than 37°C; usually IgM) Idiopathic Chronic cold haemagglutinin disease (monoclonal usually with anti-I specificity) Secondary to infections (polyclonal) |
|
Paroxysmal cold haemoglobinuria (usually polyclonal IgG with anti-P specificity) |
|
Drug-induced |
AIHAs are uncommon (incidence 1 to 3 per 100 000 per year). They are characterized by the production of antibodies directed against high frequency red cell antigens and often exhibit reactivity against donor red cells. The degree of haemolysis depends on a number of factors, including the characteristics of the bound antibody (e.g. class, quantity, specificity, thermal amplitude), the target antigen (e.g. density, expression) and other host-related genetic factors (e.g. markers of macrophage activity). The antibody class in turn will affect the degree of classical complement activation (IgM) or binding to splenic and other tissue macrophages via Fc receptors (IgG1 and IgG3 antibodies). The direct antiglobulin test (DAT) is usually positive but can be negative. The threshold of cell bound antibody detection, using the antiglobulin test, is 200 to 500 antibody molecules per cell, but fewer than 100 molecules of IgG per cell may significantly reduce RBC survival in vivo. In warm antibody AIHA, IgG antibodies predominate and the DAT is positive with IgG alone (20%), IgG and complement (detected as C3d) (67%) or C3d only (13%). In cold antibody AIHA, the antibodies (usually IgM) easily elute off red cells, leaving complement on the red cell surface (DAT is positive with C3d alone).
Warm antibody AIHA (Table 28.1)
Therapy of warm antibody AIHA depends on the severity of the haemolysis. Treatment is usually required once symptomatic anaemia develops. Steroids are the first-line treatment (e.g. prednisolone in doses of 1 mg/kg daily) and are effective in inducing a remission in about 80% of patients. Steroids reduce both production of the red cell autoantibody and destruction of antibody-coated cells. Splenectomy may be necessary if there is no response to steroids or if remission is not maintained when the dose of prednisolone is reduced. Other immunosuppressive drugs, such as azathioprine and cyclophosphamide, may be effective in patients who fail to respond to steroids and splenectomy. Ciclosporin and rituximab may also be effective in patients who are refractory to all treatment.
Blood transfusion may be required if there is fulminant haemolytic anaemia or severe anaemia not responding to steroids or other therapy. The presence of red cell autoantibodies on the patient's red cells and in the plasma can cause problems in the identification of compatible blood. It is important to exclude the presence of red cell alloantibodies and autoabsorption of autoantibodies in the plasma using enzyme treatment of the patient's red cells may be necessary to permit the investigation of the plasma for alloantibodies (Chapter 23).
Cold antibody AIHA (Table 28.1)
In cold autoantibody AIHA the IgM antibodies attach to red cells and cause their agglutination in the cold peripheries/extremities of the body; activation of complement can cause intravascular haemolysis when the cells return to the higher temperatures in the core of the body. This can occur after certain infections (Table 28.1), producing a mild-to-moderate transient haemolysis, or can be associated with chronic disease.
Chronic cold haemagglutinin disease usually occurs in the elderly, with a gradual onset of haemolytic anaemia. After exposure to cold the patient develops an acrocyanosis similar to Raynaud's disease as a result of red cell autoagglutination. If possible, the underlying cause of the antibody production should be treated (associated with clonal B-cell lymphocyte proliferation) and patients should avoid exposure to cold. Treatment with steroids, alkylating agents and splenectomy is usually ineffective. Rituximab is increasingly used as a well-tolerated and effective treatment, producing remission in about 50% of patients. Regular blood transfusion is occasionally required to prevent symptoms of anaemia. The laboratory can usually find compatible blood by using prewarmed techniques when performing compatibility testing.
Paroxysmal cold haemoglobinuria (Table 28.1)
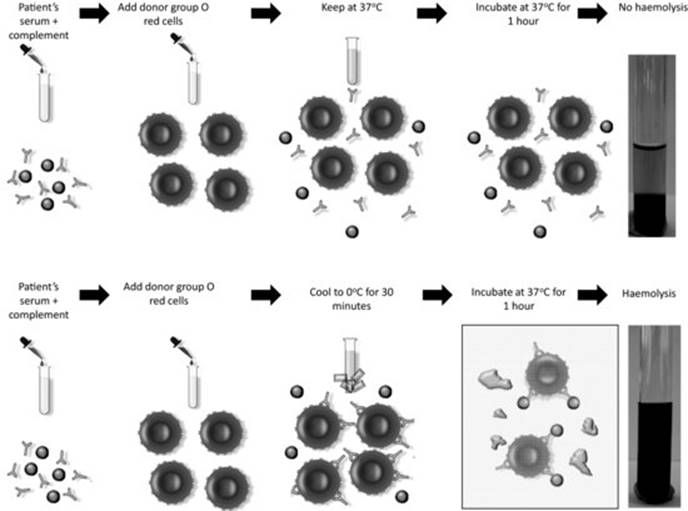
Paroxysmal cold haemoglobinuria is a rare condition that is typically seen in children following a viral illness. It is associated with complement-fixing IgG antibodies that are biphasic (typically anti-P specificity), adhering to the red cell membrane in the cold peripheries, with lysis occurring due to complement activation when the cells return to the central circulation. The lytic reaction is demonstrated in vitro by incubating the patient's red cells and serum at 0°C and then warming the mixture to 37°C (direct Donath–Landsteiner test). This test can be falsely negative due to a lack of complement; hence, a more accurate test is the indirect Donath–Landsteiner test (Figure 28.1). Haemolysis is self-limiting, but supportive transfusions may be necessary. P-negative blood should be considered if there is no sustained response to transfusion of P-positive crossmatch compatible blood.
Fig 28.1 The indirect Donath–Landsteiner test for paroxysmal cold haemoglobinuria.
The issue of whether it is necessary to use an in-line blood warmer when transfusing patients with cold antibody AIHA is controversial. It is logical to keep the patient warm and a common practice to use a blood warmer if the patient has florid haemolytic anaemia.
Drug-induced AIHA (Table 28.1)
There are three basic mechanisms of drug-induced immune RBC injury. In the hapten mechanism, the drug binds strongly to RBC proteins. IgG antibodies are directed against drug epitopes and only react with drug-coated RBCs. Antibody production usually occurs 7 to 10 days after starting the drug and the patient typically is receiving high doses of the drug. Many patients will have a positive DAT but do not have haemolysis. When haemolysis occurs it usually results in a gradual drop in haemoglobin. In the autoantibody mechanism the drug induces formation of IgG autoantibodies via unknown mechanisms. α-Methyldopa can cause a positive DAT 6 to 12 weeks after starting the drug; however, most patients do not have clinical and laboratory signs of haemolysis. In the immune-complex mechanism the drug forms immune complexes with antibody (usually IgM), which then attach to RBC membrane, causing complement mediated lysis. Classically it occurs on second or subsequent exposure to the drug and the patient may present with severe intravascular haemolysis occurring within minutes to hours of drug ingestion.
Platelet transfusions
In general, platelet transfusions are indicated for the prevention and treatment of haemorrhage in patients with thrombocytopenia or platelet function defects. The cause of the thrombocytopenia should be established before platelet transfusions are used because they are not always appropriate treatment for thrombocytopenic patients, and in some instances are contraindicated, e.g. in thrombotic thrombocytopenic purpura, haemolytic–uraemic syndrome and heparin-induced thrombocytopenia (Chapter 30).
Bone marrow failure
Therapeutic platelet transfusions are established as an effective treatment for patients who are bleeding. However, prophylactic platelet transfusion therapy for the prevention of haemorrhage in chronically thrombocytopenic patients with bone marrow failure remains more controversial. Guidelines for platelet transfusion in many countries recommend that the platelet transfusion trigger for prophylaxis is 10 × 109/L [6], and most local departmental policies would follow this recommendation, with an acceptance that selected patients with additional risk factors, such as sepsis or invasive infections, might benefit from higher thresholds.
Unfortunately, many audits continue to document that compliance with these general recommendations is poor, and a recent national comparative audit in the UK [7] showed that a large proportion (28%) of platelet transfusions were given inappropriately. One critical question is whether the evidence from published trials, when combined, demonstrates equivalence in terms of the safety of a platelet count threshold of 10 × 109/L rather than 20 × 109/L. A recent systematic review [8] has suggested that there is insufficient evidence to answer this question. However, many of the bleeding events in these studies were relatively minor and platelet transfusions are associated with well-described risks. Hence, there is no evidence to change from the current practice of a platelet transfusion threshold of 10 × 109/L unless there are other risk factors for haemorrhage.
Much of the recent research interest has focused on the optimal dose of platelets. A large randomized controlled trial [9] showed there was no significant difference in the number of patients who bled between the low dose (1.1 × 10¹¹platelets/m2), medium dose (2.2 × 10¹¹ platelets/m2) and high dose (4.4 × 10¹¹/m2) treatment arms. Overall, a low dose transfusion policy reduced patients' total platelet requirements, but at the expense of a higher number of platelet transfusions. In the UK the standard adult dose is approximately 2.4 × 10¹¹ platelets, which is close to the low dose used in the recently published large platelet dose trial [9].
A question remains as to whether a prophylactic platelet transfusion strategy is appropriate and safe in all subgroups of patients with haematological malignancies, but this awaits the publication of randomized controlled trials in progress [10,11]. A strategy of transfusing platelets only for therapeutic indications in the context of clinical bleeding may be appropriate for some patients with chronic persisting thrombocytopenia due to bone marrow failure syndromes, e.g. myelodyplasia.
Prophylactic platelet transfusions for invasive procedures depends on the type of procedure.
· No increase in platelet count required: bone marrow aspiration and biopsy.
· Platelet count should be raised to 50 × 109/L: lumbar puncture, insertion of intravascular lines, transbronchial and liver biopsy, and laparotomy.
· Platelet count should be raised to more than 100 × 109/L: surgery in critical sites such as the brain or the eyes.
Immune thrombocytopenias
· Autoimmune thrombocytopenias: platelet transfusions should be used only in patients with major haemorrhage [3,12].
· Posttransfusion purpura: platelet transfusions are usually ineffective in raising the platelet count, but may be needed in large doses to control severe bleeding in the acute phase (Chapter 12).
· Neonatal alloimmune thrombocytopenia: human platelet antigen (HPA)-matched platelet concentrates are the most appropriate treatment for this condition (Chapter 32).
Massive blood transfusion
· Clinically significant dilutional thrombocytopenia only occurs with the transfusion of more than 1.5 times the blood volume of the recipient.
· The platelet count should be maintained above 50 × 109/L in patients receiving transfusions for massive acute blood loss (Chapter 26).
Disseminated intravascular coagulation
· In acute disseminated intravascular coagulation (DIC), where there is bleeding associated with severe thrombocytopenia, platelet transfusions should be given in addition to coagulation factor replacement (Chapter 25).
· In chronic DIC, or in the absence of bleeding, platelet transfusions are not indicated.
Cardiopulmonary bypass surgery
· Platelet function defects and some degree of thrombocytopenia frequently occur after cardiac bypass surgery, but prophylactic platelet transfusions are not indicated (Chapter 27).
· Platelet transfusions should be reserved for patients with bleeding not due to surgically correctable causes.
Granulocyte transfusions
Severe persisting neutropenia is the principal limiting factor in the use of intensive treatment of patients with haematological malignancies. It may last for 2 weeks or more after chemotherapy or stem-cell transplantation, and during this period the patient is at risk of life-threatening bacterial and fungal infections. The use of haemopoietic growth factors, such as granulocyte colony-stimulating factor (G-CSF), may reduce the duration and severity of severe neutropenia, but they are only effective if the patient has sufficient numbers of haemopoietic precursors. Moreover, the time to response may be several days. Supportive treatment with granulocyte transfusions is a logical approach, although a number of factors have limited its application:
· difficulties in the collection of neutrophils, which are present in low numbers in normal individuals and which are difficult to separate from red cells because of their similar densities (commercially available long-chain starch solutions now facilitate this separation);
· the short half-life of neutrophils after transfusion, coupled with short storage times and negative effects on function of prolonged storage;
· The frequent occurrence of adverse effects such as febrile reactions, including occasional severe pulmonary reactions and human leucocyte antigen (HLA) alloimmunization causing platelet refractoriness.
Various methods have been used in the past to increase the number of neutrophils collected, including obtaining granulocytes from patients with chronic myeloid leukaemia, treating donors with steroids and using hydroxyethyl starch to promote sedimentation of red cells. However, a number of clinical trials of granulocyte transfusions in the 1970s and 1980s suggested they had limited efficacy in adults, and interest in their usage declined. Some centres continued to use granulocyte transfusions for small children and neonates because concentrates collected from adult donors produced a relatively much greater dose per recipient weight, and sometimes appeared to be clinically effective.
There has recently been a resurgence of interest in granulocyte transfusions because of the accumulating evidence that G-CSFs can be safely administered to normal individuals [13]. Much larger doses of granulocytes can be collected from donors using regimens including G-CSF administered 12–16 hours prior to apheresis, together with oral steroids such as dexamethasone to further improve the yields. Further evidence of the safety of this approach for donors and the efficacy of granulocyte transfusions collected in this way are required before granulocyte transfusion therapy becomes accepted in the care of patients with severe neutropenia and fungal infection, in conjunction with other potential approaches such as improved diagnostic strategies and organism-targeted antimicrobials. Evidence of survival benefit following granulocyte transfusions are clearly needed and a trial to evaluate this is currently ongoing (resolving infections in neutropenia with granulocytes, or RING). High dose granulocyte transfusions collected using donors treated with G-CSFs might therefore be considered as indicated in patients of any age with severe neutropenia due to bone marrow failure under the following circumstances:
· proven bacterial or fungal infection unresponsive to antimicrobial therapy or probable bacterial or fungal infection unresponsive to appropriate blind antimicrobial therapy;
· neutrophil recovery not expected for 5–7 days;
· children and lighter adults might be expected to show better incremental responses to granulocyte transfusions.
Granulocyte transfusions might be considered inappropriate for:
· patients with haematological disease resistant to treatment;
· ventilated patients; and
· patients with known HLA alloimmunization.
Approach to complications associated with blood transfusion in haematology patients
Transfusion-transmitted CMV infection
Clinical features and risk factors
CMV infection may cause significant morbidity and mortality in immunocompromised patients, mainly due to pneumonia. Patients who have never been exposed to CMV are at risk for primary infection transmitted by blood components prepared from blood donors who have previously had CMV infection and still carry the virus.
Patients who have been previously exposed to CMV and are CMV seropositive are at risk of reactivation of CMV during a period of immunosuppression. The extent to which CMV-seropositive patients are at risk from reinfection with different strains of CMV remains unknown, but this risk is generally considered to be low. The patients at risk of transfusion-transmitted CMV infection are shown in Table 28.2 [14], and the generally accepted indications for the use of CMV-seronegative or ‘CMV-safe’ blood components are shown in Table 28.3.
Table 28.2 Patients at risk for transfusion-transmitted cytomegalovirus (CMV) infection. Reproduced from Clark & Miller [6].
|
Risk well established |
|
CMV-seronegative recipients of allogeneic bone marrow/ peripheral blood progenitor cell transplants from CMV-seronegative donors |
|
CMV-seronegative pregnant women |
|
Premature infants (<1.2 kg) born to CMV-seronegative women |
|
CMV-seronegative patients with HIV infection |
|
Risk less well established |
|
CMV-seronegative patients receiving autologous bone marrow/peripheral blood progenitor cell transplants |
|
CMV-seronegative patients who are potential recipients of allogeneic or autologous bone marrow/peripheral blood progenitor cell transplants |
|
CMV-seronegative patients receiving solid organ (kidney, heart, lung, liver) transplants from CMV-seronegative donors |
|
Risk not established |
|
CMV-seronegative recipients of allogeneic bone marrow/ peripheral blood progenitor cell transplants from CMV-seropositive donors |
|
CMV-seropositive recipients of bone marrow/peripheral blood progenitor cell transplants |
|
CMV-seropositive recipients of solid organ transplants |
Table 28.3 Indications for the use of cytomegalovirus (CMV)-seronegative or CMV-safe blood components.
|
Transfusions in pregnancy |
|
Intrauterine transfusions |
|
Transfusions to neonates and to infants in the first year of life |
|
Transfusions to the following groups of CMV-seronegative patients: |
|
After allogeneic bone marrow/peripheral blood |
|
After autologous bone marrow/peripheral blood |
|
Potential recipients of allogeneic bone marrow/peripheral blood progenitor cell transplants |
|
Patients with HIV infection |
Prevention
The use of CMV-seronegative blood components has been shown to reduce the incidence of CMV infection in groups at risk for transfusion-transmitted CMV infection to 1–3%. This incomplete prevention may be due to:
· occasional failure to detect low level CMV antibodies;
· loss of antibodies in previously infected blood donors; and
· transfusion of blood components prepared from recently infected donors.
CMV is transmitted by leucocytes, and a number of studies have found that pre-storage leucocyte reduction of blood components is as effective as the use of CMV-seronegative blood components in the prevention of transfusion-transmitted CMV infection in neonates, patients undergoing remission induction therapy for acute leukaemia and after bone marrow transplantation (the only prospective randomized trial was conducted in transplant recipients using bedside leucocyte-reduction filters, which cannot be adequately quality controlled for leucocyte reduction). These data suggest that pre-storage leucocyte-reduced blood components can be accepted as a substitute for CMV-seronegative blood components for patients at risk of transfusion-transmitted CMV infection when CMV-seronegative blood components are not available, i.e. that leucocyte-reduced blood components are ‘CMV-safe’. A consensus conference in Canada recommended that where universal leucocyte reduction had been implemented, both leucocyte-reduced and CMV-seronegative blood should be used for CMV-seronegative pregnant women, intrauterine transfusions and CMV-seronegative allogeneic haemopoietic cell transplant recipients [15]. Further information about the effectiveness of leucocyte reduction of blood components in the prevention of transfusion-transmitted infections is unlikely to become available, and some haematology centres have decided to abandon the use of CMV-seronegative blood components where pre-storage leucocyte-reduced blood components are used routinely [16].
Transfusion-associated graft-versus-host disease
Pathogenesis and clinical features
Transfusion-associated graft-versus-host disease (TA-GVHD) is a rare but serious complication of blood transfusion. As discussed in Chapter 11, there is engraftment and proliferation of donor T-lymphocytes and interaction with recipient cells expressing HLA antigens causing cellular damage particularly to the skin, gastrointestinal tract, liver and spleen, and the bone marrow. Clinical manifestations usually occur 1–2 weeks after blood transfusion, and early features include fever, maculopapular skin rash, diarrhoea and hepatitis. Haematology patients at risk are those who are undergoing transplantation, have Hodgkin's lymphoma or have received therapy with certain drugs, e.g. purine analogues.
Prevention
The dose of donor lymphocytes sufficient to cause TA-GVHD is unknown, but may be lower than is achievable by current techniques for leucocyte reduction of blood components. However, there have been no case reports of TA-GVHD in the UK since 2001 following the implementation of universal leucocyte reduction of blood in the UK in 1999. Gamma-irradiation to destroy the proliferative capability of donor lymphocytes remains the usual method of choice to prevent TA-GVHD (see Chapter 11), although it is a radioactive source and requires regular recalibration. An alternative to gamma-irradiation is X-ray irradiation, which is used in several European countries. Key considerations in the assessment of methods for the prevention of TA-GVHD are their effectiveness and the avoidance of excessive damage to red cells and platelets. The currently recommended indications for the use of irradiated blood for haematology patients are shown in Table 28.4 [17]. Although gamma-irradiation is currently the accepted method of preventing TA-GVHD, pathogen-reduction technologies have been shown to be as effective at inactivating lymphocytes. Pathogen-reduced platelet components are accepted as safe from the risk of TA-GVHD in some countries without the need for further processing such as gamma-irradiation.
Table 28.4 Indications for irradiation of blood components in haematology patients. Reproduced from British Committee for Standards in Haematology [17].
|
Indications |
|
Except for stem cell infusions, all donations from first- or second-degree relatives, even if the patient is immunocompetent |
|
Except for stem cell infusions all HLA-matched components, even if the patient is immunocompetent |
|
All granulocyte components |
|
Allogeneic bone marrow/peripheral blood progenitor cell transplantation: from the time of initiation of conditioning therapy and continuing while the patient remains on GVHD prophylaxis (usually 6 months) or until lymphocytes are >1 × 10⁹/L. If chronic GVHD is present or if continued immunosuppressive treatment is required, irradiated blood components should be given indefinitely |
|
Allogeneic blood transfused to bone marrow and peripheral blood stem cell donors 7 days prior to or during the harvest must be irradiated |
|
Autologous bone marrow/peripheral blood progenitor cell transplantation: during and 7 days before the harvest of haemopoietic cells, and then from the initiation of conditioning therapy until 3 months posttransplant (6 months if total body irradiation is used) |
|
All adults and children with Hodgkin's lymphoma should have irradiated red cells and platelets for life |
|
Severe T-lymphocyte immunodeficiency syndromes |
|
Patients treated with purine analogues such as fludarabine, cladribine and deoxycoformycin and newer drugs such as bendamustine and clofarabine |
|
Patients receiving alemtuzumab (anti-CD52) |
|
Patients with aplastic anaemia receiving treatment with antithymocyte globulin (ATG) |
|
Nonindications |
|
Patients receiving rituximab (anti-CD20). |
|
Non-Hodgkin's lymphoma (although this may be reviewed following some recent reports of TA-GVHD in patients with B-cell non-Hodgkin's lymphoma) |
|
HIV infection |
|
TA-GVHD, transfusion-associated graft-versus-host disease. |
How to ensure that patients receive the correct ‘special’ blood?
An important issue for haematology departments and hospital blood banks is how to ensure that patients receive special blood components (e.g. CMV-seronegative, gamma-irradiated) when these products are indicated and that standard blood components are not transfused, as this may have devastating consequences.
Each hospital needs to establish its own procedures so that patients receive the correct special blood components, where they are indicated. These should include the following:
· Education of ward medical and nursing staff about the indications for special blood components and the importance of receiving the correct type of blood component.
· Requests for blood components to include the patient's diagnosis and any requirement for special blood components.
· Storing of individual patient's requirements for special blood components in the blood bank computer.
· The prescription for blood components should include any requirement for special blood components, enabling the ward staff to check that the blood component to be transfused complies with these requirements.
· Providing patients with cards indicating their special blood requirements, particularly for those patients receiving shared care between two hospitals and those with a long-term requirement for gamma-irradiated blood, e.g. patients with Hodgkin's lymphoma.
HLA alloimmunization and refractoriness to platelet transfusions [6]
Platelet refractoriness is the repeated failure to obtain satisfactory responses to platelet transfusions and occurs in more than 50% of patients receiving multiple transfusions.
Various methods are used to assess response to platelet transfusions. If the patient is bleeding, the clinical response is an important indication of the effectiveness of the transfusion. The response to a prophylactic platelet transfusion is assessed by measuring the increase in platelet count after the transfusion. Various formulas have been used to correct for the variation in response dependent on the patient's size and the number of platelets transfused; these include platelet recovery and corrected count increment. However, in practice, a (nonsustained) increase in the patient's platelet count of less than 5 × 10⁹/L at 20–24 hours after the transfusion can be used as a simple measure of a poor response.
Causes
Many causes of platelet refractoriness have been described and can be subdivided into immune mechanisms, most importantly HLA alloimmunization and nonimmune mechanisms involving platelet consumption (Table 28.5). Platelet consumption is the most frequent mechanism of platelet refractoriness, usually associated with sepsis. However, immune-mediated platelet destruction remains an important cause of platelet refractoriness; HLA antibodies are the commonest immune cause and the other immune causes are rare.
Table 28.5 Causes of platelet refractoriness.
|
Immune |
|
Platelet alloantibodies |
|
HLA |
|
HPA |
|
ABO |
|
Other antibodies |
|
Platelet autoantibodies |
|
Drug-dependent platelet antibodies |
|
Immune complexes |
|
Nonimmune |
|
Infection and its treatment, especially amphotericin B |
|
Splenomegaly |
|
Disseminated intravascular coagulation |
|
Fever |
|
Bleeding |
The precise mechanism of HLA alloimmunization remains uncertain, but primary HLA alloimmunization appears to be initiated by intact cells expressing both HLA class I and class II antigens such as lymphocytes and antigen-presenting cells. Platelets only express HLA class I antigens and hence leucocyte-reduced blood components cause primary HLA alloimmunization in fewer than 3% of recipients. Use of pre-storage leucocyte-reduced blood components has therefore led to a significant reduction in the incidence of HLA alloimmunization. However, secondary HLA alloimmunization does not require the presence of HLA class II antigens, and may occur in patients who have been pregnant or previously transfused with non-leucocyte-reduced blood components.
Investigation and management
If platelet refractoriness occurs, the following algorithm can be used for investigation and management (Figure 28.2 [18]).
1. A clinical assessment should be made for clinical factors likely to be associated with nonimmune platelet consumption.
2. If nonimmune platelet consumption appears likely, an attempt should be made to correct the clinical factors responsible, where possible, and platelet transfusions from random donors should be continued. If a poor response to random donor platelet transfusions persists, the patient should be tested for HLA antibodies.
3. If nonimmune platelet consumption appears to be unlikely, an immune mechanism should be suspected and the patient's serum should be tested for HLA antibodies. If HLA antibodies are present, the specificity of the antibodies should be determined as this may help in the selection of HLA-compatible donors. However, HLA antibodies stimulated by repeated transfusions are often ‘multispecific’ and it is not possible to determine their specificity.
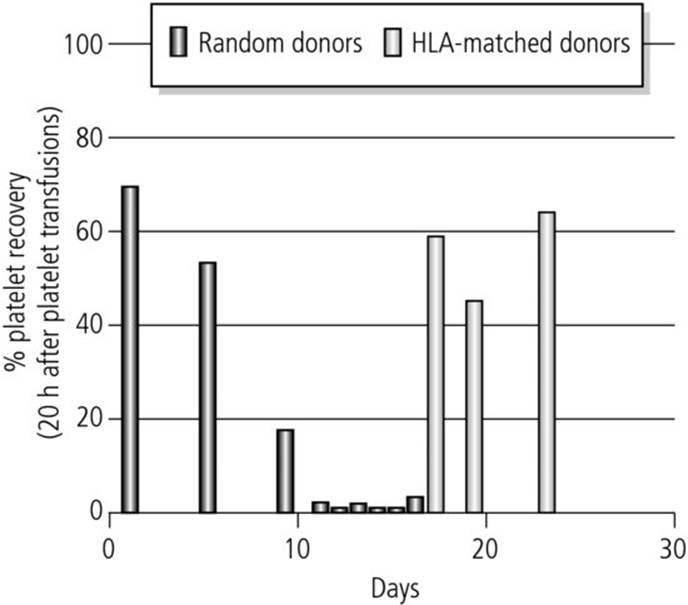
4. Platelet transfusions from HLA-matched donors (matched for the HLA-A, -B antigens of the patient) should be used for patients with apparent immune refractoriness and the response to further transfusions should be observed carefully. Figure 28.3 shows improved responses to HLA-matched platelet transfusions in a patient with platelet refractoriness due to HLA alloimmunization. If responses to HLA-matched transfusions are not improved, the reason should be sought, and platelet cross-matching of the patient's serum against the lymphocytes and platelets of HLA-matched donors may be helpful in determining the cause and the selection of compatible donors for future transfusions. These matching strategies are based on counting the number of HLA-A and HLA-B mismatches between the patient and donor; this requires a large HLA typed donor panel and at times no suitable matches can be found. An alternative approach is HLA epitope matching; this only considers the epitopes on the HLA antigen, whereas standard HLA-matching considers the whole HLA antigen.
5. If there are no factors for nonimmune platelet consumption and HLA antibodies are not detected, consideration should be given to less frequent causes of immune platelet refractoriness.
a. High titre ABO antibodies in the recipient. This is an unusual cause of platelet refractoriness and can be excluded by switching to ABO-compatible platelet transfusions if ABO-incompatible transfusions have been used for previous transfusions.
b. HPA antibodies, which usually occur in combination with HLA antibodies, but sometimes occur in isolation.
c. Drug-dependent platelet antibodies, which may be underestimated as a cause for platelet refractoriness.
Fig 28.2 Algorithm for the investigation and management of patients with platelet refractoriness. DIC, disseminated intravascular coagulation.

Fig 28.3 Responses to platelet transfusions in a female patient with acute myeloblastic leukaemia undergoing remission induction therapy. There were poor responses to the initial platelet transfusions and the patient was found to have HLA antibodies. There were improved responses to platelet transfusions from HLA-matched donors.
Alloimmunization to red cell antigens
Incidence
Alloimmunization to red cell antigens is another important consequence of repeated transfusions in haematology patients. The incidence of red cell alloimmunization in adult haematology patients is in the range of 10–15% and is similar to other groups of multitransfused patients, e.g. patients with renal failure. However, a higher proportion of children requiring long-term transfusion support develop red cell alloimmunization. In sickle cell disease, the incidence is in the range of 20–30% (see Chapter 29). The implications of these observations include the following.
· Patients with sickle cell disease should be phenotyped for Rh, Kell, Fy, Jk and MNS antigens before the first transfusion and patients with thalassaemia and other children requiring chronic transfusion support should be phenotyped for Rh and Kell antigens.
· Blood for transfusion to children requiring long-term transfusion support, including patients with haemoglobinopathies, should be matched for Rh and Kell antigens to prevent alloimmunization.
· Phenotyping and antigen matching to prevent red cell alloimmunization is not required for other groups of patients requiring repeated transfusions.
Timing of sample collection for compatibility testing [19]
In patients with haematological disorders receiving repeated transfusions, an important issue is the timing of blood sample collection in relation to the previous transfusion.
· Where the patient is receiving very frequent transfusion, e.g. daily, it is only necessary to request a new sample every 3 days.
· In the UK, if the previous transfusion was 3–14 days earlier, the sample should ideally be taken within 24 hours of the start of the transfusion, although some laboratories stretch this to 48 hours for patients who have been repeatedly transfused without developing antibodies. Other countries, e.g. Canada, only require a sample within 3 days of the start of the transfusion.
· Where the previous transfusion was 14–28 days earlier, the sample should be taken within 3 days of the start of the transfusion.
· Where the previous transfusion was more than 28 days ago, the sample should be taken within 1 week of the planned transfusion.
Sample collection timeframe requirements do vary slightly from country to country.
ABO-incompatible bone marrow/peripheral blood progenitor cell transplants
ABO-incompatible bone marrow/peripheral blood progenitor cell transplants present particular problems (Table 28.6). The transplant may provide a new A and/or B antigen from the donor (major mismatch) or a new A and/or B antibody (minor mismatch). For pretransplant, blood component support should be with the patient's own ABO type. For posttransplant, selection of the appropriate group is more complicated (see Figure 28.4 [20]). The requirements for platelet and FFP support are also shown. These recommendations should be followed posttransplant until the patient has engrafted, ABO antibodies to the donor ABO group are undetectable and the direct antiglobulin test is negative.
Table 28.6 Problems associated with ABO-incompatible bone marrow/peripheral blood progenitor transplants.
|
Major ABO incompatibility (e.g. recipient O, donor A) |
|
Failure of engraftment: risk not increased in ABO-incompatible transplants |
|
Acute haemolysis at the time of reinfusion: avoided by processing donor bone marrow/peripheral blood progenitor cells |
|
Haemolysis of donor-type red cells: avoid by using red cells of recipient type in the early posttransplant period |
|
Delayed erythropoiesis: may be due to persistence of anti-A in the recipient, minimize transfusion of anti-A by using platelets and plasma from group A donors |
|
Delayed haemolysis due to persistence of recipient anti-A: only switch to donor red cells when recipient anti-A undetectable and direct antiglobulin test undetectable |
|
Minor ABO incompatibility (e.g. recipient A, donor O) |
|
Acute haemolysis at the time of reinfusion: avoid by removing donor plasma if the donor anti-A titre is high |
|
Delayed haemolysis of recipient cells due to anti-A produced by donor lymphocytes (passenger lymphocyte syndrome): maximum haemolysis usually occurs between days 9 and 16 posttransplant. Rare in T-cell-depleted grafts or when CD34+ cells selected in stem cell processing |
· Major ABO incompatibility: the patient's own ABO group should be given. Plasma and platelets should be of the donor-type blood group. The European Group for Blood and Marrow Transplantation (EBMT) also advise that group O red cells can be used.
· Minor ABO incompatibility: red cells of the donor ABO group should be given. Plasma and platelets should be of a recipient-type blood group.
· Major and minor (bidirectional) ABO incompatibility: give group O red cells, group AB plasma and platelets of the recipient-type blood group.
Fig 28.4 Recommendations for ABO type of blood components in ABO-incompatible bone marrow/peripheral blood progenitor cell transplants. Adapted from Warkentin [20], with permission.

Studies disagree on whether ABO incompatibility can also affect overall survival, disease-free survival or GVHD. A recent meta-analysis [21] found no difference in overall survival between recipients of ABO matched or mismatched grafts when the donor was related. However, in unrelated donor transplants there was a marginally reduced overall survival in patients who received bidirectional or minor-mismatched transplants.
· RhD-incompatible transplants can also cause difficulties. It is recommended that RhD-negative blood components should be used for RhD-positive recipients with RhD-negative donors. However, no cases of immunization have been reported when RhD-negative recipients have received RhD-positive transplants, and RhD-positive blood components may be used.
Iron overload
A major adverse consequence of repeated red cell transfusions over a long period in patients with haemoglobinopathies or myelodysplastic syndromes is iron overload. This important complication is described in detail in Chapter 29.
Key points
1. Specialist transfusion support and advice is required for many patients with haematological disorders.
2. The need for transfusion, as in other groups of patients, is determined by assessment of individual patient's symptoms and blood counts and guided by national and local recommendations for the use of blood.
3. Special blood components are frequently needed to avoid complications such as TA-GVHD and transfusion transmission of CMV in haematology patients susceptible to these complications.
4. Responses to platelet transfusions should be carefully monitored to identify patients having poor responses, which require clinical and laboratory investigation to determine the most likely cause and the best approach to management.
5. Further work is needed to define the optimal thresholds for red cell and platelet transfusion in patients with haematological malignancies and the role of granulocyte transfusions.
References
1. Wallis JP, Wells AW & Chapman CE, on behalf of the Northern Regional Transfusion Committee. Changing indications for red cell transfusion from 2000 to 2004 in the North of England. Transfus Med 2006; 16: 411–417.
2. British Committee for Standards in Haematology. Guidelines on the clinical use of red cell transfusions. Br J Haematol 2001; 113: 24–31.
3. Valeri CR, Khuri S & Ragno G. Nonsurgical bleeding diathesis in anemic thrombocytopenic patients: role of temperature, red blood cells, platelets, and plasma-clotting proteins. Transfusion 2007; 47: 206S–248S.
4. Rizzo JD, Brouwers M, Hurley P et al. American Society of Hematology/American Society of Clinical Oncology clinical practice guideline update on the use of epoetin and darbopoetin in adult patients with cancer. Blood 2010; 116(20): 4045–4059.
5. Wilson J, Yao GL, Raftery J et al. A systematic review and economic evaluation of epoetin alfa, epoetin beta and darbepoetin alfa in anaemia associated with cancer, especially that attributable to cancer treatment. Health Technol Assess 2007; 11(13): 1–220.
6. British Committee for Standards in Haematology. Guidelines for platelet transfusions. Br J Haematol 2003; 122: 10–23.
7. Estcourt LJ, Birchall J, Lowe D et al. Platelet transfusions in haematology patients: are we using them appropriately? Vox Sang 2012; 103(4): 284--293.
8. Estcourt LJ, Stanworth SJ, Doree C et al. Prophylactic platelet transfusion for the prevention of haemorrhage after chemotherapy and stem cell transplantation. Cochrane Database Syst Rev 2012; Issue 5. DOI: 10.1002/14651858.CD004269.pub3.
9. Slichter SJ, Kaufman RM, Assmann SF et al. Dose of prophylactic platelet transfusions and prevention of haemorrhage. N Engl J Med 2010; 362: 600–613.
10. Stanworth SJ, Dyer C, Choo L et al. Do all patients with haematologic malignancies and severe thrombocytopenia need prophylactic platelet transfusions? Background, rationale and design of a clinical trial (trial of platelet prophylaxis) to assess the effectiveness of prophylactic platelet transfusions. Transfus Med Rev 2010; 24: 163–171.
11. Wandt H, Schäfer-Eckart K, Wendelin K et al. A therapeutic platelet transfusion strategy without routine prophylactic transfusion is feasible and safe and reduces platelet transfusion numbers significantly: final analysis of a randomised study after high-dose chemotherapy and PBSCT. Bone Marrow Transplantat 2009; 43(S1s): S23.
12. Neunert C, Lim W, Crowther M et al. The American Society of Hematology 2011 evidence-based practice guideline for immune thrombocytopenia. Blood 2011; 117: 4190–4207.
13. Price TH. Granulocyte transfusion: current status. Semin Hematol 2007; 44: 15–23.
14. Sayers M, Anderson KC, Goodnough LT et al. Reducing the risk for transfusion-transmitted cytomegalovirus infection. Ann Int Med 1992; 116: 55–62.
15. Laupacis A, Brown J, Costello B et al. Prevention of posttransfusion CMV in the era of universal WBC reduction: a consensus statement. Transfusion 2001; 41: 560–569.
16. Clark P & Miller JP. Leucocyte-reduced and cytomegalovirus-reduced-risk blood components. In: PD Mintz (ed.), Transfusion Therapy: Clinical Principles and Practice, 3rd edn. Bethesda, MD: AABB Press; 2010.
17. British Committee for Standards in Haematology. Guidelines on irradiated blood components for the prevention of graft-versus-host disease. Br J Haematol 2010; 152: 35–51.
18. Dzik S. How I do it: platelet support for refractory patients. Transfusion 2007; 47(3): 374–378.
19. British Committee for Standards in Haematology. Guidelines for compatibility procedures in blood transfusion laboratories. Transfus Med 2004; 14: 59–73.
20. Warkentin PI. Transfusion of patients undergoing bone marrow transplantation. Hum Pathol 1983; 14: 261–266.
21. Kanda J, Ichinohe T, Matsuo K et al. Impact of ABO mismatching on the outcomes of allogeneic related and unrelated blood and marrow stem cell transplantations for hematologic malignancies: IPD-based meta-analysis of cohort studies. Transfusion 2009; 49(4): 624–635.
Further reading
Campell-Lee SA. The future of red cell alloimmunisation. Transfusion 2007; 47: 1959–1960.
Cohen AR. New advances in iron chelation therapy. Hematology Am Soc Hematol Educ Program 2006: 42–47.
Drew WL & Roback JD. Prevention of transfusion-transmitted cytomegalovirus: reactivation of the debate? Transfusion 2007; 47: 1955–1958.
Estcourt LJ, Stanworth SJ & Murphy MF. Platelet transfusions for patients with haematological malignancies: who needs them? Br J Haematol 2011; 154(4): 425–440.
Heddle NM. Acute paroxysmal cold hemoglobinuria. Transfus Med Rev 1989, July; 3(3): 219–229.
Silberstein LE & Cunningham MJ. Autoimmune hemolytic anemias. In: CD Hillyer, LE Silberstein, PM Ness, KC Anderson & JD Roback (eds), Blood Banking and Transfusion Medicine: Basic Principles and Practice, 2nd edn. Philadelphia, PA: Churchill Livingstone; 2007.
Stanworth S, Massey E, Hyde C et al. Granulocyte transfusions for treating infections in patients with neutropenia or neutrophil dysfunction. Cochrane Database Syst Rev 2005; Issue 3. DOI: 10.1002/14651858/CD005339.