
Low birth weight is the term used to define infants who are born too small, and preterm or premature birth are the terms used to define infants who are born too soon. Preterm birth is one of the major health hazards of humans, being the greatest cause (other than congenital anomalies) of neonatal morbidity and mortality. The American College of Obstetricians and Gynecologists (Preterm labor. Technical Bulletin No. 206, June 1995) has suggested that preterm birth be defined as delivery prior to the completion of 37 weeks.
With continued improved care of the preterm infant, other definitions have been developed. For example, the great preponderance of mortality and serious morbidity from preterm birth is prior to 34 weeks and some clinicians consider 34 weeks to be the threshold for significant prematurity. Very low birth weight (infants weighing 1500 g or less) and extremely low birth weight (those who weigh 1000 g or less) are also commonly used terms to describe premature infants.
With respect to size, the fetus or infant may be normally grown or appropriate for gestational age (AGA), small in size or small for gestational age (SGA), or overgrown and consequently large for gestational age (LGA). In recent years, the term small for gestational age has been widely used to categorize an infant whose birth weight is below the 10th percentile for its age. Another often-used term for these infants is fetal growth restriction. The infant whose birth weight is above the 90th percentile has been categorized as large for gestational age, and the infant whose weight is between the 10th and 90th percentiles is designated appropriate for gestational age. Thus, an infant born before term can be small or large for gestational age and still be preterm. It is important to recognize that preterm birth also frequently includes infants who have suffered subnormal in-utero growth.
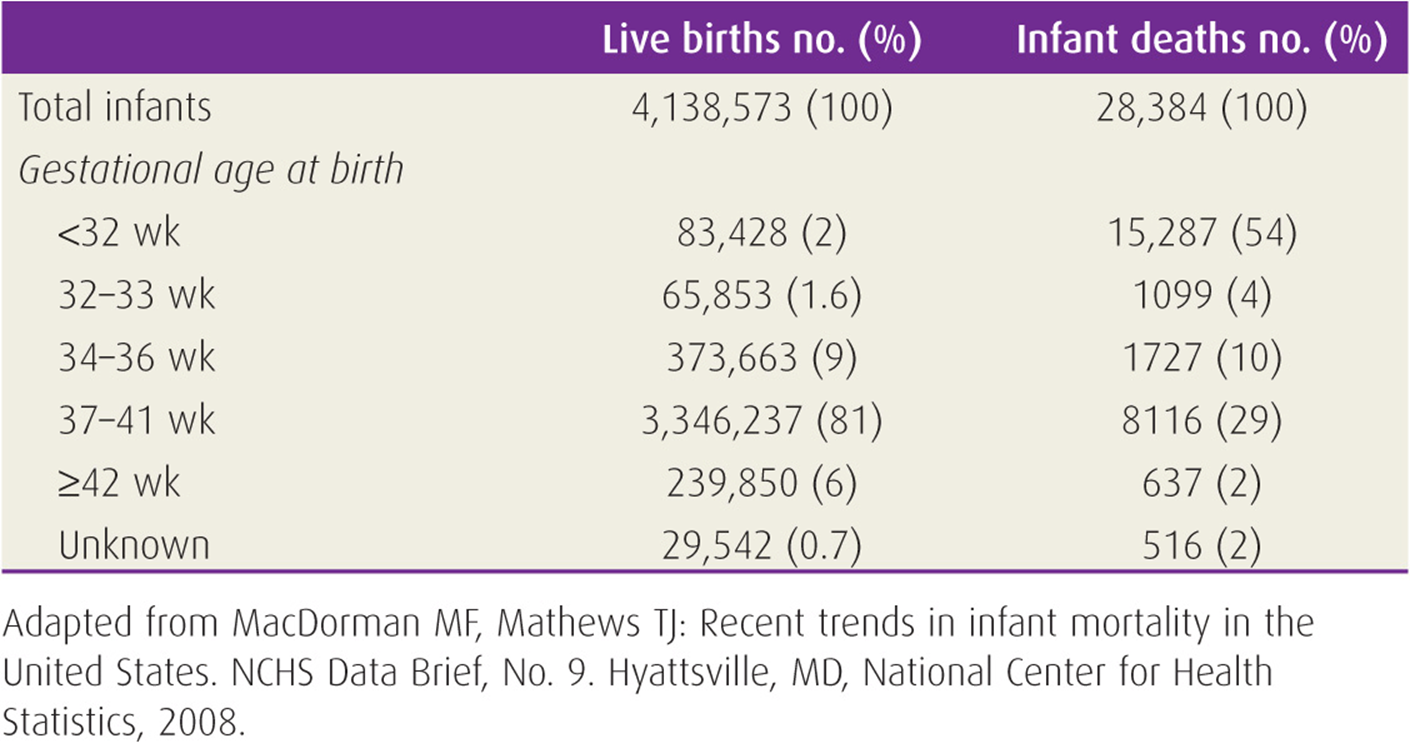
As shown in Table 32-1, almost 90 percent of live births in the United States occur at 37 weeks or later, and progressively fewer births are recorded with decreasing gestational weeks at delivery. In many industrialized countries, including the United States, the proportion of infants born before term has increased in the past 20 years. This increase in preterm births has been attributed to changes in the frequency of multiple births, increases in obstetrical intervention, improved ascertainment of early preterm births, and increased use of ultrasound for estimating gestational age.
TABLE 32-1. Infant Mortality Rates in the United States in 2005
LOWER LIMIT OF SURVIVAL
Gestational age-linked survival and survival without major morbidity at Parkland Memorial Hospital from 2001–2005 is shown in Figure 32-1. Chances for survival increased appreciably at or above 1000-g birth weight. These data also indicate that survival is possible for infants weighing 500 to 750 g. Many of these extremely low-birth-weight infants, however, were growth restricted and, therefore, of more advanced maturity. Clearly, expectations for neonatal survival are influenced by gestational age and maturity rather than simply by birth weight alone.
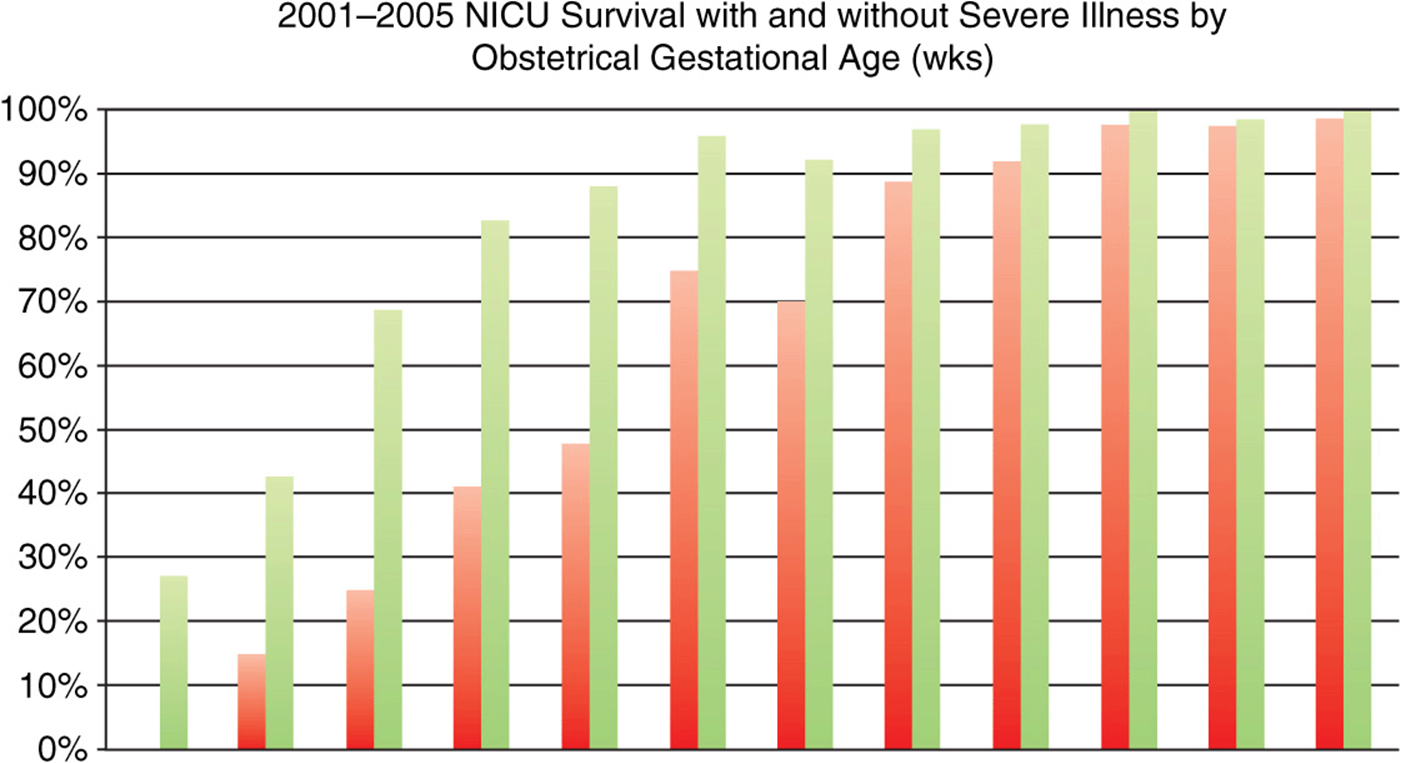
FIGURE 32-1 Infants who were not offered resuscitation and those with congenital anomalies are excluded. Severe illness includes moderate or severe BPD, NEC stage 2 or above, or grade 3 or 4 IVH. (Courtesy of Department of Pediatrics at Parkland Memorial Hospital).
The frontier or lower limit for infant survival has been progressively pushed earlier into gestation primarily as a result of continued innovations in neonatal intensive care. The period of gestation from 23 to 25 weeks currently poses the greatest dilemma for both the obstetrician and pediatrician. The probability of neonatal death before 26 weeks exceeds 75 percent. Severe infant morbidities, as well as death, are common before 26 weeks’ gestation and almost universal before 24 weeks’ gestation.
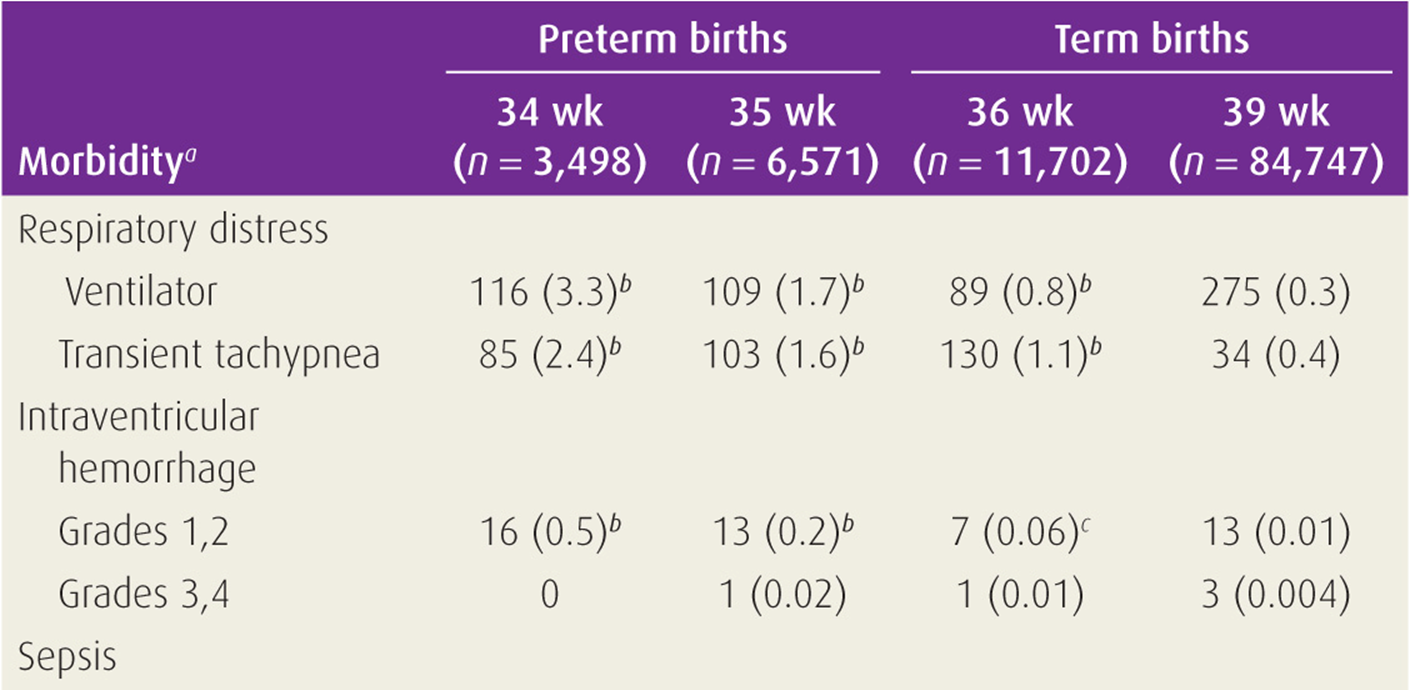
Not only has the frontier for neonatal survival been pushed earlier into pregnancy, but survival of larger preterm infants has become as good as that for term infants (see Figure 32-1). Only recently late preterm infants 34 to 36 weeks have gained attention because of increased morbidity rates compared with those of term infants. These infants amount for 75 percent of all preterm births and are the fastest increasing and largest proportion of singleton births in the United States (see Table 32-2).
TABLE 32-2. Neonatal Morbidity at Parkland Hospital in Live Births Delivered Late Preterm Compared with 39 Weeks

LONG-TERM CONSEQUENCES
For infants born at the frontier of survival, the high rate of significant neonatal morbidity in these tiny infants, and the likelihood of a normal life, must be weighed against the apparent triumph of survival. Survival without neurological disability (i.e., cerebral palsy) has been reported in less than 1 percent of infants born before 22 weeks, 5 percent during the 23rd week, 12 percent during the 24th week, and 23 percent during the 25th week. It has been suggested from a review of outcomes in such infants that full resuscitation and intensive care should definitely be given at 26 weeks, probably be given at 25 weeks, possibly be given at 24 weeks, but not at 23 weeks or earlier.
CATEGORIES AND CAUSES OF PRETERM BIRTH
Women delivered preterm can be categorized into three broad, general groups with varying causes leading to preterm delivery. These groups are shown in Table 32-3.
TABLE 32-3. General Categories of Pregnancies Complicated by Preterm Delivery

Mandated Preterm Delivery
All too often, pregnancy complications force a clinical decision to affect preterm delivery rather than continue pregnancy. A host of pregnancy disorders may mandate such a choice. Most commonly, these complications of pregnancy threaten fetal health so that a continued intrauterine existence will likely result in fetal death. Many examples may be cited, but the most common are maternal hypertension, severe diabetes mellitus, failure of fetal growth, and abruptio placenta.
Preterm Premature Rupture of the Membranes
This term is used to denote spontaneous rupture of the fetal membranes before the onset of labor and before term. The pathogenesis of premature rupture of the membranes is obscure but occult infection has been implicated (see Chapter 34).
Spontaneous Preterm Labor with Intact Membranes
Pregnancies with intact fetal membranes and spontaneous labor before term must be distinguished from those in which there has been preterm premature rupture of the membranes. Common causes of spontaneous preterm labor are shown in Table 32-4.
TABLE 32-4. Common Causes of Preterm Birth at 23 to 36 Weeks in Decreasing Order of Frequency

A large variety of factors have been implicated in preterm deliveries due to either rupture of the membranes or spontaneous labor with intact membranes.
Lifestyle Factors
Behaviors such as cigarette smoking, poor nutrition and poor weight gain during pregnancy, and use of drugs such as cocaine or alcohol have been reported to play important roles in the incidence and outcome of low-birth-weight infants. Some of this effect is undoubtedly due to restricted fetal growth as well as preterm birth.
Other maternal factors implicated include young maternal age, poverty, short stature, and occupational factors. Another lifestyle factor that seems intuitively important, yet has seldom been formally studied, is psychological stress in the mother.
Genetic Factors
It has been observed for many years that preterm delivery is a condition that runs in families. This observation plus the recurrent nature of preterm birth and its differing prevalence between races has led to the suggestion of a genetic cause for preterm labor.
Amnionic Fluid and Chorioamnionic Infection
Chorioamnionic infection caused by a variety of microorganisms has emerged as a possible explanation for many heretofore unexplained cases of ruptured membranes and/or preterm labor. Pathogenic bacteria have been recovered at transabdominal amniocentesis from approximately 20 percent of women in preterm labor without evidence of overt clinical infection and with intact fetal membranes. Viral products have also been recovered.
It is postulated that bacterial endotoxin (lipopolysaccharide) introduced into the amnionic fluid stimulates decidual cells to produce cytokines and prostaglandins that may initiate labor. Although the pathway for bacteria to enter the amnionic fluid is obvious after membrane rupture, the route of access with intact membranes is unclear. It has been shown that Escherichia coli can permeate living chorioamnionic membranes. Thus, intact fetal membranes at the cervix are not necessarily a barrier to ascending bacterial invasion of the amnionic fluid. In vitro exposure to bacterial proteases reduces the bursting load of fetal membranes. Thus, microorganisms given access to fetal membranes may be capable of causing membrane rupture, preterm labor, or both.
The interest in a possible microbial pathogenesis of preterm labor has prompted some clinicians to perform amniocentesis to detect occult amniotic fluid infection in women with intact fetal membranes. In centers using amniocentesis in the management of preterm labor with intact fetal membranes, several laboratory methods have been reported helpful for the rapid detection of intra-amnionic infection defined as a positive amnionic fluid culture. A negative Gram stain has been shown to be the most reliable test to exclude amnionic fluid bacteria (specificity 99 percent), and a high interleukin-6 was the most sensitive test (sensitivity 82 percent) in detecting amnionic fluid containing bacteria.
Other microorganisms implicated in preterm birth include bacterial vaginosis (see Chapter 33) and chlamydial infection. Although Chlamydia trachomatis is the most common sexually transmitted bacterial pathogen in the United States, the possible influence of cervical infection with this organism on preterm birth is unclear. The Centers for Disease Control and Prevention guidelines for screening and treatment of chlamydial infection during pregnancy are based on the prevalence of the infection in various populations, for example, teenagers, and on the likely benefit of third-trimester screening and treatment to reduce newborn ophthalmia neonatorum or pneumonitis, rather than reduce the incidence of preterm birth.
For further reading in Williams Obstetrics, 23rd ed.,
see Chapters 6, “Parturition” and 36, “Preterm Birth.”