
Steven Chen
Erin Brown
Presentation
A 58-year-old woman with a newly found breast mass presents for further workup and treatment options. Six months ago, she discovered a palpable mass on her left breast during self-examination. Since this time, it has slowly increased in size. She denies any skin changes or nipple discharge. She has no significant medical history, and she has been in her normal state of health prior to presentation. She denies any personal history of breast cancer but notes that her mother was diagnosed with breast cancer at age 60. Her vital signs are normal. On physical exam, a left-sided breast mass is palpable and measures 5 cm in diameter. There are no overlying skin changes. The right breast is normal without palpable masses. Two palpable lymph nodes are present in the left axilla; the nodes are firm but mobile. There is no supraclavicular or right axillary lymphadenopathy.
Differential Diagnosis
A breast mass with palpable lymph nodes should be considered to be breast cancer until proven otherwise. However, the differential diagnosis also includes a number of benign breast lesions. A breast issue that may cause reactive lymph nodes such as abscess or injury may be a consideration in the right clinical setting. Additionally, other malignancies including malignant phyllodes tumors, angiosarcomas, or metastatic disease (e.g., melanoma) should remain in the differential.
Workup
A thorough history should be undertaken with an emphasis on breast cancer risk stratification. Important risk factors to include are age at menarche and menopause, age at first childbirth, history of breastfeeding, alcohol consumption, hormone use or exposure, family history of breast cancer, and personal history of breast cancer. If a strong family history is present, genetic testing should be considered. Factors that should prompt genetic testing include a first-degree relative diagnosed with breast cancer before the age of 50, three or more first-or second-degree relatives diagnosed with breast cancer at any age, breast cancer in a male relative, bilateral breast cancer in a first-degree relative, or a history of ovarian cancer in two or more first-or second-degree relatives. Prior to initiating genetic testing, counseling should be initiated to ensure that the risks and benefits of testing for the individual and her family are understood.
Due to the presence of a palpable mass in this patient, the next step is a bilateral mammogram in combination with ultrasound of the mass and the ipsilateral axilla. An MRI may be considered at this stage to evaluate the extent of the primary lesion (including invasion into the skin or deep structures), and to rule out occult lesions in either breast or axilla. Needle biopsies should be obtained for histologic confirmation of the suspected diagnosis. Fine needle aspiration is most commonly used for biopsy of lymphadenopathy; however, core biopsy is the gold standard for biopsy of the breast mass because of its ability to preserve cell architecture. FNA should be avoided for biopsy of a solid breast lesion if a core is possible. The use of ultrasound or imaging to ensure proper sampling is encouraged, particularly if the tumor or lymph nodes are at all indistinct to palpation. Tissue specimens that demonstrate breast cancer are analyzed for ER, PR, and Her2/neu at a minimum. Consideration for distant metastases should also be entertained for those with locally advanced disease. Screening laboratory studies may include a CBC, liver function test, and alkaline phosphatase. In locally advanced breast cancer, a bone scan and CT chest and abdomen and pelvis should be obtained. PET/CT scan may also be substituted for the CT chest, abdomen, and pelvis.
This patient’s workup confirms the left breast mass to be 5.2 cm in diameter based on imaging and is categorized as BI-RADS 5 (highly suggestive of malignancy). No radiographic abnormalities are noted within the right breast; however, two morphologically abnormal lymph nodes are detected in the left axilla. Biopsy reports reveal that both the breast and the lymph node biopsies are consistent with infiltrating ductal carcinoma. Tissue markers reveal an ER-positive, PR-positive, Her2-negative breast cancer. Metastatic workup is negative for any distant metastases.
Diagnosis and Treatment
The diagnostic workup is complete and consistent with the suspected diagnosis of locally advanced breast cancer. The tumor is 5.2 cm in diameter based on imaging without local extension (T3 provisionally), metastases to at least two lymph nodes (N1 provisionally), and no evidence of distant metastases (M0). This corresponds with a stage III breast cancer. For locally advanced breast cancer, two treatment options exist: primary surgical management followed by chemotherapy versus neoadjuvant chemotherapy followed by surgery. In either case, both would then be followed by radiation therapy and hormonal therapy in this case.
Surgical management may be either mastectomy or breast-conserving surgery (also known as lumpectomy, wide local excision, or partial mastectomy). Either surgical technique will also require complete axillary dissection in this patient due to the confirmed presence of palpable metastatic lymph nodes. In order to proceed with breast-conserving surgery (BCS), the surgeon must be able to remove the mass with negative margins while maintaining acceptable cosmetic results. Therefore, multiquadrant disease and large tumor size relative to breast size are traditionally considered relative contraindications to BCS. Furthermore, BCS for locally advanced cancer should always be accompanied by radiation therapy, so the patient must not have any contraindications to radiation such as prior history of radiation to the chest wall, connective tissue disease such as lupus and scleroderma, or active pregnancy during the planned time of radiation therapy. If a patient with locally advanced breast cancer desires BCS, but does not meet size criteria, has an inoperable tumor, or evidence of inflammatory breast cancer, neoadjuvant chemotherapy should be strongly considered.
The ultimate decision about BCS versus mastectomy should be made by a well-informed patient in consultation with the operating surgeon. When approaching the discussion with each patient, the surgeon must inform the patient of the risks and benefits of each surgical approach but should be prepared to provide guidance about the entire sequence of care. BCS benefits include preservation of the breast and a smaller operation; cons include increased rate of recurrence and risk of positive margins requiring further surgery. The pros of modified radical mastectomy include decreased recurrence and only one operation unless reconstruction is planned. However, the disadvantage of mastectomy is removal of the breast and the need for reconstruction if a breast mound is desired.
Neoadjuvant therapy involves chemotherapy or hormonal therapy prior to surgical therapy. The goal is to reduce the tumor burden in order to pursue breast conserving surgery or to pursue surgery in otherwise nonoperable or difficult to operate on tumors. Original concerns regarding induction chemotherapy included fear of decreased survival due to delaying surgery and increased surgical complication rates due to negative effects of chemotherapy on wound healing.
Studies report no difference in rates of seroma formation, wound infection, or delayed wound healing between neoadjuvant and primarily surgical groups. Additionally, multiple studies have shown equivalent survival rates among patients randomized to neoadjuvant chemotherapy in comparison to those randomized to primary surgical approach followed by postoperative chemotherapy. Furthermore, studies such as the NSABP trials have shown higher rates of BCS after preoperative chemotherapy due to significant reductions in tumor size.
Surgical Approach
Breast-Conservation Surgery
As described above, the goal of BCS is to remove the tumor with adequate margins as well as acceptable cosmetic results. In order to achieve this result, preoperative surgical planning is of the utmost importance. For the nonpalpable lesion, preoperative localization is essential. A wire localized technique using a preoperative wire placed by ultrasound or stereotactic methods can be helpful. Other potential localization technologies may include placement of a radioactive seed or biopsy hematoma directed surgery. This approach is usually not needed for an easily palpable mass such as the patient in this case. The incision should be made as close to the center of the breast as feasible while facilitating dissection to allow for future re-excision via mastectomy. Sharp or blunt dissection is used to remove the mass with the goal of 1-cm margins in all directions. After excision of the mass, many radiation oncologists prefer that the cavity walls be marked for potential radiation boost unless a balloon-based accelerated breast irradiation catheter is to be used. Margins of the specimen should be marked or separately submitted shave margins should be performed. Lastly, attention should be paid to hemostasis and closure of the defect. Simple closure is sufficient in many cases; however, complex closure may be necessary to prevent skin dimpling from a large cavity. For large excisions, an oncoplastic approach based on breast reduction principles may be beneficial to improve cosmesis and to facilitate wide margins while minimizing cosmetic impact to the shape of the breast. It is important, however, to ensure that the desire for an improved cosmetic outcome does not compromise the planned excision of the tumor and margins itself. Potential pitfalls of lumpectomy mainly relate to poor cosmetic effect and the possible need for further surgeries due to inadequate or grossly positive margins.
Complete Axillary Lymph Node Dissection
In the absence of clinically palpable nodes or previously biopsied lymph nodes negative for metastatic disease, sentinel node biopsy should be performed in order to spare the morbidity of a complete axillary dissection. This may be performed before or after neoadjuvant chemotherapy, although it is important to note that performing this after neoadjuvant chemotherapy slightly increases the false-negative rate. Most surgeons use a combination approach for locating the sentinel node that includes injection of both a blue dye (either methylene blue or isosulfan blue) and a radioactive tracer (typically technetium-99), although either can be used alone by experienced surgeons. The patient should be placed in the supine position, and the ipsilateral arm should be prepped and draped in order to allow manipulation of the arm during the procedure. Any radioactive and/or blue lymph nodes are dissected free and sent for pathologic examination. If negative for metastatic disease, no further dissection is required; however, positive metastatic disease is an indication to proceed with complete axillary dissection.
To proceed with complete axillary dissection, an incision is made just inferior to the axillary crease. First, the lateral edge of the pectoralis major and latissimus dorsi muscles are then identified. Beneath the pectoralis major is the pectoralis minor muscle, which defines the levels of axillary lymph nodes with level I nodes below, level II nodes posterior to, and level III nodes superior to the muscle. A complete axillary dissection involves the removal of all three levels of nodes. In the absence of clinically positive nodes that extend into level III, only level I and II nodes are removed. To proceed with dissection, the interpectoral tissues, including Rotter’s nodes, are dissected free. Next, the axillary vein is identified and the overlying fascia in incised; the tissue is freed with great care to spare the lymphatics superior to the vein. Care must be taken to identify and preserve several important structures during axillary dissection: the serratus anterior muscle, the thoracodorsal nerve, and the long thoracic nerve. Potential pitfalls for complete axillary dissection include overskeletonization of the axillary vein, which may lead to increased risk of upper extremity lymphedema or injury to the axillary, long thoracic, or thoracodorsal nerves. Dissection above the axillary vein may also result in injury to the brachial plexus and should be avoided whenever possible (Figure 1).
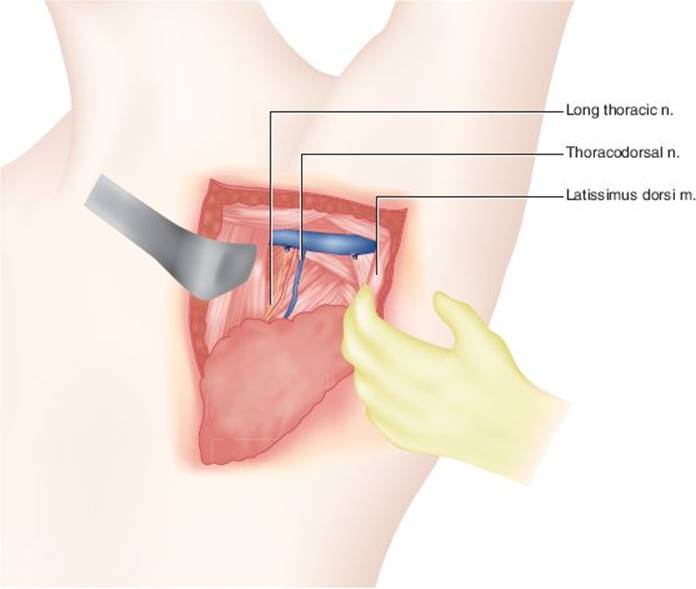
FIGURE 1 • Schematic of axillary lymph node dissection with preserved structures
Modified Radical Mastectomy
As in BCS, the goal of modified radical mastectomy (MRM) is to remove the mass with adequate margins. In the case of locally advanced breast cancer, mastectomy is the most common surgical technique due to large tumor size even when neoadjuvant chemotherapy is pursued. To begin, an elliptical incision is made extending from just medial to the sternum to the midaxillary line, and skin flaps are created by dividing Cooper’s ligaments with the aid of countertraction. This is done by using electrocautery, sharp dissection, or a tumescent technique. The outer borders of dissection should extend to the lateral edge of the sternum medially, the latissimus dorsi laterally, the clavicle superiorly, and the inframammary fold inferiorly (which often takes one onto the rectus sheath). Care must be taken to completely excise the pectoralis fascia with the breast tissue. Technique varies depending on whether reconstruction is planned (either immediately following mastectomy or in the future). If reconstruction is planned, as much skin as possible should be preserved. In some select cases, the skin of the nipple-areola complex can be spared, but a complete excision of the underlying ductal tissue within the nipple papule should be performed. This is generally avoided in tumors that are close to the nipple for fear of tumor extension into the ducts within the nipple. In addition, biopsy of the tissue posterior to the complex should be obtained to ensure a negative margin. Without reconstruction, enough skin should be excised to allow closure without tension while avoiding skin overlap. Potential pitfalls include incomplete excision of the axillary tail leaving behind potentially cancerous cells, inappropriate thickness of the flaps (if too thick, potential for recurrence is increased, but if too thin, flap necrosis may occur), trauma to the flap causing skin breakdown and necrosis, and unnecessarily crossing the midline.
Special Intraoperative Consideration
During an operation for advanced breast cancer, a possible nonroutine finding is invasion of the tumor into the pectoralis muscle. In this case, the involved muscle must also be resected and included with the specimen.
Postoperative Management
After mastectomy, drains should be left in place to prevent seroma formation. Patients may quickly resume a regular diet and return to normal activities within a few weeks. All patients with locally advanced breast cancer should be considered for adjuvant therapy. This includes chemotherapy and hormonal therapy. Those with ER+ tumors will likely need hormonal therapy. Premenopausal patients typically receive tamoxifen, while postmenopausal patients receive an aromatase inhibitor for a total of 5 years. For patients with Her2/neu-positive tumors, therapy with the monoclonal antibody trastuzumab is recommended for 1 year.
Radiation therapy is indicated in all patients after BCS and in specific instances after mastectomy. In the case of greater than or equal to four positive nodes, tumor size larger than 5 cm, or grossly positive margins after mastectomy, radiation should be performed. If one to three nodes are positive or margins are inadequate, radiation should be strongly considered according to NCCN guidelines. The specific details of the various chemotherapy and radiation regimens are complex and beyond the scope of this chapter. This complexity emphasizes the importance of a team approach to breast cancer treatment involving a medical oncologist, radiation oncologist, surgical oncologist, and plastic surgeon.
Education regarding prognosis and surveillance are also crucial components of breast cancer treatment. The most important prognostic indicators for recurrence and death include age, comorbidities, tumor staging, and number of positive nodes. In general, stage I and II breast cancers have a 5-year disease-free survival between 65% and 92%. Stage III breast cancers have a 5-year disease-free survival of 44% to 47%, and a patient with a stage IV breast cancer diagnosis can expect a 5-year disease-free survival rate of 14%. Monitoring for recurrence is essential. Annual mammogram should begin 6 months after the completion of radiation and/or chemotherapy. Women should have a clinical breast exam performed by their physician every 4 to 6 months for the first 5 years and then annually thereafter. Finally, woman taking tamoxifen with an intact uterus should have a yearly pelvic exam due to increased risk of endometrial cancer.
SUGGESTED READINGS
American College of Radiology. Practice Guideline for the Performance of Contrast-Enhanced MRI of the Breast. Revised 2008. http://www.acr.org/SecondaryMainMenuCategories/quality_safety/guidelines/breast/mri_breast.aspx. Accessed: December 22, 2011.
Carlson RW, et al. The NCCN Breast Cancer Clinical Practice Guidelines in Oncology. J Natl Compr Canc Netw. 2009;7(2):122–192.
Overgaard M, et al. Postoperative radiotherapy in high-risk postmenopausal breast-cancer patients given adjuvant tamoxifen: Danish Breast Cancer Cooperative Group DBCG 82c randomized trial. Lancet. 1999;353:1641–1648.
Overgaard M, et al. Postoperative radiotherapy in high-risk premenopausal women with breast cancer who receive adjuvant chemotherapy. Danish Breast Cancer Cooperative Group 82b Trial. N Engl J Med. 1997;337: 949–955.
Rastogi P, et al. Preoperative chemotherapy: updates of National Surgical Adjuvant Breast and Bowel Project Protocols B-18 and B-27. J Clin Oncol. 2008;26(5):778–785.
Sabel MS, et al. Sentinel node biopsy prior to neoadjuvant chemotherapy. A J Surg. 2003;186:102–105.
Silverstein MJ, et al. Image-detected breast cancer: stateof-the-art diagnosis and treatment. J Am Coll Surg. 2009;7(6):504–520.
Vilarino-Varela M, et al. Current indications for postmastectomy radiation. Int Semin Surg Oncol. 2009;6:5.