
Marci D. Jones, Rodrigo Santamarina, and Lance G. Warhold
DEFINITION
 Acute compartment syndrome is a condition in which increased tissue pressure compromises the circulation within the enclosed space of fascial compartments. As a result of this elevated interstitial pressure, the blood supply to the soft tissues is impaired. If left untreated, elevated pressures can cause irreversible muscle and nerve damage resulting in fibrosis and contracture.
ANATOMY
Compartment syndrome is most common in the forearm and hand but can occur in the arm and in the finger.
The arm is divided into two fascial compartments, the forearm into three compartments, the hand into ten compartments, and the finger into two compartments.
The two arm compartments are the anterior and posterior, separated by the medial and lateral intermuscular septa (FIG 1A).
 The anterior arm compartment contains the biceps brachii, brachialis, and coracobrachialis.
The posterior arm compartment contains the triceps brachii.
The forearm consists of three compartments: the volar, the dorsal, and the mobile wad of three (FIG 1B).
The contents of the volar compartment include the flexor muscles and can be subdivided into superficial and deep components. The superficial muscles are the flexor carpi ulnaris, palmaris longus, pronator teres, and flexor carpi radialis. The deep muscles are the flexor digitorum superficialis and profundus, and the flexor pollicis longus.
The dorsal compartment of the forearm contains the extensor muscles. The superficial extensors include the extensor digitorum communis, extensor digiti minimi, and extensor carpi ulnaris. The deep layer includes the supinator, abductor pollicis longus, extensor pollicis longus, extensor pollicis brevis, and extensor indicis.

FIG 1 • A. Compartments of the arm. (continued)

FIG 1 • (continued) B. Compartments of the forearm. C. Compartments of the hand.
The mobile wad of three is a distinct muscle compartment that contains the brachioradialis, extensor carpi radialis longus, and extensor carpi radialis brevis.
The wrist has one significant closed space, the carpal tunnel. Although not a compartment in the strictest sense, increased pressure in this tunnel can be detrimental to the median nerve.
The hand contains ten distinct compartments (FIG 1C).
There are seven compartments for the interossei. Each of the four dorsal and three palmar interossei has a separate compartment.
The adductor compartment contains the adductor pollicis.
The thenar compartment contains the abductor pollicis brevis, the opponens pollicis, and the flexor pollicis brevis.
The hypothenar compartment contains the abductor digiti minimi, flexor digiti minimi, and opponens digiti minimi.
Compartment syndrome can also occur in the finger due to the limited skin compliance from the multiple fascial attachments.
PATHOGENESIS
Increased pressure within a compartment decreases the blood supply to the soft tissues and can result in tissue ischemia and ultimately necrosis. The blood flow to a compartment is determined by several factors, including venous pressure, arterial pressure, and local interstitial pressure. Increased capillary permeability results from muscle ischemia. This increased permeability leads to intramuscular edema, increases the tissue pressure, decreases blood flow and oxygen transport, and leads to more tissue damage. It is easy to appreciate the vicious cycle that escalates the pathophysiology of the compartment syndrome.
Many conditions are associated with compartment syndrome. These can be divided into two major categories3 :
Conditions that decrease compartment volume (tight casts or dressings, burn eschar, limb lengthening or application of traction, increased external pressure on limb from prolonged weight [lying on limb or entrapment under a weight])
Conditions that increase compartment contents (bleeding—arterial or venous injury, anticoagulation, trauma, reperfusion injury, edema, infiltrated infusion, snakebite, infection, high-pressure injection)
NATURAL HISTORY
Compartment syndrome results in hypoxic cell damage and ultimately anoxic cell death. Functional changes occur in muscle after 2 to 4 hours of total ischemia. Hypoxia to nerves causes paresthesia and hypoesthesia within 30 minutes of ischemia, but irreversible nerve damage may not occur until 12 hours or more of total ischemia.
An untreated compartment syndrome can result in permanent neural deficit, tissue necrosis, growth arrest, Volkmann contracture, and even wet gangrene.
PATIENT HISTORY AND PHYSICAL FINDINGS
It is important to elicit a detailed history and evaluate the possible causes of compartment syndrome (discussed above).
Pain out of proportion to physical findings is the most important finding. For patients with this finding, one must have a high clinical suspicion regardless of the presumed severity of the inciting event.
Most commonly, patients will present with a history of trauma or a crushing injury; however, other causes must not be overlooked.
Compartment syndrome may involve single or multiple compartments in the extremity.
Physical examination findings include:
A tense, swollen, and tender compartment (FIG 2)
Pain with passive stretch of the muscles within the compartment
Paresthesias or sensory disturbances in the nerve distribution of the compressed nerve are intermediate findings. This can be accompanied by motor weakness. Motor paralysis is a later finding.
Pallor and pulselessness are late findings.
The findings of pain out of proportion to physical examination, a tense compartment, and pain with passive stretch are sufficient to warrant intracompartmental pressure measurements. One should not delay definitive diagnosis and treatment until later findings are present.
In obtunded or sedated patients, a tense, swollen compartment is sufficient to warrant intracompartmental pressure measurements.

FIG 2 • Diffuse, tense swelling of the hand. A. Palmar view with loss of palmar concavity. B. Radial view.
IMAGING AND OTHER DIAGNOSTIC STUDIES
Clinical examination is the cornerstone of the diagnosis, and it is important to have a high degree of suspicion for compartment syndrome.
Immediate fasciotomy is indicated in patients with unequivocal symptoms and signs of compartment syndrome. Direct measurement of compartment pressures is indicated in all cases when the patient’s symptoms and physical examination signs are indicative of compartment syndrome, and it is especially important in patients who are obtunded or sedated.
Diagnosis of compartment syndrome of the finger is made clinically and not through the use of pressure measurement.
Pressure measurement in the arm is made in both anterior and posterior compartments. Anteriorly, the pressure is measured over the biceps muscle, and posteriorly over the triceps muscle.
The physician must be careful not to injure the radial nerve when measuring the arm compartment pressure. The nerve courses deep to the triceps in the spiral groove of the humerus. Ten centimeters proximal to the lateral epicondyle, it passes through the lateral intermuscular septum to the anterior compartment.
In the forearm, the pressure is measured over the palmar, mobile wad, and dorsal compartments.
The median and ulnar nerves are at risk during measurement of the palmar compartment. The ulnar nerve courses deep to the flexor carpi ulnaris in the ulnar forearm; the median nerve is between the flexor digitorum superficialis and profundus muscles.
When measuring the mobile wad, the superficial branch of the radial nerve is deep to the brachioradialis in the forearm but emerges between the brachioradialis and extensor carpi radialis longus tendons about 8 cm proximal to the radial styloid.
 The posterior interosseous nerve courses around the radial neck in the proximal radial forearm and should be avoided when measuring the mobile wad and dorsal compartments.
In the hand, pressure measurements should be made in the affected compartments; measurements are generally made in the area of the planned incisions.
There is not an absolute increased compartment pressure that warrants fasciotomy. When the pressure approaches 30 to 45 mm Hg, or 30 mm Hg less than the diastolic pressure, with concordant physical examination findings, decompressive fasciotomy should be performed.4 In the hand, lower pressures (15 to 20 mm Hg) may indicate compartment syndrome.
Plain radiographs should be performed to evaluate any underlying bony abnormality. Fractures and dislocations should be reduced as anatomically as possible.
Arterial injury can lead to ischemia and can present similarly. Arteriography is indicated if the history may be significant for arterial injury (fracture, avulsion, or laceration).
DIFFERENTIAL DIAGNOSIS
Arterial injury
Nerve injury
NONOPERATIVE MANAGEMENT
There is no role for nonoperative management of an acute compartment syndrome. In acute cases of compartment syndrome with elevated compartment pressure, prompt decompressive fasciotomies are required to relieve tissue ischemia.
In patients with early symptoms and signs of compartment syndrome, but without elevated compartment pressures, removal of all compressive dressings and casts, and elevation of the affected extremity to the level of the heart is indicated.
Frequent close monitoring by physical examination and repeated pressure measurements as necessary are critical.
In patients presenting late with aseptic muscle necrosis, acute fasciotomy and débridement may not be indicated.
SURGICAL MANAGEMENT
Preoperative Planning
The surgeon should review radiographs and plan for surgical stabilization as necessary.
Positioning
The patient is positioned supine on the operating table with the upper extremity on an armboard.
Tourniquets are not routinely used during decompressive fasciotomy.
If the arm is affected, the shoulder and axilla are included in the sterile field to allow exposure to the entire extremity.
Approach
Skin is considered a significant compressive structure, and it is important to create a skin incision of sufficient length to allow complete decompression. Cosmesis is not a concern.
Incisions are planned to afford complete and rapid decompression of the compartments while maintaining coverage of vital structures and avoiding joint contractures due to scarring.
The viability of muscles is determined by muscle tone and color, contractility, and bleeding.
If the viability is still unclear, the muscle should be left alone and reinspected in 24 to 48 hours.
The skin is left open and the wounds are copiously irrigated and covered with wet saline dressings. Occasionally, a wound vacuum dressing can be applied to facilitate care and reduce edema and pain associated with frequent dressing changes.
Once the wound is considered to be stable and clean, the skin can be closed if under no tension. If tension is present, split-thickness skin grafts are usually applied.
TECHNIQUES
DECOMPRESSION OF THE ARM
 Compartment syndrome of the arm is rare. It can be approached from the lateral, posterior, or anteromedial approach.
 The choice of incision may be based on the need for fracture fixation.1,2
The lateral approach begins at the deltoid insertion and extends to the lateral epicondyle. The fascia overlying the biceps anteriorly and triceps posteriorly is split through the incision (TECH FIG 1A).
The anteromedial approach extends from the medial epicondyle toward the axilla, and the fascia overlying the biceps and triceps is split (TECH FIG 1B). This incision can be continued from the forearm skin incisions.
The ulnar nerve must be protected in this approach.
For isolated posterior compartment syndrome, a posterior incision can be made from 8 cm distal to the acromion to the olecranon6 (TECH FIG 1C). The triceps fascia is directly exposed and incised.
The radial nerve runs between the long and lateral heads of the triceps and is at risk during muscle débridement.

TECH FIG 1 • A. Lateral approach to the arm. B. Anteromedial approach to the arm. C. Posterior approach to the arm.
DECOMPRESSION OF THE VOLAR FOREARM
Design a curvilinear incision from the carpal tunnel to the antecubital fossa. A complete carpal tunnel release is indicated if symptoms of median nerve compression are present (TECH FIG 2).
Start the incision distally between the thenar and hypothenar eminences in line with the radial border of the ring finger. Release the skin, palmar fascia, and transverse carpal ligament.
Continue the incision proximally to the distal wrist crease, then curve it ulnarly to the pisiform and extend it proximally along the ulnar side of the distal forearm.
This prevents exposure of the flexor tendons and median nerve and protects the palmar cutaneous branch of the median nerve.
Curve the incision radially in the mid-forearm and then just anterior to the medial epicondyle at the elbow.
Creation of this flap provides coverage of the median nerve.
At the antecubital fossa, curve the incision slightly anteriorly to meet the incision of the arm, if necessary.
This prevents a linear incision at the level of the elbow and provides coverage for the brachial artery.
Release the fascia covering the superficial and deep compartment of the forearm, as well as the mobile wad, through this incision. Release the lacertus fibrosis at the elbow. Release individual muscle fascia if release of the compartment fascia does not relieve the pressure within each muscle.
Loosely close the wound over the carpal tunnel; it is generally left open over the forearm.
If the swelling is mild, the fascia may be left open and the skin closed, or the skin edges may be approximated with a vessel loop-stapling technique.
If the wound is left open, it is covered with a sterile nonocclusive dressing. Alternatively, a VAC dressing may be applied.
An alternative incision uses the Henry approach between the brachioradialis and the flexor carpi radialis, connecting to the carpal tunnel distally and proximally crossing the antecubital fossa obliquely from radial to ulnar.
If this approach is used, take care not to injure the palmar cutaneous branch of the median nerve at the wrist.
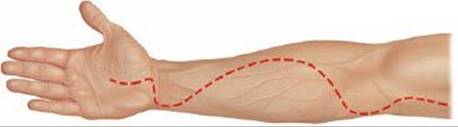
TECH FIG 2 • Incision for decompression of the palmar forearm. Note the incision in the hand used here for release of the thenar compartment.
DECOMPRESSION OF THE DORSAL FOREARM
The wound is managed in a similar way to that described for the volar forearm fasciotomy.
In the forearm, release of the volar compartment and mobile wad may decrease the pressure in the dorsal compartment. Once the palmar fasciotomy has been performed, the dorsal compartment should be re-evaluated for the need for fasciotomy.
Make a longitudinal dorsal incision just ulnar to the tubercle of Lister and extending proximally toward the lateral epicondyle. Release the fascia over the dorsal compartment (TECH FIG 3).
Release individual muscle fascia if necessary.
If posterior interosseous nerve involvement is suspected, separate the extensor carpi ulnaris and extensor digitorum communis muscles to expose and release the fascia overlying the supinator.

TECH FIG 3 • Incision for approach to the dorsal forearm.
DECOMPRESSION OF THE HAND COMPARTMENTS
To release the four dorsal and three palmar interosseous compartments and the adductor compartment, make two dorsal longitudinal incisions over the second and fourth metacarpals (TECH FIG 4A).
Take the incisions to the level of the extensor tendons. Avoid the sensory branches of the radial and ulnar nerves, and preserve dorsal veins to minimize postoperative edema.

TECH FIG 4 • Incisions for the release of the hand compartments. A. Dorsal. B. Thenar and hypothenar. C. Incisions over dorsal, thenar, and hypothenar compartments. These incisions were left open.
Retract the extensor tendons and the dorsal surface of the metacarpal. Release the dorsal compartments on each side of the metacarpal (the first and second dorsal compartments are reached on either side of the second metacarpal, and the third and fourth dorsal compartments are found on either side of the fourth metacarpal). Continue blunt dissection palmarly through the dorsal interosseous to release the three palmar interosseous compartments.
Release the adductor compartment through the incision over the second metacarpal.
Release the thenar compartment through a longitudinal incision along the radial border of the thumb metacarpal, and release the hypothenar compartment through an incision along the ulnar border of the fifth metacarpal (TECH FIG 4B). Split the underlying fascia longitudinally.
The wounds are left open (TECH FIG 4C) and the hand is placed in a bulky splint in intrinsic-plus position (metacarpophalangeal joints flexed 70 degrees and interphalangeal joints extended).
DECOMPRESSION OF THE FINGER
Make longitudinal midaxial incisions along the finger. These incisions are made by connecting the most dorsal portions of the joint flexion creases (TECH FIG 5A). These are more easily seen with the finger in flexion.
Avoid making a more palmar, midlateral incision to prevent postoperative flexion contracture.
Carefully divide the transverse retinacular ligament and Cleland’s ligament to release the neurovascular bundles on both radial and ulnar sides (TECH FIG 5B).
If possible, loosely approximate the skin.

TECH FIG 5 • A. Incision for the release of the finger. Dots are placed at the apex of each flexion crease, and connecting the dots provides the midaxial line. B. Division of the transverse retinacular ligament and Cleland’s ligament.


FIG 3 • Wound coverage after second look with delayed primary closure and split-thickness skin grafting.
POSTOPERATIVE CARE
A second look is planned 48 to 72 hours after the index procedure.
Additional débridement of devitalized tissue is performed. Serial débridements are performed until no devitalized tissue remains.
Delayed primary closure of the skin (not fascia) may be possible. More frequently, split-thickness skin grafting is performed to cover the wounds (FIG 3). If significant soft tissue has been lost with exposed tendon, nerve, or bone, flap coverage is planned.
Wound coverage should be performed as soon as possible to minimize complications such as infection, desiccation, and amputation.
The upper extremity should be elevated and splinted in an intrinsic-plus position. Gentle active and active assisted range of motion of the hand, wrist, and elbow should be initiated as soon as swelling begins to subside, generally within 2 to 3 days after wound closure. Placement of a flap or skin graft may preclude motion at certain joints, but unaffected joints should be ranged.
OUTCOMES
The outcome after compartment release depends both on the severity of the initial injury and the time elapsed before release.
Patients with prompt diagnosis and treatment and limited devitalized tissues generally have favorable outcomes.
Patients with severe initial injuries, delayed treatment, or extensive tissue necrosis have a more guarded prognosis for functional recovery of the upper extremity.
COMPLICATIONS
Volkmann ischemic contracture is the result of untreated acute compartment syndrome.
Necrosis and fibrosis of the muscle occur, with a resultant claw hand deformity. This deformity is due to extrinsic flexor and extensor contracture with concomitant intrinsic muscle dysfunction.
Nerve dysfunction results either from the initial ischemic injury or from subsequent compressive neuropathy due to the dense scarring of the tissues surrounding the nerves.
The deeper compartments are more severely compromised, with the flexor digitorum profundus alone affected in milder cases, and fibrosis of all muscles in the most severe.
REFERENCES
1. Antebi E, Herscovici D Jr. Acute compartment syndrome of the upper arm: a report of 2 cases. Am J Orthop 2005;34:498–500.
2. Diminick M, Shapiro G, Cornell C. Acute compartment syndrome of the triceps and deltoid. J Orthop Trauma 1999;13:225–227.
3. Gulgonen A. Compartment syndrome. In: Green DP, Pederson WC, Hotchkiss RN, et al, eds. Green’s Operative Hand Surgery, 5th ed. New York: Elsevier Churchill Livingstone, 2005:1985–2006.
4. Whitesides E, Heckman MW. Acute compartment syndrome: update on diagnosis and treatment. J Am Acad Orthop Surg 1996;4:209–218.
5. Yabuki S, Kikuchi S. Dorsal compartment syndrome of the upper arm: a case report. Clin Orthop Relat Res 1999;366:107–109.