
Laura E. Mitchell
Oral clefts (OCs), including cleft lip with or without cleft palate (CL/P) and isolated cleft palate (CP), comprise one of the most commonly occurring groups of human malformations. These malformations have a profound influence on the basic human condition, affecting appearance, nutrition, and communication, and require long-term, multidisciplinary treatment. Given the prevalence, severity, and economic consequences of OCs, it is not surprising that there has been extensive research into their etiology and inheritance.
It is generally recognized that CL/P and CP are, with rare exceptions (e.g., Van der Woude's syndrome), etiologically distinct conditions (Fogh-Andersen, 1942). Further, even within these two groups, there is causal heterogeneity; i.e., identical cleft malformations may occur as the result of different underlying factors. Over 300 recognized causes of OCs have been identified (Gorlin et al., 1990), including teratogenic exposures (e.g., antiepileptic medications), chromosomal abnormalities (e.g., deletion of chromosome 22qll), and single-gene disorders (e.g., Van der Woude's syndrome). However, such factors tend to be individually rare and are estimated to account for only 30% of CL/P and 50% of CP cases (Jones, 1988; Gorlin et al., 1990; Saal, 1998).
At present, a specific causative agent(s) cannot be identified for the majority (50%-70%) of OCs. In some cases, these OCs occur in association with additional malformations and are likely to be attributable to as yet unidentified teratogens, subtle chromosomal abnormalities (e.g., microdeletions), or unrecognized single-gene defects. However, in many cases, the OC occurs in isolation. This latter group constitutes the so-called nonsyndromic OCs and is the focus of the remainder of this chapter.
For both nonsyndromic CL/P and CP, the most consistently identified risk factor is the presence of a positive family history. The observed familial recurrence patterns provide strong evidence for a genetic contribution to both conditions since the risks to relatives of affected individuals are much higher than would be expected if familial aggregation was attributable to the effects of a shared environment (Khoury et al., 1988). However, the familial recurrence patterns for both CL/P and CP are also inconsistent with the segregation of a single fully penetrant Mendelian disease locus. Nonsyndromic CL/P and CP are, therefore, classified as genetically complex traits (Wyszynski et al., 1996), but their specific mode of inheritance has not been clearly defined.
Mode of Inheritance
The ability to establish mode of inheritance for a given condition is important for at least two reasons. Knowledge of mode of inheritance allows for more accurate genetic counseling of affected individuals and their relatives. In particular, when mode of inheritance is known, recurrence risks can be based on an understanding of the underlying disease etiology rather than on empiric estimates. In addition, an understanding of mode of inheritance is important when designing studies aimed at the identification of disease-causing or predisposing loci.
One vs. Many
Efforts to determine the mode of inheritance of nonsyndromic CL/P and CP have been guided limited by the methods that prevailed during a given period. Early investigators invoked modifications of simple Mendelian inheritance (Fogh-Andersen, 1942). However, such models were largely unsatisfactory to explain the observed familial recurrence patterns for these conditions, which are characterized by monozygotic twin concordance rates less than 100%, a nonlinear decline in risk to relatives with decreasing degree of genetic relationship to the proband, and recurrence risks that are dependent on the severity of the proband's defect as well as the number of affected family members (Carter, 1969).
During the 1960s, it was recognized that multifactorial threshold models, which were originally developed to explain the inheritance of continuously distributed traits, could also be applied to discrete traits such as CL/P and CP (Falconer, 1965). Under the multifactorial threshold model, liability to a discrete trait is assumed to be determined by the equal, additive, and relatively small effects of numerous genetic and environmental risk factors and to be normally distributed. Further, the observed dichotomy in phenotypic expression is determined by a threshold beyond which individuals are affected. Such models can account for monozygotic twin concordance rates of less than 100%, nonlinear declines in risk to relatives as a function of the of degree genetic relationship, and risks that are dependent on the severity of the proband's defect and/or the number of affected family members.
The multifactorial threshold model quickly gained acceptance as an appropriate model for the inheritance of many common congenital anomalies, including CL/P and CP. However, the assumptions underlying this model have been criticized as being unrealistic. In addition, it was not until the methods of complex segregation analysis were developed (see Chapter 18 for details) that the fit of multifactorial threshold and single-gene (i.e., Mendelian) models of inheritance to observed familial recurrence patterns could be directly compared.
Complex segregation analyses can explicitly evaluate single major locus vs. multifactorial threshold models of inheritance. Several such analyses of CL/P have been conducted (Demenais et al., 1984; Marazita et 1986, 1992; Chung et al., 1986, 1989; Hecht et al., 1991; Nemana et al., 1992; Ray et al., 1993; Clementi et al., 1995), but no clear picture had emerged from these studies (Mitchell, 1997). In those instances where it was possible to discriminate between alternate models of inheritance for CL/P, the best-fitting models varied widely and included multifactorial inheritance as well as both autosomal recessive and autosomal dominant single-gene models with and without an additional multifactorial component. Although fewer segregation analyses have been performed for CP (Chung et al., 1974; Demenais et al., 1984; Pietrzyk et al., 1985), conclusions regarding the best-fitting models of inheritance are also inconsistent. (A summary of the various modes of inheritance that have been proposed for CL/P and CP is provided in Chapter 18.)
The inconsistent results obtained from complex segregation analyses of CL/P and CP may be attributed to genetic heterogeneity; i.e., the genetic mechanisms underlying these conditions may differ across populations. However, given the similarity of CL/P and CP familial recurrence patterns across populations (particularly Caucasian populations), it is more likely that these differences reflect the relatively low power of segregation analyses to discriminate between single-locus and multifactorial models of inheritance (Smith, 1971; Ott, 1990).
Shifting Paradigms
The multifactorial threshold and single-gene models that are evaluated in the context of complex segregation analysis represent two extreme classes of inheritance. It is generally recognized that the mode of inheritance of many conditions, including CL/P and CP, is likely to lie between these two extremes. However, only in the very recent past has there been much interest in defining more precisely the mode of inheritance for such conditions. This interest follows from advances in molecular genetics that offer the possibility of identifying genes that contribute to the development of non-Mendelian or complex traits and the realization that an understanding of mode of inheritance is important when designing studies to identify such genes (Risch, 1990a,b; Lander and Schork, 1994).
Although mode of inheritance questions are difficult to answer definitively, familial recurrence studies can offer some clues (Risch, 1990b). For a dichotomous trait, such as CL/P or CP, familial recurrence is often expressed as the ratio of risk to relatives of an affected individual compared to the population prevalence, denoted λR. The subscript R denotes the type of relation (M, monozygotic twins; S, sib; 1, parent/offspring; 2, second-degree relative; 3, third-degree relative). For example, if the risk of CL/P in the offspring of affected individuals is 0.03 and the prevalence of CL/P in the population is 0.001, then λ1 0.03/0.001 or 30.
The pattern of decline in λR - 1 with decreasing degree of unilineal relationship is determined by the underlying genetic model (Risch, 1990b). When a single gene contributes to disease risk, λR - 1 decreases by a factor of 2 with each degree of unilineal relationship, using the parent-offspring relationship for the first-degree relatives. If the parent-offspring risk is the same as the sib risk (i.e., the dominance variance is 0), this pattern will also hold for sibs and monozygotic twins. Under single-locus inheritance, the expected risk ratio to second-degree relatives is, therefore, obtained by solving the following equation for λ2,
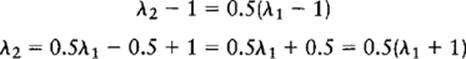
The expected risk ratio to third-degree relatives (λs) is obtained in a similar fashion. Hence, assuming a single-locus model of inheritance and λ1 = 30, the risk ratios for second- and third-degree relatives of individuals with CL/P are expected to be 15.5 and 8.25, respectively.
If a trait is determined by multiple loci that act in an additive fashion or by multiple independent loci (i.e., loci that are each sufficient to cause disease), λR - 1 will also decline by a factor of 2 with each degree unilineal relationship. Hence, the expected familial recurrence pattern is identical under single-locus, multiple additive loci, or multiple independent loci models of inheritance and familial recurrence studies cannot be used to discriminate between these models. If, however, the trait is determined by multiple loci acting in a multiplicative fashion, λR - 1 will decline by greater than a factor of 2 with each degree relationship.
Under a multilocus, multiplicative model of inheritance, the rate of decrease λR - 1 is determined by the number of underlying loci as well as the degree interaction between loci; thus, it varies depending on the specifics of the underlying model. The predictions of various multiplicative models can, therefore, be compared to the observed familial recurrence pattern. In general, the power to discriminate between alternate multiplicative models of inheritance using this approach is low (Farrall and Holder, 1992). However, such comparisons are extremely helpful in defining the number of genes that contribute to a trait and the maximum plausible effect that any one gene may have on disease risk.
To estimate risk ratios under multiplicative models of inheritance, it is necessary to specify the number and magnitude of the effects at each locus in the model. For example, one multiplicative model of inheritance for CL/P might predict that the observed risk ratio, λ1 = 30, is determined by two loci, one that increases the risk of CL/P in first-degree relatives by sixfold and a second that increases the risk by fivefold. Since these two loci are hypothesized to act multiplicatively, they are the only loci required to account for the overall increase in risk observed among first-degree relatives (i.e., 6 × 5 = 30). To calculate the risk to other types of relative, the increase in λR attributable to susceptibility locus i is determined in a manner analogous to that outlined above. For example, λ 21 (the risk ratio for second-degree relatives attributable to the first locus) = 0.5(6 + 1) = 3.5, λ22 = 0.5(5 + 1) = 3.00, and the overall risk to second-degree relatives (λ2) is obtained as the product of the effects individual loci, or 3.5(3.0) = 10.0. Corresponding values for third-degree relatives are λ31 = 2.25,λ32 = 2.00, and λS 4.5. The expected decline in risk λR is clearly more dramatic under this multiplicative model (λ1 = 30,λ2 = 10,λ3 = 4.5) than under the single-locus model of inheritance (λ1 = 30,λ2 = 15.5,λ3, 8.25).
Familial Recurrence Pattern Analysis
Cleft Lip with or without Cleft Palate
Three analyses of the familial recurrence patterns observed for nonsyndromic CL/P, using the methods described above, have been published (Farrall and Holder, 1992; Mitchell and Risch, 1992; Mitchell and Christensen, 1996). Two of these studies were based on re-analyses of published data from multiple sources (Farrall and Holder, 1992; Mitchell and Risch, 1992), whereas the third was based on Danish data obtained by record linkage (Mitchell and Christensen, 1996). Despite differences in the types of bias that may have influenced the various data sets, the results from these studies are relatively consistent. In contrast to earlier segregation analyses, all three studies clearly excluded single-locus inheritance of CL/P. As the predictions of models with multiple additive loci and multiple independent loci are similar to those of the single major locus model, these models were also excluded in each of these studies.
Each of the familial recurrence studies of CL/P concluded that this condition is most likely determined by multiple genes acting in a multiplicative fashion. Further, these analyses suggest that there are likely to be two to eight CL/P susceptibility loci and that the maximum effect of any one of these loci would be to increase the risk to first-degree relatives of affected individuals by three to sixfold. The analyses based on the Danish data (Mitchell and Christensen, 1996) are summarized in Table 19.1 and suggest that CL/P is likely to be determined by two to three loci, with no single locus accounting for more than a threefold increase in risk to first-degree relatives. This analysis is likely to provide the most accurate indication of the mode of inheritance of CL/P for several reasons: it is based on a single, well-defined population, estimates of risk were obtained by record linkage rather than self-reported family history, and an accurate estimate of the population prevalence of CL/P in Denmark was used to estimate values of λR.
Cleft Palate
Two analyses of the familial recurrence patterns observed for nonsyndromic CP have been published (Fitzpatrick and Farrall, 1993; Christensen and Mitchell, 1996). One was based largely on the reanalysis of published data from multiple sources (Fitzpatrick and Farrall, 1993), whereas the other was based on Danish data obtained by record linkage (Christensen and Mitchell, 1996). Both studies provided strong evidence against single-locus inheritance of CP. Models of inheritance assuming multiple additive loci and multiple independent loci are, therefore, also unlikely for this condition.
|
TABLE 19.1. Familial Recurrence Pattern Analysis of Cleft Lip with or without Cleft Palate in Denmark |
|||||||||||||||||||||||||||||||||||||||||||||||||
|
|||||||||||||||||||||||||||||||||||||||||||||||||
The familial recurrence pattern exhibited by CP appears to be most consestent with an underlying multiplicative model of inheritance. The analyses based on the Danish data (Christensen and Mitchell, 1996) are summarized in Table 19.2 and suggest that CP is likely to be determined by several interacting loci. Under such a model, no single locus is likely to account for more than a sixfold increase in risk to first-degree relatives of affected individuals.
|
TABLE 19.2. Familial Recurrence Pattern Analysis of Cleft Palate in Denmark |
||||||||||||||||||||||||||||||||||||||||||||||||||||
|
||||||||||||||||||||||||||||||||||||||||||||||||||||
Conclusions
The results of familial recurrence pattern analyses for CL/P and CP have important implications for the design of studies aimed at the identification of specific susceptibility loci. These analyses indicate that the strongest susceptibility loci for these conditions may be associated with values of λ1i as large as 6 to 8 or as small as 2 to 3. Hence, the prospect of detecting such loci using traditional linkage approaches will be low, particularly if the latter estimates are correct. Moreover, even nonparametric linkage approaches (e.g. affected pedigree members, affected sib pairs) are likely to require sample sizes that will be difficult to achieve for these conditions (Risch, 1990c).
At present, association studies (see Chapter 20) targeted at specific candidate genes are likely to offer the most fruitful strategy for the identification of specific CL/P and CP susceptibility loci. Such studies should employ methods, such as the transmission disequilibrium test (Spielman et al., 1993), that eliminate concerns regarding false-positive findings attributable to population structure (Spielman et al., 1993; Ewens and Spielman, 1995) or focus on populations where such concerns are reduced. Association studies of CL/P and CP have begun to provide clues regarding the role of putative susceptibility loci (Wyszynski et al., 1996; Schutte and Murray, 1999). However, the full potential of this approach may not be realized until large-scale (i.e., genomewide) association studies for complex diseases become feasible.
Familial recurrence pattern analyses provide useful information regarding the genetic contribution to complex traits. However, such analyses do not consider all of the complexities that may be involved in the determination of a particular condition. For example, in the mouse, susceptibility to CL/P is influenced by both maternal genetic effects (Trasler and Trasler, 1984; Juriloff, 1986) and gene-environment interactions (Karolyi et al., 1987). Although such factors may also influence susceptibility to CL/P and CP in humans, their impact on familial recurrence patterns and on conclusions regarding mode of inheritance drawn from these patterns are difficult to predict. Hence, at present, mode of inheritance of CL/P and CP remains a vaguely defined concept that is unlikely to be fully elucidated until the specific causes of these conditions have been identified.
Acknowledgements
This work was supported in part by a grant (DEI 1388) from the National Institutes of Health.
References
Carter, CO (1969). Genetics of common disorders. BMJ 25: 52–57.
Christensen, K, Mitchell, LE (1996). Familial recurrence-pattern analysis of nonsyndromic isolated cleft palate-a Danish registry study. Am J Hum Genet 58: 182–190.
Chung, CS, Beechert, AM, Lew, RE (1989). Test of genetic heterogeneity of cleft lip with or without cleft palate as related to race and severity. Genet Epidemiol 6: 625–631.
Chung, CS, Bixler, D, Watanabe, T, et al. (1986). Segregation analysis of cleft lip with or without cleft palate: a comparison of Danish and Japanese data. Am J Hum Genet 39: 603–611.
Chung, CS, Ching, GHS, Morton, NE (1974). A genetic study of cleft lip and palate in Hawaii. Complex segregation analysis and genetic risk. Am J Hum Genet 26: 177–188.
Clementi, M, Tenconi, R, Collins, ACE, Milan, M (1995). Complex segregation analysis in a sample of consecutive newborns with cleft lip with or without cleft palate in Italy. Hum Hered 45: 157–164.
Demenais, F, Bonaiti-Pellie, C, Briard, ML, Feingold, J (1984). An epidemiological and genetic study of facial clefting in France. II. Segregation analysis. J Med Genet 21: 436–440.
Ewens, WJ, Spielman, RS (1995). The transmission/disequilibrium test: history, subdivision, and admixture. Am J Hum Genet 57: 455–464.
Falconer, DS (1965). The inheritance of liability to certain diseases, estimated from the incidence among relatives. Ann Hum Genet 29: 51–76.
Farrall, M, Holder, SE (1992). Familial recurrence pattern analysis of cleft lip with or without cleft palate. Am J Hum Genet 50: 270–277.
Fitzpatrick, D, Farrall, M (1993). An estimation of the number of susceptibility loci for isolated cleft palate. J Craniofac Genet Dev Biol 13: 230–235.
Fogh-Andersen, P (1942). Inheritance of Harelip and Cleft Palate. Copenhagen: Arnold Busck.
Gorlin, RJ, Cohan MM, Lavin, LS (1990). Syndromes of the Head and Neck. New York: Oxford University Press.
Hecht, JT, Yang, PMW, Buetow, KH (1991). Complex segregation analysis of nonsyndromic cleft lip and palate. Am J Hum Genet 49: 674–681.
Jones, MC (1988). Etiology of facial clefts: prospective evaluation of 428 patients. Cleft Palate Craniofac J 25: 16–20.
Juriloff, DM (1986). Major genes that cause cleft lip in mice: progress in the construction of a congenic strain and in linkage mapping. J Craniofac Genet Dev Biol 2(Suppl): 55–66.
Karolyi, IJ, Liu, S, Erickson, RP (1987). Susceptibility to phenytoininduced cleft lip with or without cleft palate: many genes are involved. Genet Res Camb 49: 43–49.
Khoury, MJ, Beaty, TH, Liang, KY (1988). Can familial aggregation of disease be explained by familial aggregation of environmental factors. Am J Epidemiol 127: 674–683.
Lander, ES, Schork, NJ (1994). Genetic dissection of complex traits. Science 265: 2037–2048.
Marazita, ML, Goldstein, AM, Smalley, SL, et al. (1986). Cleft lip with or without cleft palate: reanalysis of a three-generation family study from England. Genet Epidemiol 3: 335–342.
Marazita, ML, Hu, D-N, Spence, MA, et al. (1992). Cleft lip with or without cleft palate in Shanghai, China: evidence for an autosomal major locus. Am J Hum Genet 51: 648–653.
Mitchell, LE (1997). Genetic epidemiology of birth defects: nonsyndromic cleft lip and neural tube defects. Epidemiol Rev 19: 61–68.
Mitchell, LE, Christensen, K (1996). Analysis of the recurrence patterns for nonsyndromic cleft lip with or without cleft palate in the families of 3,073 Danish probands. Am J Med Genet 61: 371–376.
Mitchell, LE, Risch, N (1992). Mode of inheritance of nonsyndromic cleft lip with or without cleft palate: a reanalysis. Am J Hum Genet 51: 323–332.
Nemana, LJ, Marazita, ML, Melnick, M (1992). Genetic analysis of cleft lip with or without cleft palate in Madras, India. Am J Med Genet 42: 5–9.
Ott, J (1990). Cutting a Gordian knot in linkage analysis of complex human traits. Am J Hum Genet 46: 219–221.
Pietrzyk, JJ, Rozanski, BS, Swisterska, E (1985). Genetic analysis of cleft lip and cleft palate in S. Poland: complex segregation analysis. Acta Anthropogenet 9: 140–152.
Ray, AK, Field, LL, Marazita, ML (1993). Nonsyndromic cleft lip with or without cleft palate in West Bengal, India: evidence for an autosomal major locus. Am J Hum Genet 52: 1006–1011.
Risch, N (1990a). Genetic linkage and complex diseases, with special reference to psychiatric disorders. Genet Epidemiol 7: 3–16.
Risch, N (1990b). Linkage strategies for genetically complex traits. I. Multilocus models. Am J Hum Genet 46: 222–228.
Risch, N (1990c). Linkage strategies for genetically complex traits. II. The power of affected relative pairs. Am J Hum Genet 46: 229–241.
Saal, HM (1998). Syndromes and malformations associated with cleft lip with or without clerft palate. Am J Hum Genet 63S: A118.
Schutte, BC, Murray, JC (1999). The many faces and factors of orofacial clefts. Hum Mol Genet 8: 1853–1859.
Smith, C (1971). Discriminating between different modes of inheritance in genetic disease. Clin Genet 2: 303–314.
Spielman, RS, McGinnis, RE, Ewens, WJ (1993). Transmission test for linkage disequilibrium: the insulin gene region and insulindependent diabetes mellitus (IDDM). Am J Hum Genet 52: 506–516.
Trasler, DG, Trasler, TA (1984). Left cleft lip predominance and genetic similarities of L line and CL/Fr strain mice. Teratology 30: 423–427.
Wyszynski, DF, Beaty, TH, Maestri, NE (1996). Genetics of nonsyndromic oral clefts revisited. Cleft Palate Craniofac J 33: 406–417.